Related Experiment Video
Updated: Oct 1, 2026
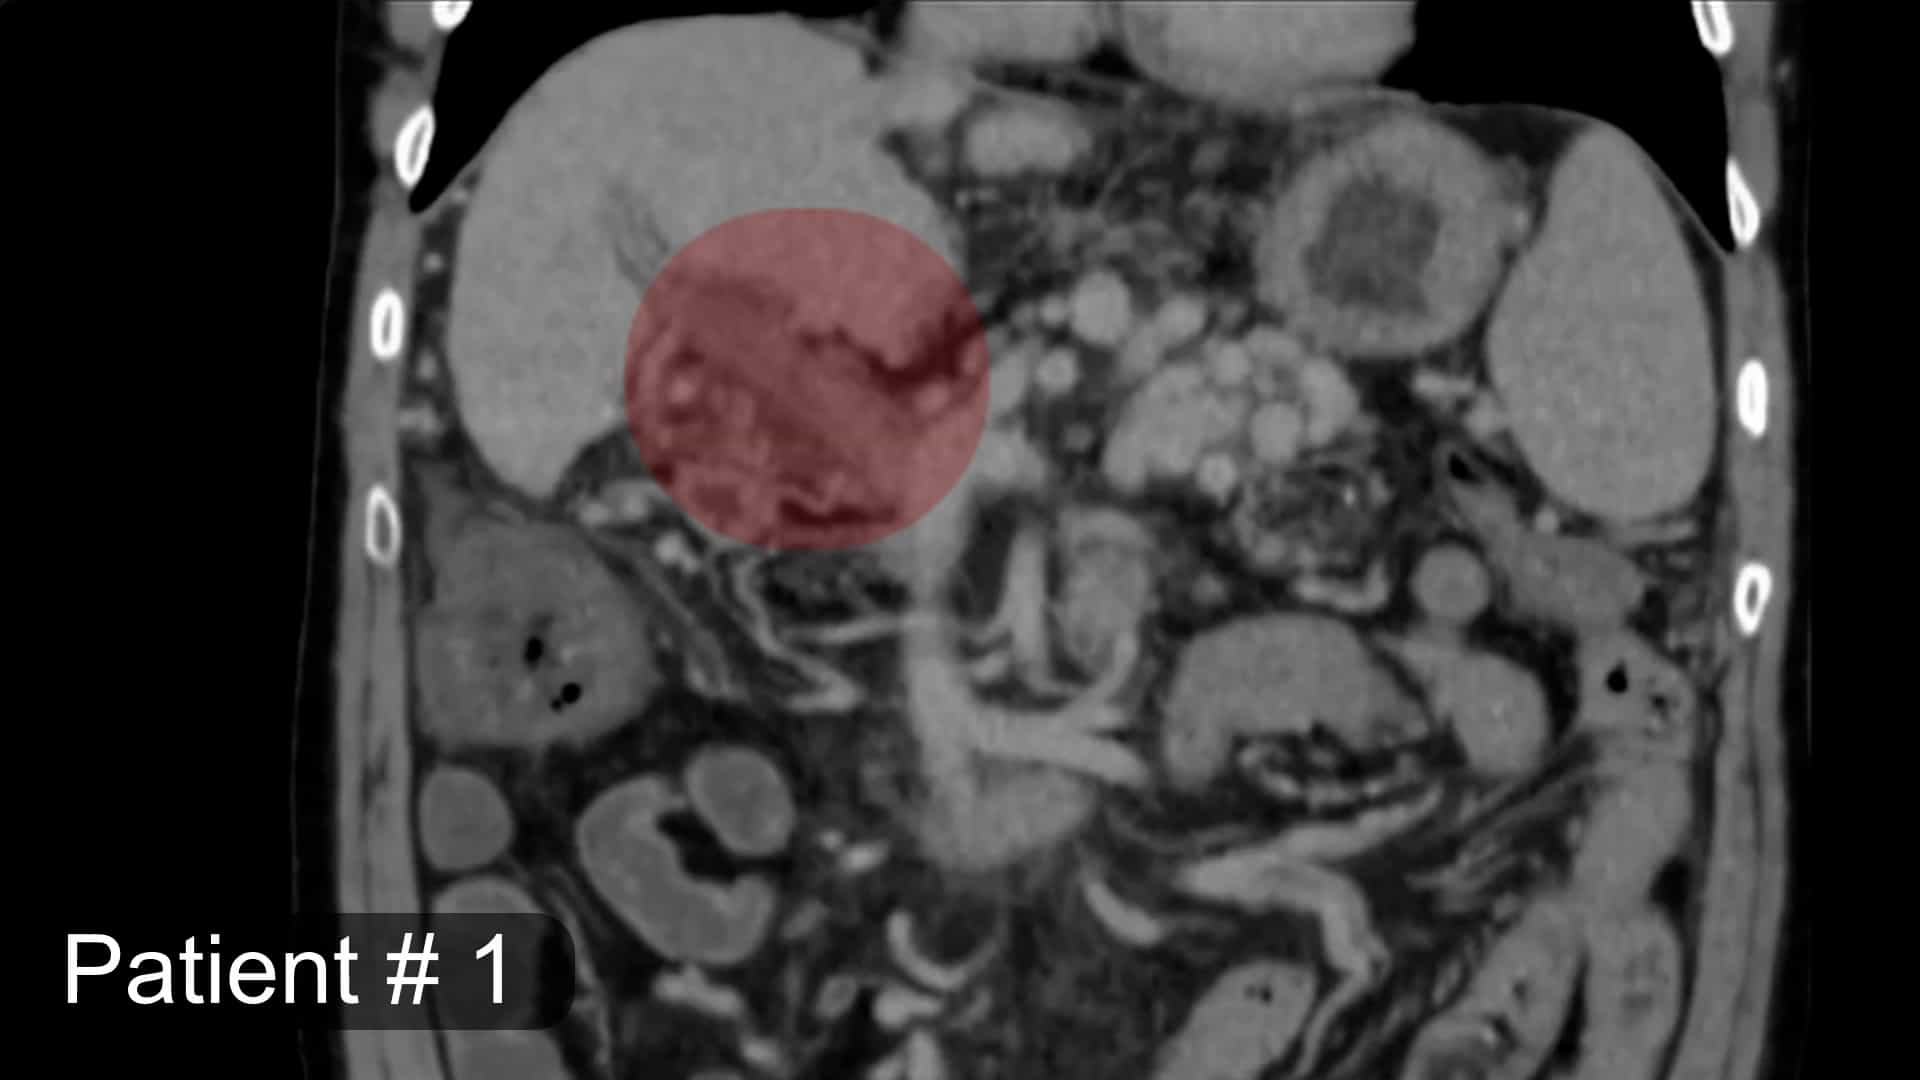

New Thrombectomy Technique for Total Portal Vein Thrombosis in Liver Transplantation
Published on: June 27, 2025
Superior mesenteric vein thrombosis presented transient false positivity for lupus anticoagulant under heparin
1Division of Critical Care Medicine, Osaka City University Medical School, Osaka, Japan.

A 24-year-old Japanese man was admitted because of massive haematemesis and melaena with persistent abdominal pain. Markedly bloody ascites and severely oedematous small intestine were recognized, and angiography then revealed superior mesenteric vein thrombosis. After resection of the necrotic small intestine, continuous intravenous infusion of heparin and urokinase was performed. This patient had no familial or personal history of thrombosis. On the 15th day after operation, an initial search for lupus anticoagulant revealed that the prothrombin time (PT) ratio and dilute activated partial thromboplastin time (aPTT) were positive under heparin treatment, without evidence of rheumatic or connective tissue disease. Thrombocytopenia was observed with a nearly normocellular bone marrow. A follow-up examination 1 year later still revealed an increased aPTT. However, all tests for antiphospholipid antibodies had been negative including dilute aPTT for about 2 years since the 15th day after operation. These findings suggest that, in this patient, superior mesenteric vein thrombosis has not been associated with primary antiphospholipid syndrome but is probably idiopathic. Positive tests for lupus anticoagulant in the initial period may be unreliable due to heparin treatment.
A 24-year-old Japanese man was admitted because of massive haematemesis and melaena with persistent abdominal pain. Markedly bloody ascites and severely oedematous small intestine were recognized, and angiography then revealed superior mesenteric vein thrombosis. After resection of the necrotic small intestine, continuous intravenous infusion of heparin and urokinase was performed. This patient had no familial or personal history of thrombosis. On the 15th day after operation, an initial search for lupus anticoagulant revealed that the prothrombin time (PT) ratio and dilute activated partial thromboplastin time (aPTT) were positive under heparin treatment, without evidence of rheumatic or connective tissue disease. Thrombocytopenia was observed with a nearly normocellular bone marrow. A follow-up examination 1 year later still revealed an increased aPTT. However, all tests for antiphospholipid antibodies had been negative including dilute aPTT for about 2 years since the 15th day after operation. These findings suggest that, in this patient, superior mesenteric vein thrombosis has not been associated with primary antiphospholipid syndrome but is probably idiopathic. Positive tests for lupus anticoagulant in the initial period may be unreliable due to heparin treatment.
Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:30
Venous Thrombosis I: Introduction
 01:22
Portal Hypertension