Related Experiment Video
Updated: Sep 30, 2026
Shunt Surgery, Right Heart Catheterization, and Vascular Morphometry in a Rat Model for Flow-induced Pulmonary Arterial Hypertension
Published on: February 11, 2017
Bovine jugular vein as right ventricle-to-pulmonary artery valved conduit
Antonio F Corno1, Michel Hurni, Helen Griffin
1Centre Hospitalier Universitaire Vaudois (CHUV), Lausanne, Switzerland.

Background And Aims Of The Study:
The reduced availability of homografts and investigations into the ideal valved conduit have prompted a search for alternative options. This prospective study evaluated the Contegra, a new biological valved conduit consisting of a glutaraldehyde-preserved heterologous bovine jugular vein having a trileaflet venous valve.
Methods:
Between April 1999 and May 2001, 26 patients (mean age 13.5+/-12.5 years; range: 4 months to 43 years), of mean body weight 33.9+/-26.7 kg (range: 4.0-91.0 kg), underwent implantation of a Contegra valved conduit for the following diagnoses: pulmonary valve replacement during Ross operation (n = 11), pulmonary atresia with ventricular septal defect (n = 6), tetralogy of Fallot (n = 3), truncus arteriosus (n = 3), Taussig-Bing syndrome (n = 2), and pulmonary valve regurgitation (n = 1). Conduit size was 14 mm in two patients, 16 mm in four, 18 mm in three, 20 mm in three, and 22 mm in 14. Mean cardiopulmonary bypass time was 156+/-33 min (range: 105-233 min), and mean aortic cross-clamp time 79+/-29 min (range: 0-128 min).
Results:
There were no hospital deaths. During a mean follow up of 14.7+/-6.9 months (range: 1-26 months) there was one late death (4% mortality) that was unrelated to the valved conduit. Three children underwent reoperation; in all cases this was nonconduit-related. All 25 late survivors are currently free from reoperation and complications due to presence of the conduit. Echocardiographically monitored valve regurgitation was absent in 12 cases, trivial in nine and mild in four. The discharge situation was maintained during systematic follow up. No difference was found between the pressure gradient at discharge and at the last follow up.
Conclusion:
The new conduit provided consistently good results during its first two years of use. The main advantages were: (i) excellent off-the-shelf availability; (ii) large variety of available sizes (12 to 22 mm internal diameter); (iii) easy tailoring and suturing; (iv) adequate hemodynamics; (v) no need for proximal or distal extension; and (vi) reduced cost (half that of a conventional homograft).

Related Concept Videos
 01:16
Chambers of the Heart
Deoxygenated blood from the body is received in the right...
 01:16
Heart Valves
The AV valves prevent the backflow of blood from the ventricles to the atria during ventricular contraction. These valves function with the assistance of the chordae tendineae and papillary muscles. When the ventricles are relaxed, the chordae tendineae are slack, allowing blood to flow from the atria into the...
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...
 01:04
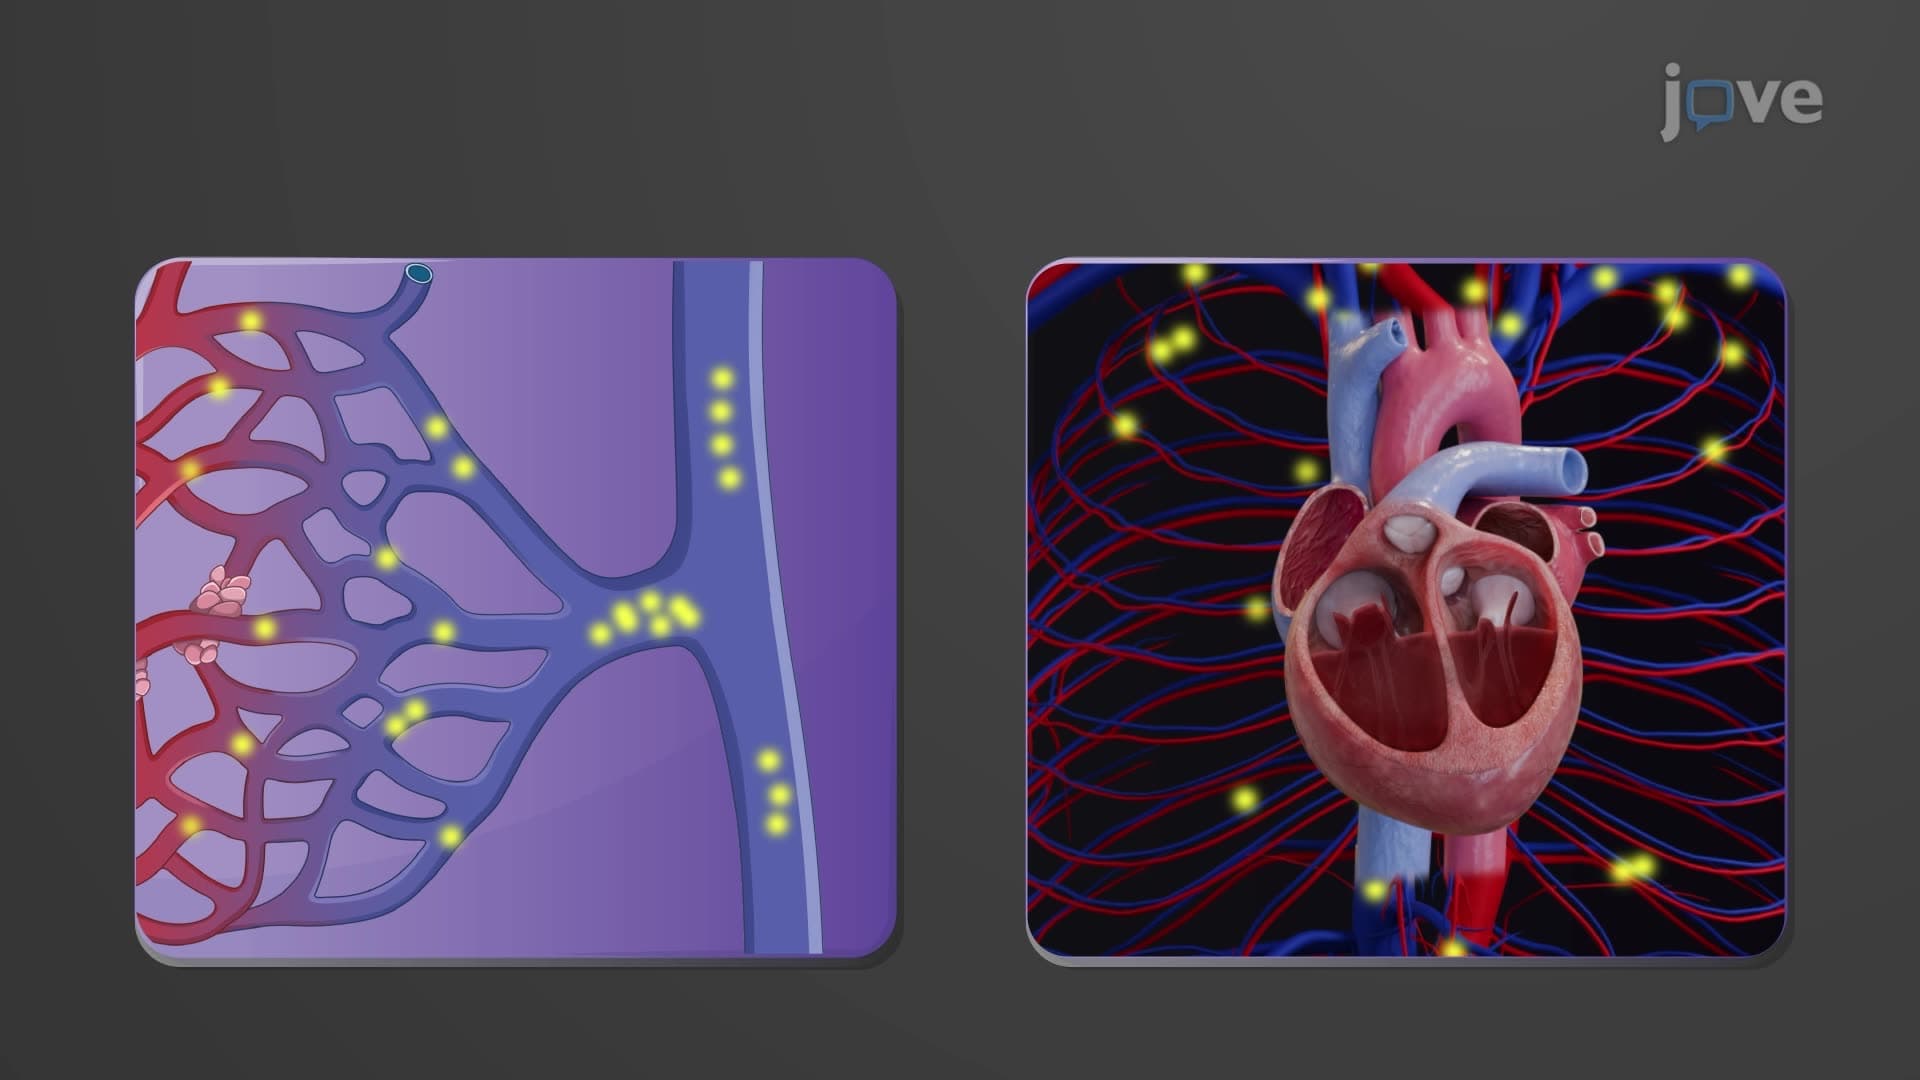
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system as it...
 01:11
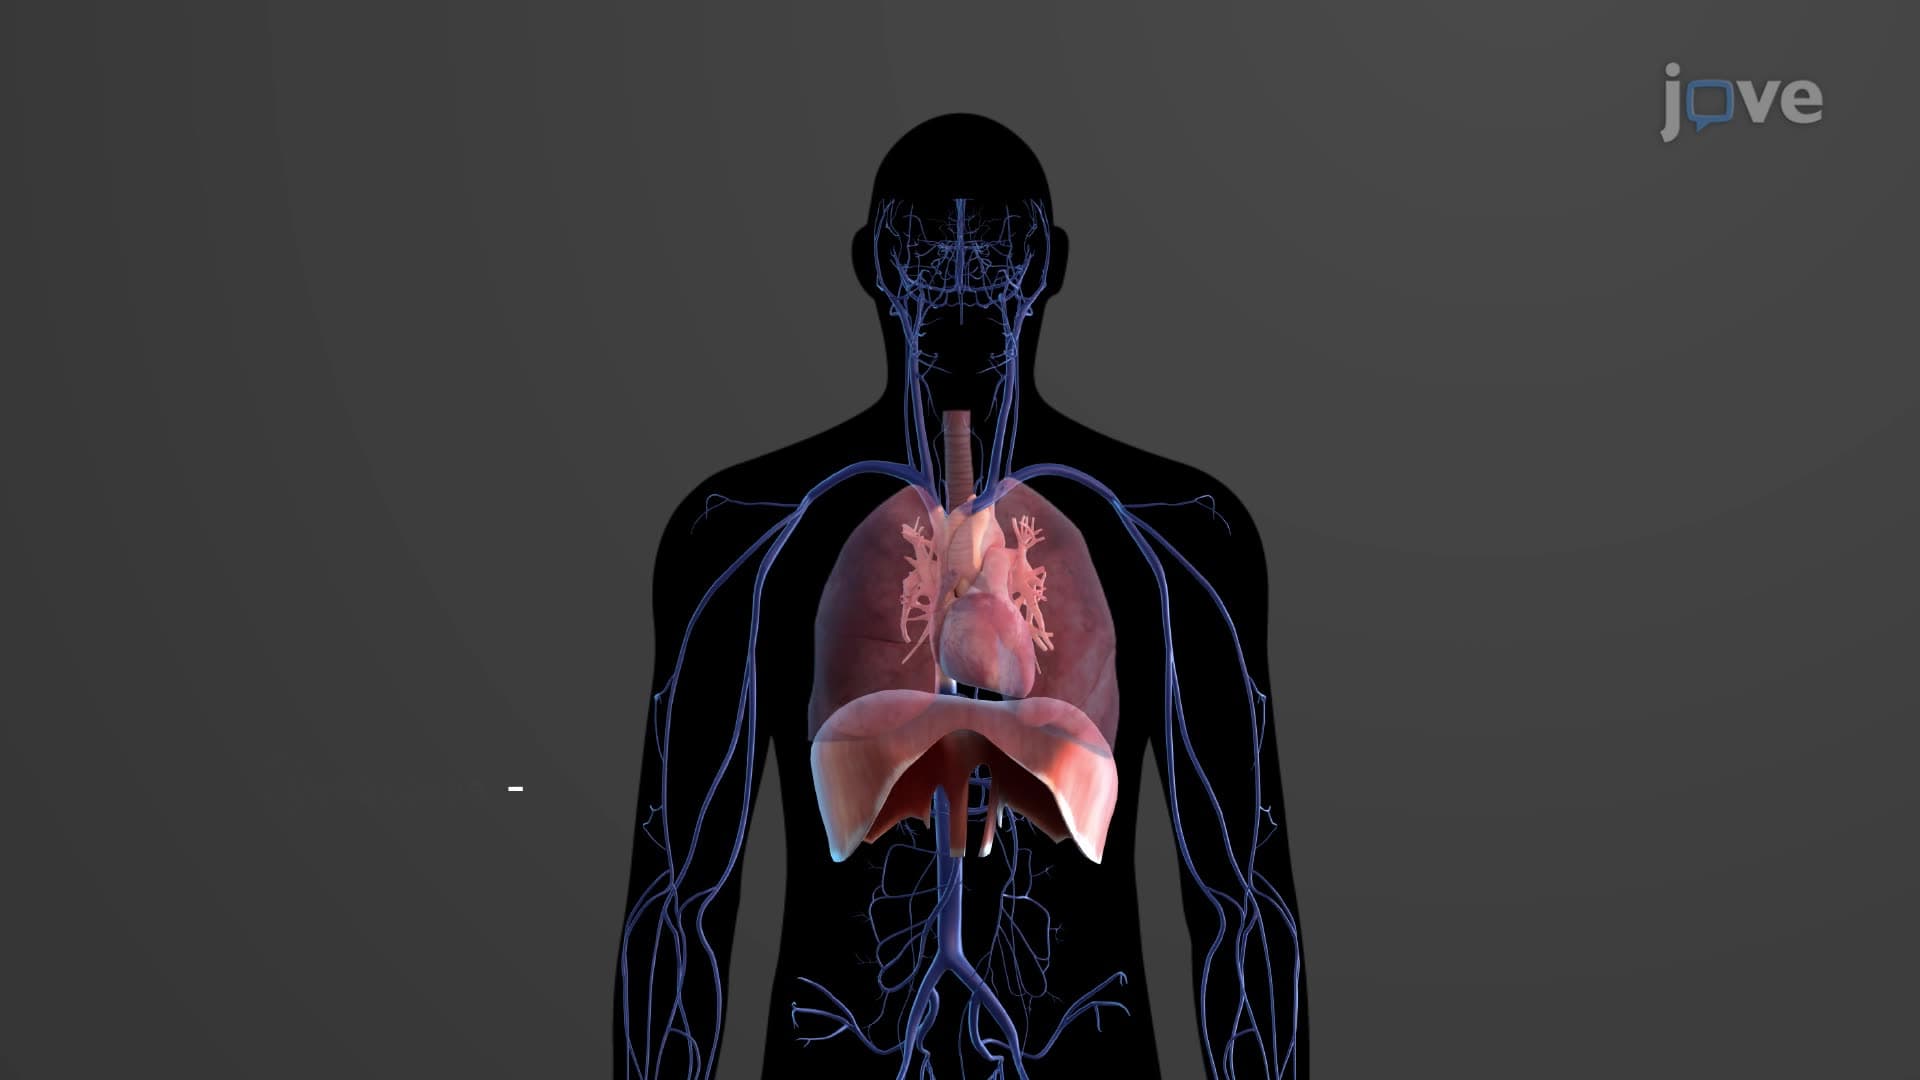
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the middle...
 01:21
Cardiac Catheterization II: Right Heart Catheterization