Related Experiment Video
Updated: Aug 18, 2026

Probiotic Studies in Neonatal Mice Using Gavage
Published on: January 27, 2019
Comparison of two gentamicin dosing schedules in very low birth weight infants
Alok Rastogi1, Ghanshyam Agarwal, Suma Pyati
1Department of Pediatrics, Cook County Children's Hospital, Chicago, IL 60612, USA. arastogi1@hotmail.com

Insights
The 48-hour gentamicin dosing schedule for very low birth weight infants achieved therapeutic levels, but nearly one-third had low concentrations before the next dose. A 36-hour interval may be optimal for gentamicin therapy.
Area of Science:
- Neonatal Pharmacology
- Pediatric Infectious Diseases
- Clinical Pharmacy
Background:
- Gentamicin dosing in very low birth weight (VLBW) infants is critical for treating sepsis.
- Existing dosing schedules require evaluation for optimal efficacy and safety in preterm neonates.
Purpose of the Study:
- To compare the efficacy and pharmacokinetics of two gentamicin dosing schedules in preterm neonates.
- To evaluate a new every 48 hours (q48h) dosing schedule against the existing every 24 hours (q24h) schedule.
Main Methods:
- A prospective, randomized controlled trial involving 58 VLBW infants (600-1500 g) treated for suspected sepsis.
- Infants received either q48h (5.0 or 4.5 mg/kg/dose) or q24h (2.5 or 3.0 mg/kg/dose) gentamicin.
- Peak and trough serum gentamicin concentrations were monitored.
Main Results:
- The q48h schedule resulted in significantly higher peak serum gentamicin concentrations (8.19 vs. 6.04 µg/mL) compared to q24h.
- Ninety percent of q48h infants achieved therapeutic peak concentrations (6-12 µg/mL) versus 55% of q24h infants.
- While q48h reduced subtherapeutic peaks, 30% of infants had low trough concentrations (<0.5 µg/mL) before the next dose.
Conclusions:
- The q48h gentamicin schedule achieves therapeutic peaks in VLBW infants but may lead to prolonged periods of low trough concentrations.
- Nearly one-third of infants on q48h dosing had very low trough levels, potentially impacting efficacy.
- A 36-hour dosing interval warrants investigation to balance bactericidal activity and minimize prolonged sub-therapeutic levels.
Background:
Several dosing schedules for gentamicin have been recommended for very low birth weight infants during the early neonatal period. We conducted a prospective, randomized, controlled trial to compare efficacy and pharmacokinetics of two dosing schedules in preterm neonates.
Methods:
Fifty-eight very low birth weight infants (600 to 1500 g), prescribed gentamicin for treatment of suspected sepsis during the first week after birth, were randomized to receive either the new dosing schedule [every 48 h (q48h)] or the existing dosing schedule [every 24 h (q24h)]. Infants in the "q48h" group received gentamicin at 5.0 or 4.5 mg/kg/dose q48h depending on weight group and infants in the "q24h" group received 2.5 or 3.0 mg/kg/dose q24h. Peak and trough serum gentamicin concentrations were monitored.
Results:
Peak serum gentamicin concentrations after the first dose were significantly higher in the q48h infants than in q24h infants (8.19 +/- 1.3 vs. 6.04 +/- 2.2, P = 0.00001). Ninety percent of all peak serum gentamicin concentrations in the q48h group were in a higher therapeutic range of 6 to 12 microg/ml as compared with 55% of q24h (P = 0.0005). None of the q48h infants had subtherapeutic serum gentamicin concentrations immediately after administration of the first dose as compared with 36% of q24h infants (P < 0.005). Eighteen percent of q24h infants continued to have peak serum gentamicin concentrations in subtherapeutic range even after the third dose at 48 h. Trough serum gentamicin concentrations were significantly lower in q48h infants than in q24h infants. However, 9 of 30 (30%) q48h infants had trough serum gentamicin concentrations of < or = 0.5 microg/ml before the dose at 48 h and 4 of the 9 had serum gentamicin concentrations of <1 microg/ml at 24 h after the first dose.
Conclusions:
The q48h dosing schedule of gentamicin given to very low birth weight infants during the first week after birth achieved therapeutic serum gentamicin concentrations and potentially higher peak to MIC ratios for microorganisms in all infants. However, nearly one-third of the infants had extremely low serum gentamicin concentrations before the next dose. A dosing interval of 36 h might be optimal for bactericidal activity and avoid bacterial growth during prolonged periods of extremely low serum gentamicin concentrations; this dosing interval warrants study.


Related Concept Videos
 01:19
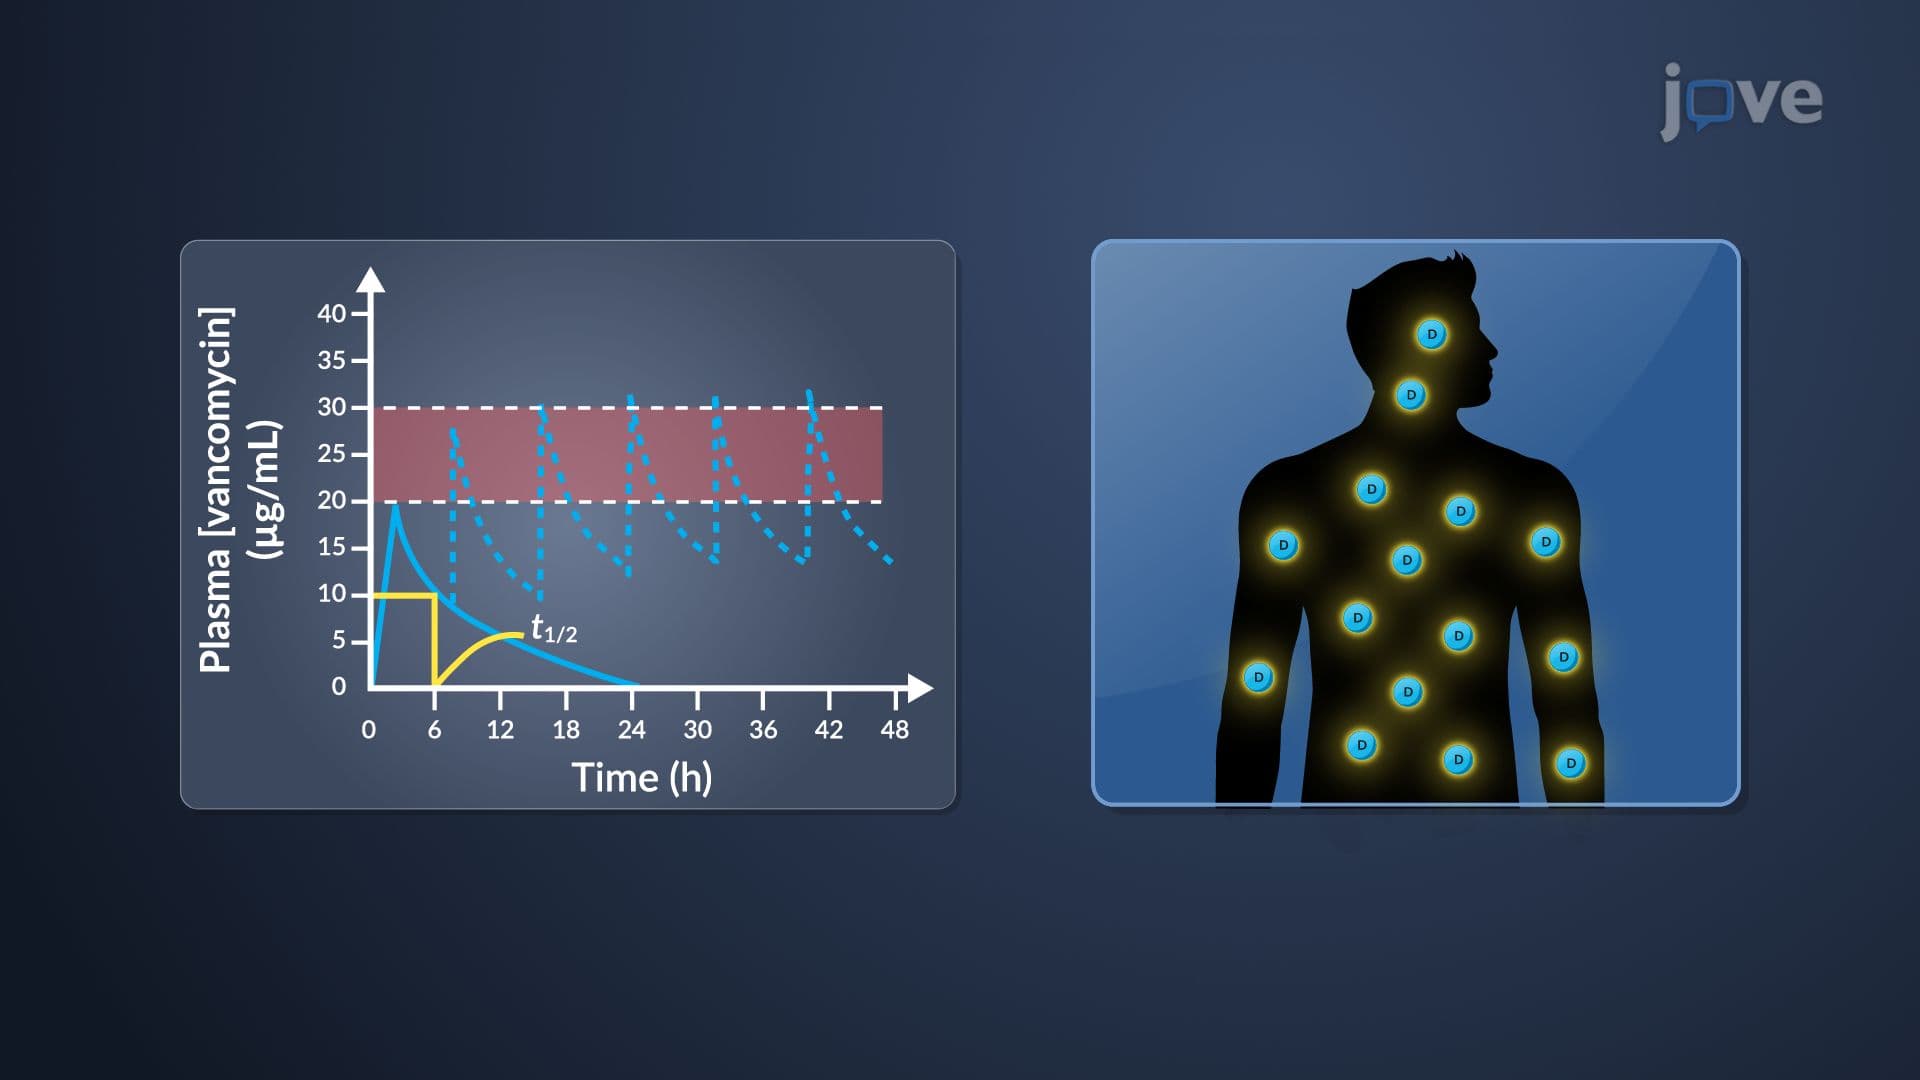
Dosage Interval and Administration Route: Determination Methods
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:20
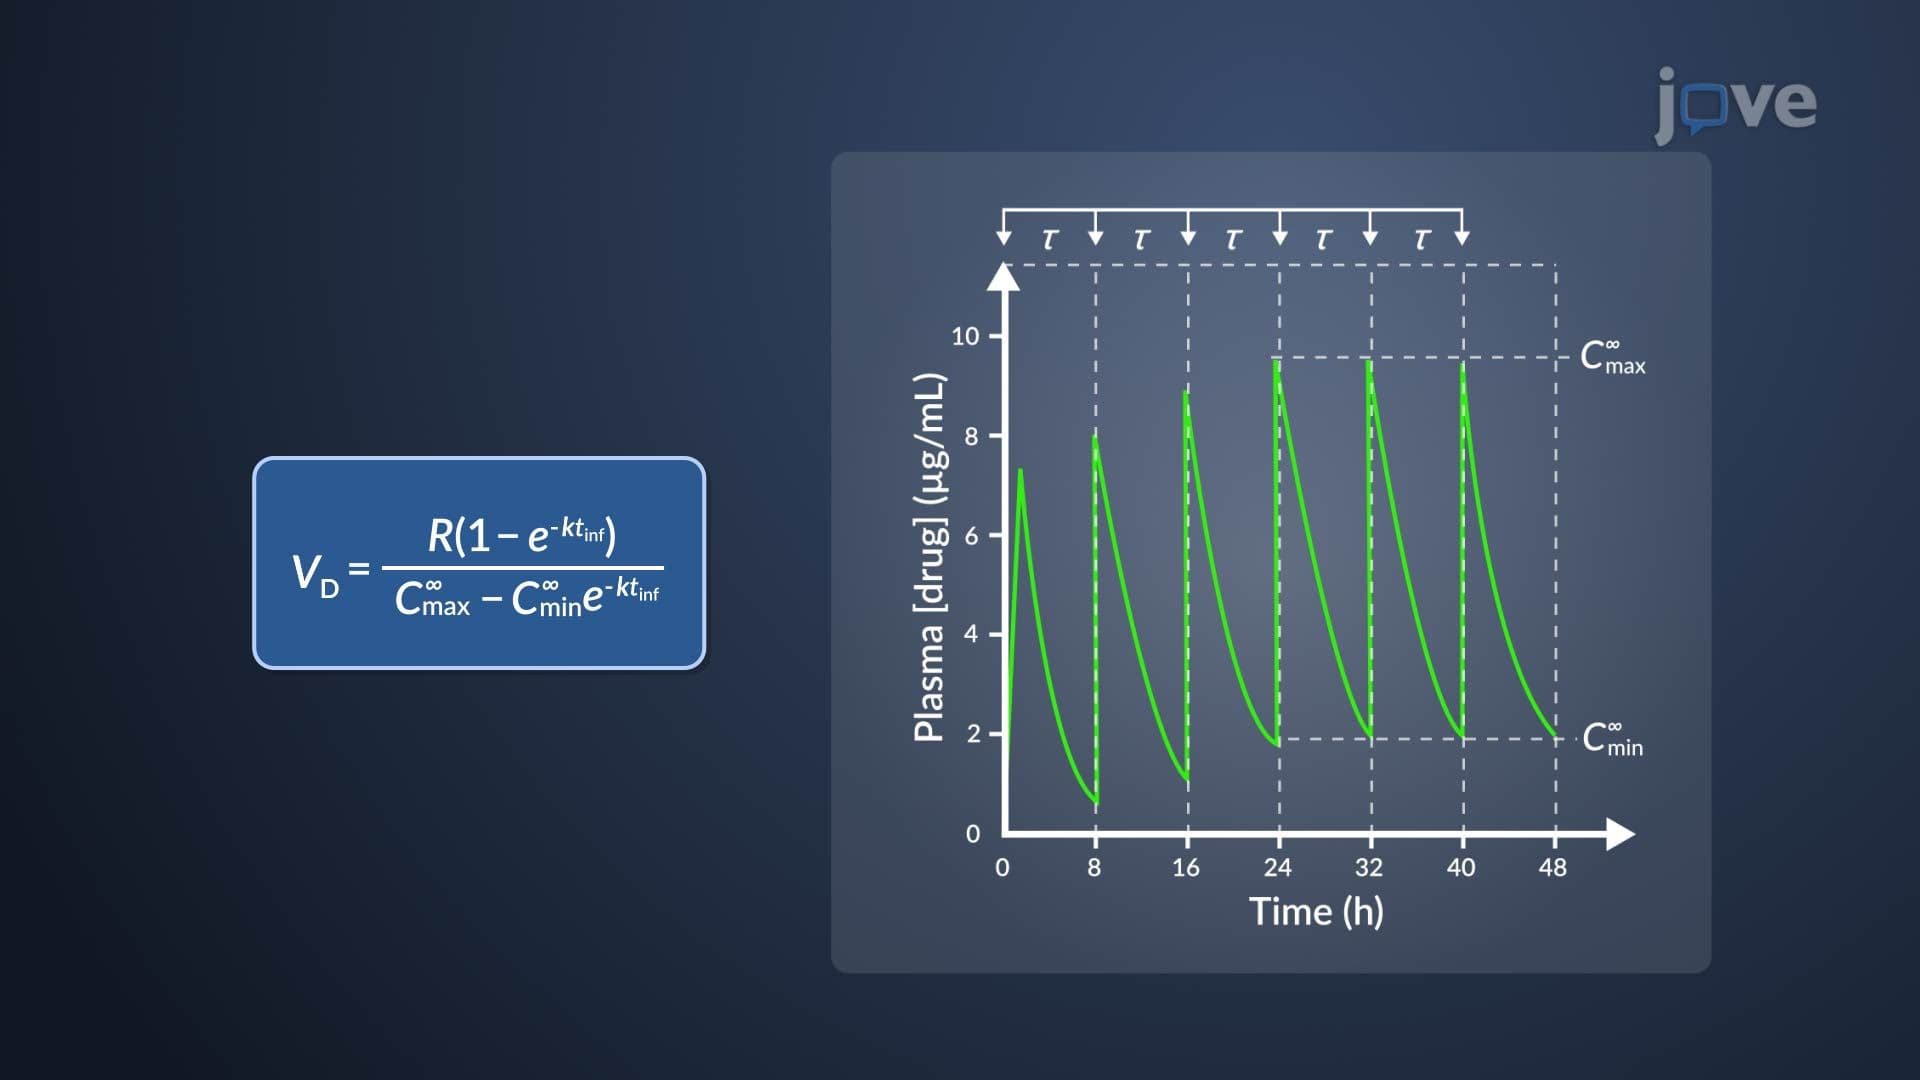
Estimation of k and VD of Aminoglycosides
 01:28
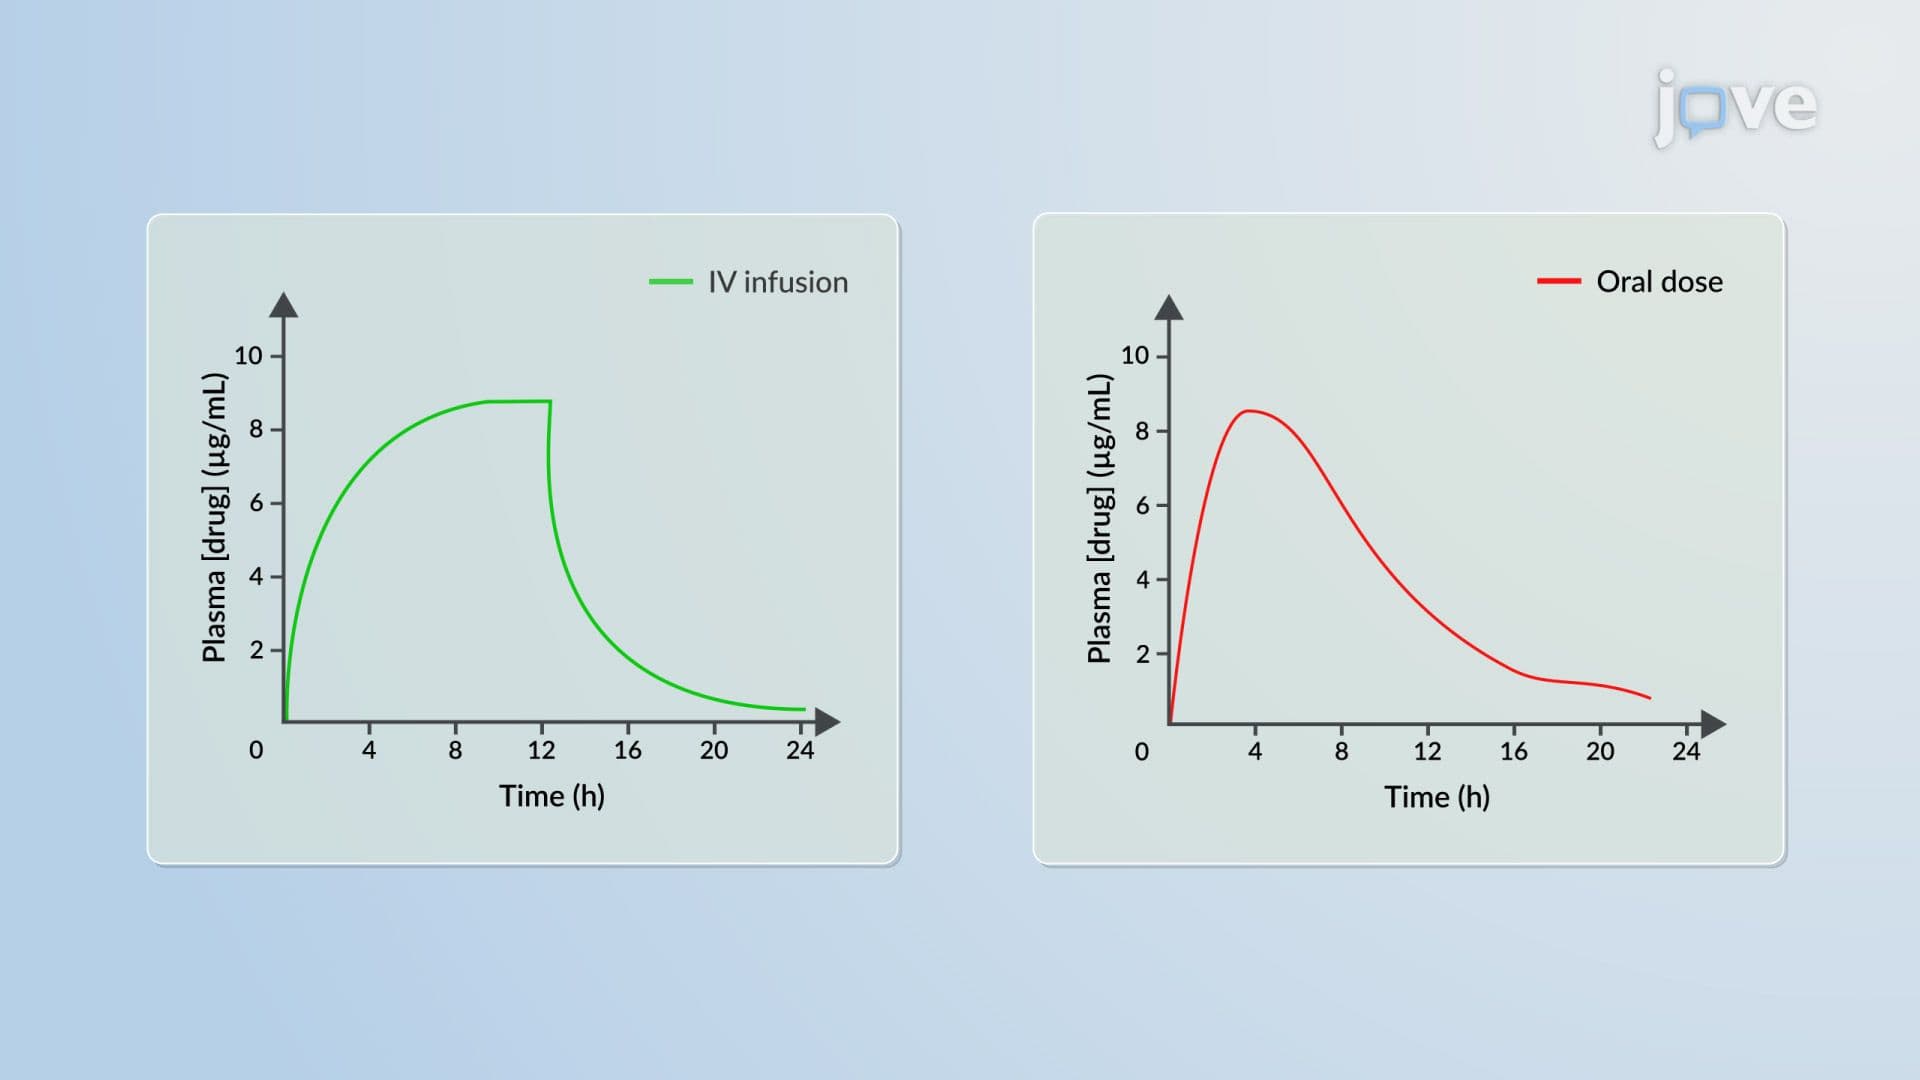
IV Infusion to Oral Dosing: Conversion Methods
 01:29
Drug Dosing: Infants and Children