Related Experiment Video
Updated: Oct 1, 2026
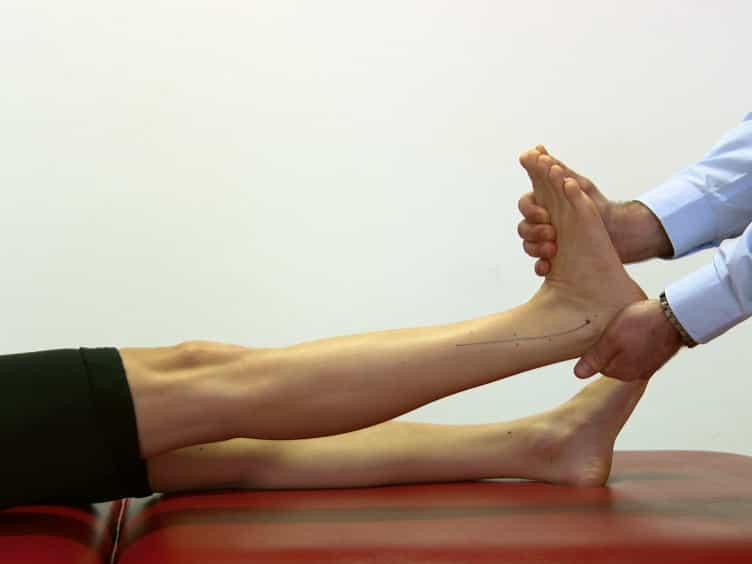
Diagnosis of Musculus Gastrocnemius Tightness - Key Factors for the Clinical Examination
Published on: July 7, 2016
Architecture of the medial gastrocnemius in children with spastic diplegia
Adam P Shortland1, Charlotte A Harris, Martin Gough
1One Small Step Gait Laboratory, Guy's Hospital, London, UK. adam.shortland@gstt.sthames.nhs.uk

Insights
In children with spastic diplegia, medial gastrocnemius muscle contracture is not due to reduced muscle fiber length. Findings suggest aponeuroses shortness may explain fixed muscle shortness in these patients.
Area of Science:
- Biomedical Engineering
- Musculoskeletal Ultrasound
- Pediatric Orthopedics
Background:
- Spastic diplegia, a common form of cerebral palsy, often leads to muscle contractures, particularly in the medial gastrocnemius.
- Understanding the structural basis of these contractures is crucial for effective treatment and management.
- Muscle architecture, including fascicle length and pennation angle, influences muscle function and length.
Purpose of the Study:
- To investigate differences in medial gastrocnemius muscle architecture between typically developing children and children with spastic diplegia.
- To determine if reduced fascicle length contributes to the observed muscle contracture in spastic diplegia.
- To explore potential structural origins of muscle contracture in ambulatory children with spastic diplegia.
Main Methods:
- Ultrasound imaging was used to measure medial gastrocnemius fascicle length and deep fascicle angle.
- Measurements were taken in normally developing adults, normally developing children, and children with spastic diplegia at various ankle joint positions.
- Statistical analysis was performed to compare architectural variables between the groups.
Main Results:
- Fascicle length and deep fascicle angle were similar between normally developing adults and children.
- No significant difference in fascicle length was found between normally developing children and children with spastic diplegia.
- Deep fascicle angles were significantly reduced in the spastic diplegia group at a specific ankle joint angle, but not at resting angles.
Conclusions:
- Reduced muscle fiber length does not appear to be the primary cause of medial gastrocnemius contracture in ambulatory children with spastic diplegia.
- The observed differences in deep fascicle angle are likely related to resting muscle length and may not have clinical significance.
- Muscle contracture in spastic diplegia may be better explained by aponeuroses shortness, potentially linked to reduced muscle fiber diameter, rather than reduced fiber length.
Abstract:
Ultrasound images were obtained of the medial gastrocnemius at different ankle joint positions with the knee extended. Fascicle length and deep fascicle angle were measured in five normally developing adults (mean age 33 years, age range 24 to 36 years) and in five normally developing children (mean age 7.8 years, age range 7 to 11 years), and in seven children with spastic diplegia (mean age 10 years, age range 6 to 13 years). These architectural variables were similar in the groups of normally developing adults and children. Importantly, no statistical difference could be found between the normally developing children and those with diplegia for fascicle length. Deep fascicle angles were reduced significantly in the clinical group at a particular ankle joint angle but not at the resting angles. The difference in deep fascicle angles is explained as a function of resting muscle length and is not attributed any clinical importance. Our results do not explain the structural origin of muscle contracture explicitly. However, they do indicate that most of the fixed shortness in the medial gastrocnemii of ambulant children with spastic diplegia is not due to reduced muscle fibre length. We suggest that muscle contracture may be better explained in terms of shortness of the aponeuroses of pennate muscles, such as the medial gastrocnemius, through reduced muscle fibre diameter.


Related Concept Videos
 01:28
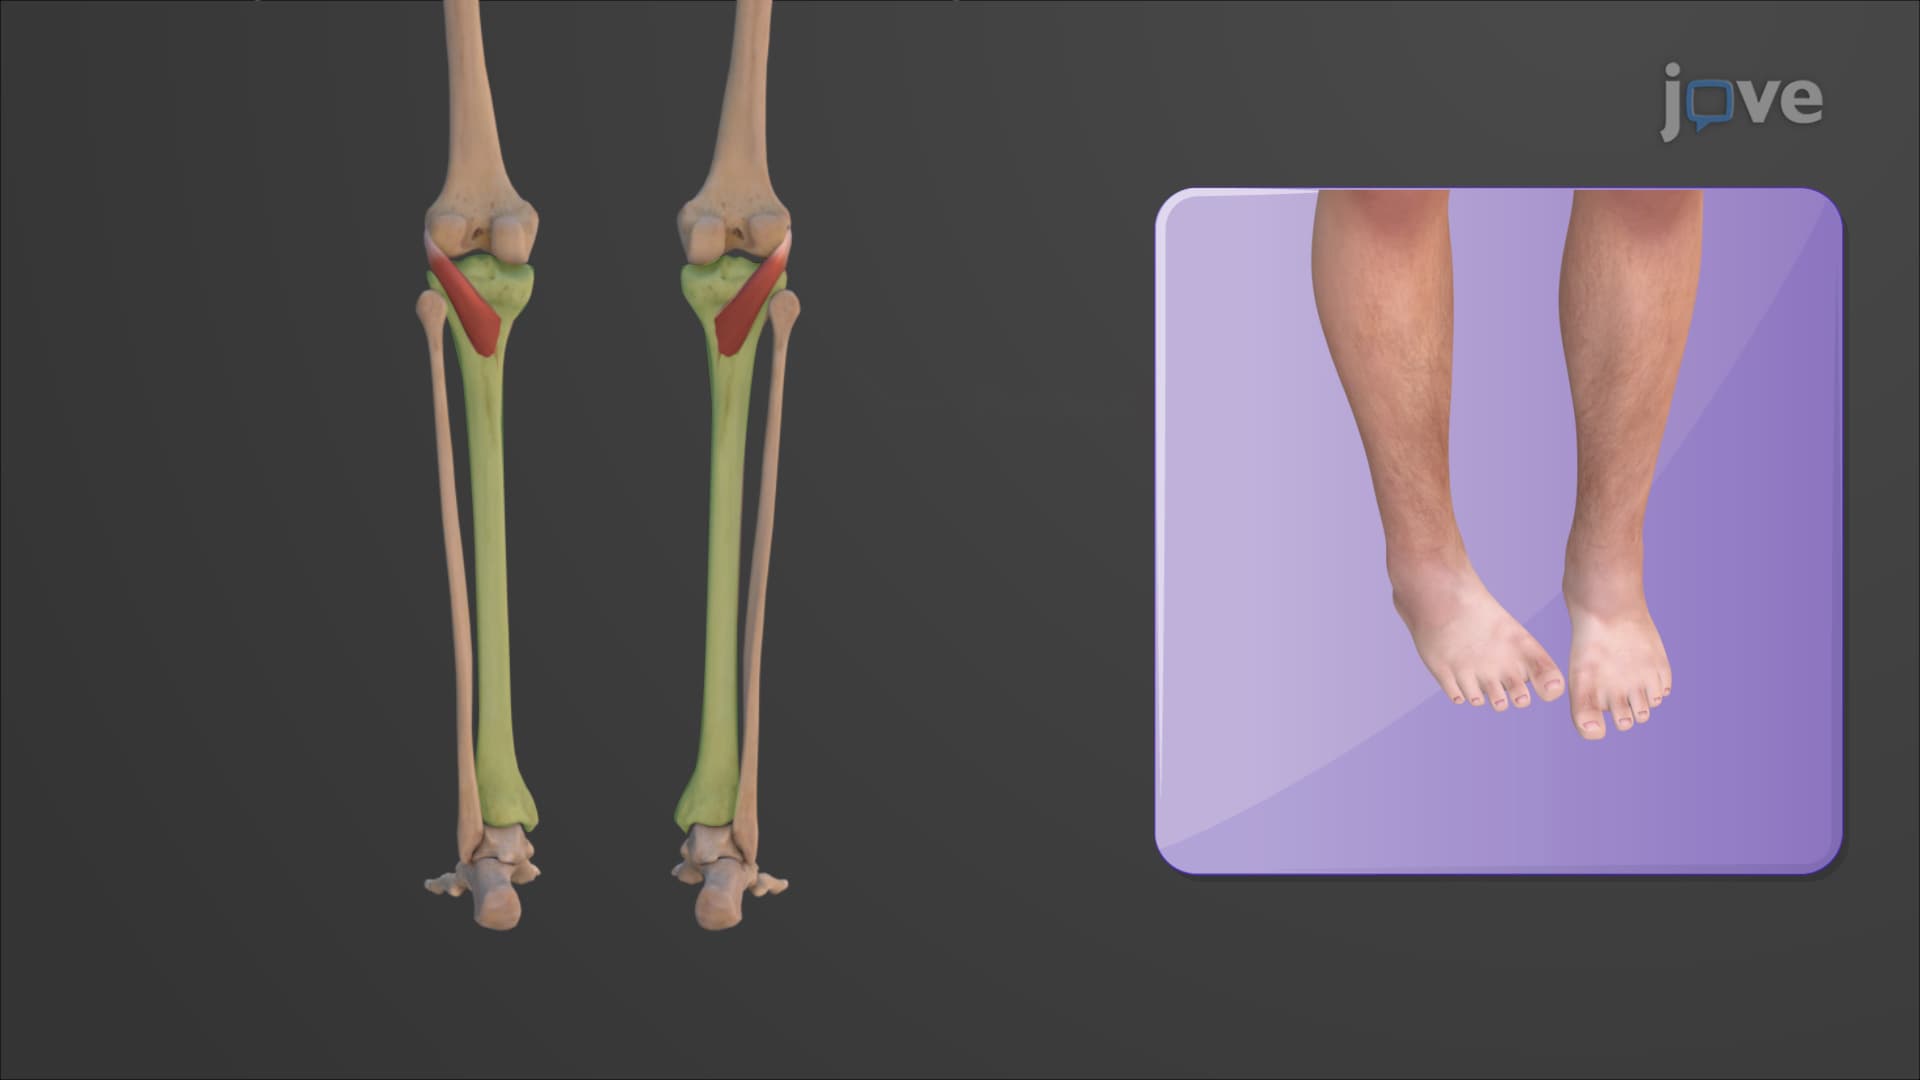
Muscles of the Leg that Move the Foot and Toes
Anterior Compartment
The anterior compartment includes muscles that contribute to the dorsiflexion of the foot. This compartment houses the tibialis anterior, extensor hallucis longus, and extensor digitorum longus muscles.
 01:23
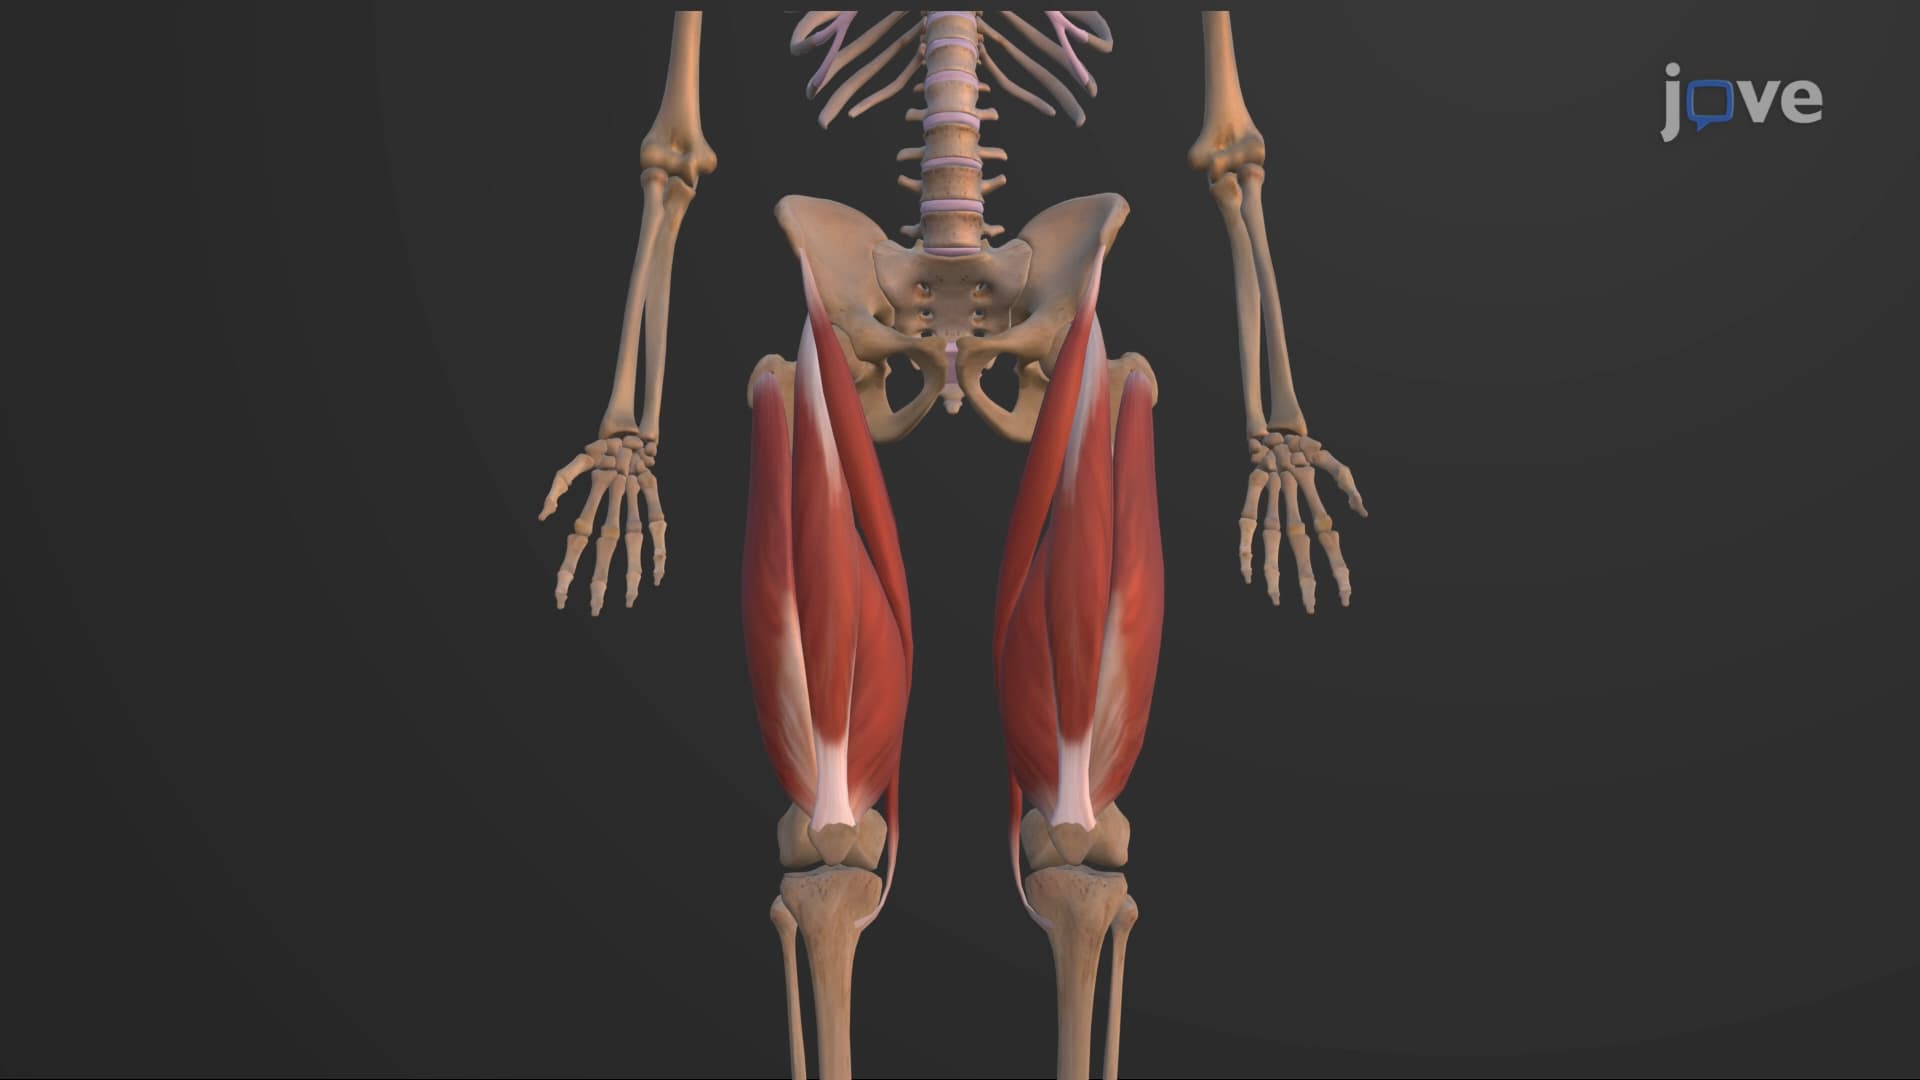
Muscles that Move the Leg
Anterior Compartment
The quadriceps femoris, the most visible muscle of the anterior compartment, is integral for leg extension and thigh flexion. It is formed by merging four distinct muscles — the vastus lateralis, vastus medialis, vastus intermedius, and rectus femoris. The quadriceps tendon, a shared tendon of the four quadriceps muscles, is affixed to...
 01:16
Bones of the Lower Limb: Femur and Patella
 01:20
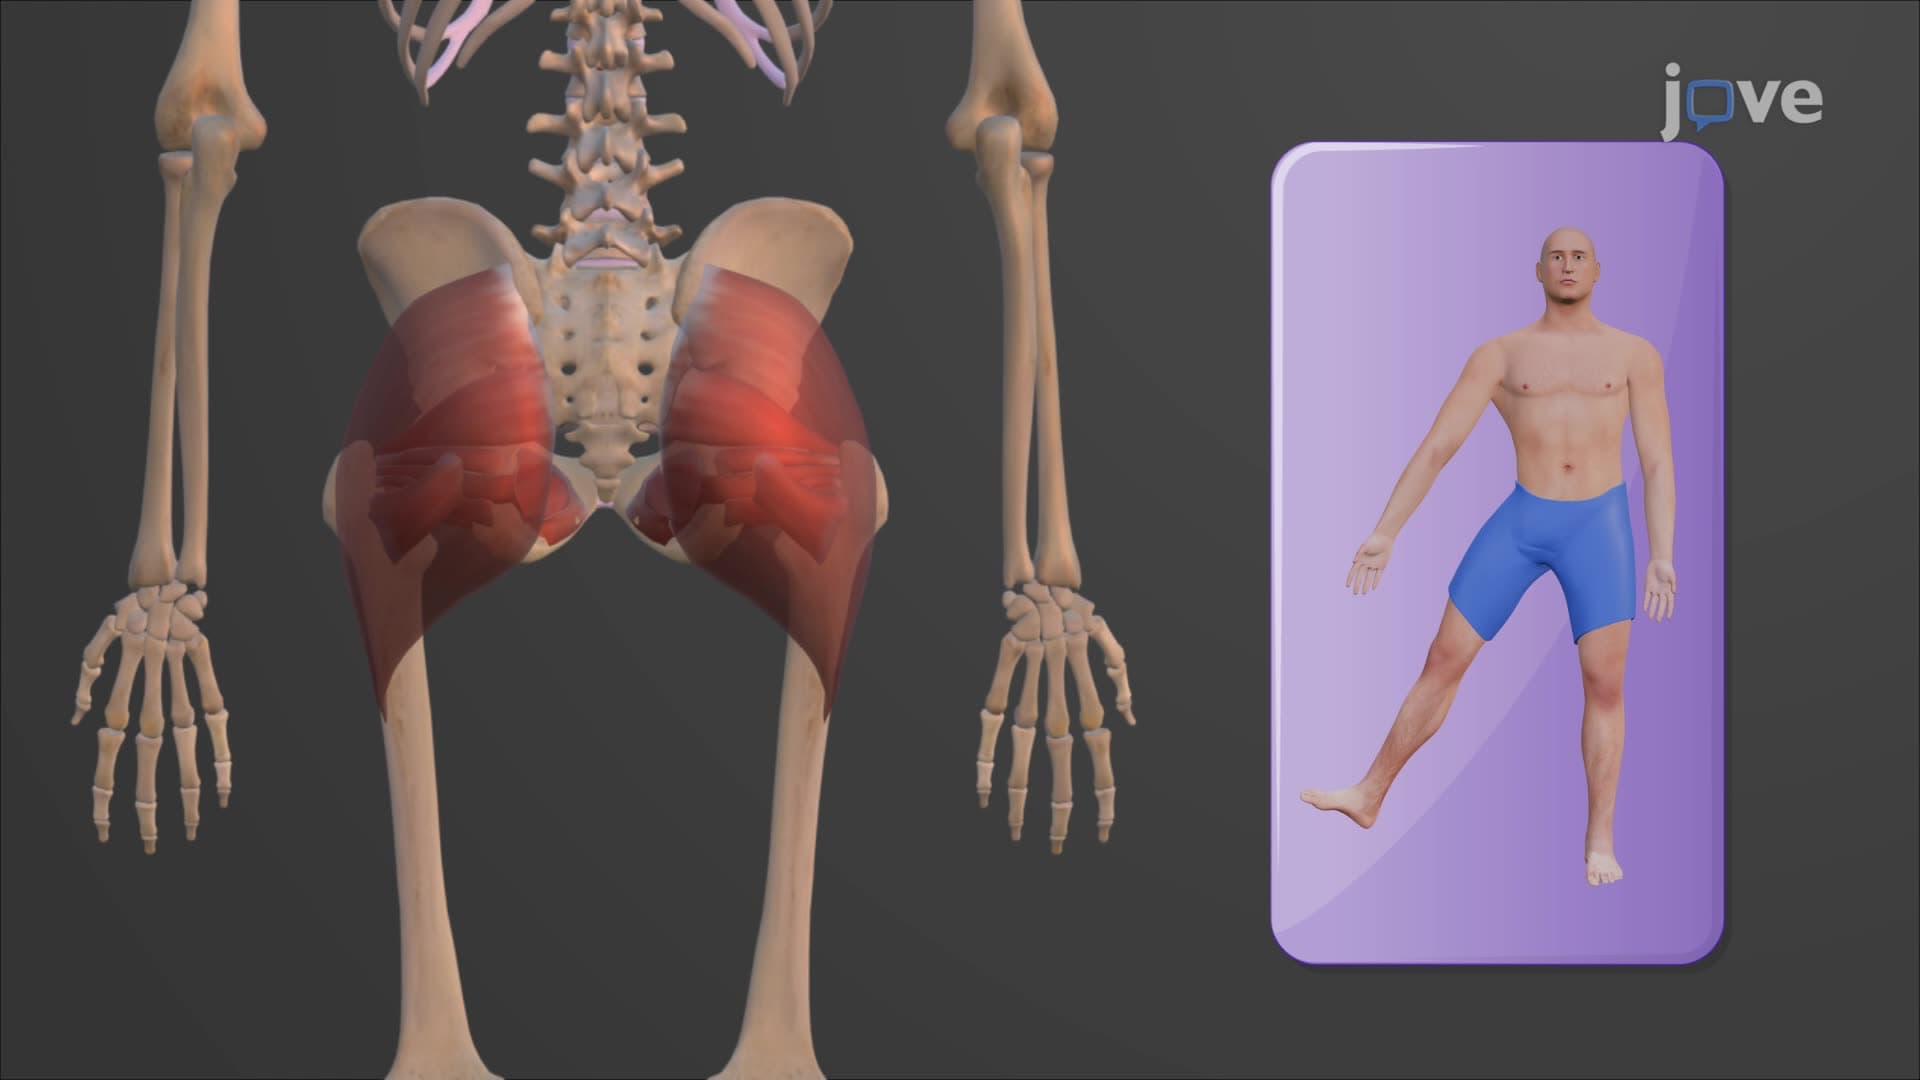
Muscles that Move the Thigh
Three other significant muscles are the gluteus maximus, gluteus medius, and gluteus minimus. The gluteus maximus originates from the posterior surface of the ilium, sacrum, and coccyx, and the thoracolumbar fascia...