Acute effects of L- and T-type calcium channel antagonists on cardiovascular reflexes in conscious rabbits
Related Experiment Video
Updated: Oct 1, 2026
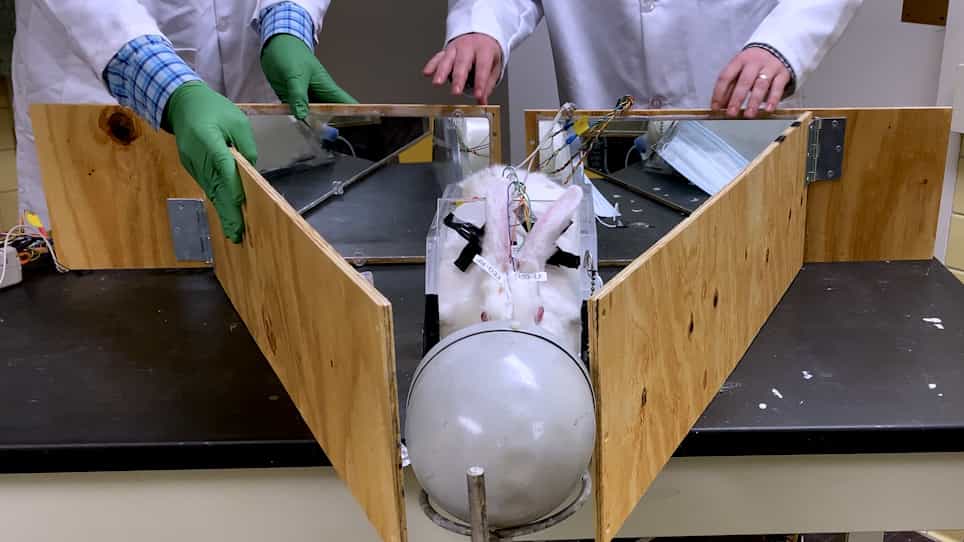
Multi-system Monitoring for Identification of Seizures, Arrhythmias and Apnea in Conscious Restrained Rabbits
Published on: March 27, 2021
Mark G Devlin1, James A Angus, Kathryn M Wilson
1Department of Pharmacology, University of Melbourne, Melbourne, Victoria, Australia.

Abstract:
1. The effects of the relatively selective T-type voltage- operated calcium channel (VOCC) antagonist mibefradil were compared with verapamil, an L-type VOCC antagonist, on a range of autonomic reflexes in conscious rabbits. 2. Mean arterial pressure (MAP), heart rate (HR), the baroreceptor-HR reflex, postural adaptation reflex (90 degrees head-up tilt), Bezold-Jarisch-like reflex and the vasoconstrictor component of the nasopharyngeal reflex were assessed before and during i.v. infusion of vehicle (saline), mibefradil or verapamil. Doses of mibefradil that gave low (M1; 0.45 +/- 0.02 microg/mL) and high (M2; 0.93 +/- 0.05 microg/mL) plasma concentrations, or verapamil (0.059 +/- 0.004 microg/mL; n = 6 each) were chosen to mimic clinically observed therapeutic levels. 3. At steady state infusion over 30-90 min, MAP was significantly lower in M2 (- 7 mmHg) and verapamil (- 6 mm Hg) treatments, but only verapamil caused a significant tachycardia (+ 31 b.p.m.) compared with vehicle. Mibefradil (M2) and verapamil decreased the HR range of the baroreflex by 27 and 29%, respectively, but neither treatment affected the vagal or sympathetic constrictor components of the Bezold-Jarisch-like and nasopharyngeal reflexes, respectively. 4. In response to 90 degrees tilt, vehicle- and verapamil-treated rabbits responded with small rises in MAP of 4 +/- 2 and 8 +/- 2 mm Hg, respectively, 5 s into the upright posture, while M1 and M2 caused falls in MAP of 6 +/- 4 and 9 +/- 3 mm Hg, respectively, at 5 s. 5. Thus, both L- and T-type VOCC antagonists, at plasma concentrations in the clinical range, lowered MAP in the conscious rabbit, but only mibefradil caused postural hypotension. We conclude that T-type VOCC may play an important role in the venoconstrictor reflex in response to tilt in the rabbit.
Insights
Both T-type and L-type calcium channel blockers lowered blood pressure in rabbits. However, mibefradil, a T-type blocker, uniquely caused postural hypotension, suggesting T-type channels are key in tilt-induced venoconstriction.
Area of Science:
- Pharmacology
- Cardiovascular Physiology
Background:
- Voltage-operated calcium channels (VOCCs) are crucial for regulating vascular tone and autonomic reflexes.
- T-type and L-type VOCCs have distinct physiological roles, but their comparative effects on autonomic reflexes are not fully understood.
Purpose of the Study:
- To compare the effects of a selective T-type VOCC antagonist (mibefradil) with an L-type VOCC antagonist (verapamil) on autonomic reflexes in conscious rabbits.
- To investigate the role of T-type VOCCs in postural adaptation and venoconstriction.
Main Methods:
- Conscious rabbits were infused intravenously with vehicle, mibefradil (low and high doses), or verapamil to achieve clinically relevant plasma concentrations.
- Autonomic reflexes assessed included mean arterial pressure (MAP), heart rate (HR), baroreceptor-HR reflex, postural adaptation (head-up tilt), Bezold-Jarisch-like reflex, and nasopharyngeal reflex.
Main Results:
- Both mibefradil and verapamil significantly reduced MAP. Verapamil, but not mibefradil, caused tachycardia.
- Mibefradil and verapamil similarly reduced the HR range of the baroreflex.
- During head-up tilt, mibefradil (both doses) induced postural hypotension, while verapamil did not significantly alter the MAP response to tilt.
Conclusions:
- Both T-type and L-type VOCC antagonists lower MAP in conscious rabbits at clinically relevant concentrations.
- T-type VOCCs appear to play a significant role in the venoconstrictor response during postural changes (tilt) in rabbits.
More Related Videos
Related Concept Videos
 01:18
Antihypertensive Drugs: Action of Calcium Channel Blockers
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:26
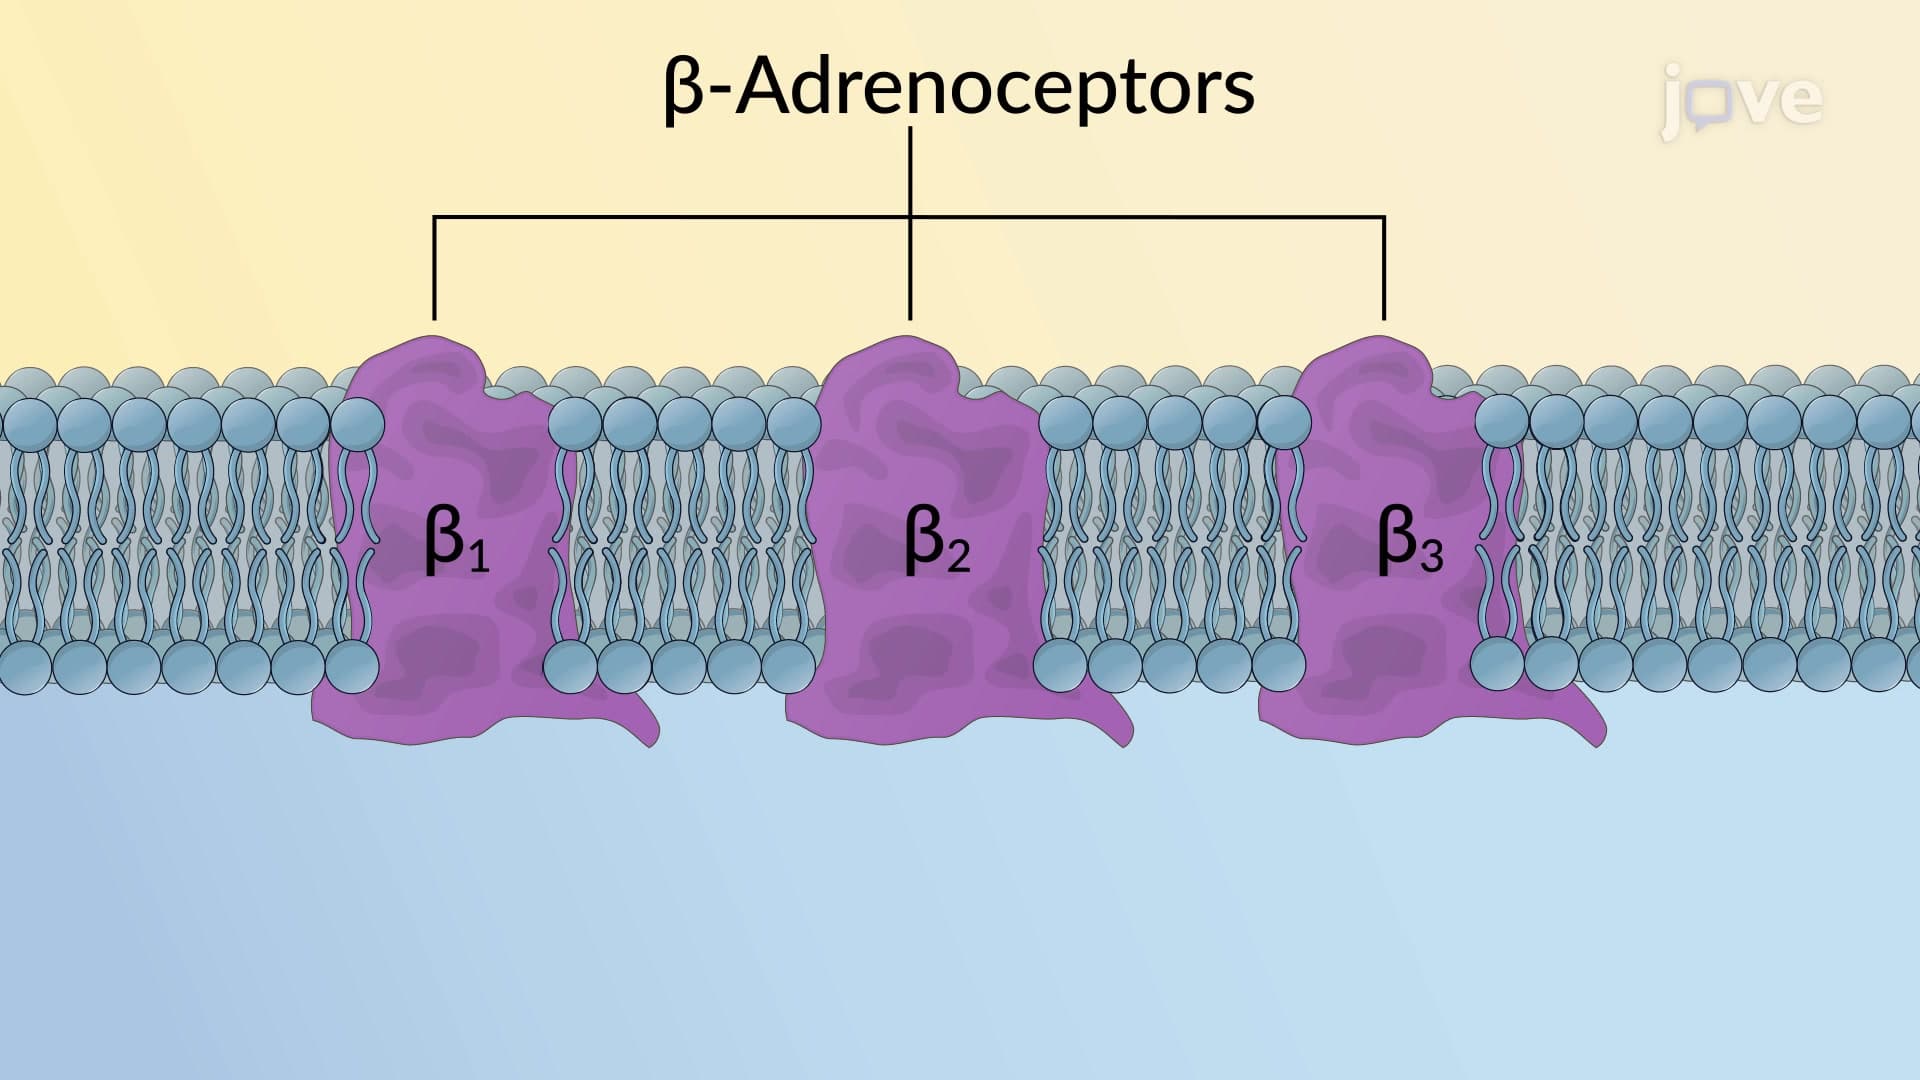
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...