Related Experiment Video
Updated: Jan 6, 2026

Author Spotlight: Advancing Therapeutic Strategies for Improving Pregnancy Rates by Analyzing Embryo-Endometrium Interactions
Published on: June 21, 2024
Progesterone therapy versus follicle maturing drugs--possible opposite effects on embryo implantation

Abstract:
Progesterone (P) is an essential hormone to allow the establishment of a pregnancy and to prevent spontaneous abortion during the first trimester. One way to treat P deficiency is simply to supplement extra P during the luteal phase and during the first trimester. Another way to increase serum P is to use follicle maturing drugs. However, these latter drugs may also cause an increase in contra-P hormones so that luteal phase deficiency is common when anovulatory women are treated with follicle maturing drugs. Improved pregnancy and especially reduced miscarriage rates, will be found when P is supplemented in the luteal phase in women requiring follicle maturing drugs. When women have fairly regular cycles and appear to be ovulating they may still have endometrial biopsies that are out of phase and be classified as having luteal phase defects (LPD). A slight majority of women with LPD make mature follicles and respond much better to supplemental P than to follicle maturing drugs. In some cases the use of follicle maturing drugs creates a hostile uterine environment possibly related to premature trophoblast invasion.


Related Concept Videos
 01:27
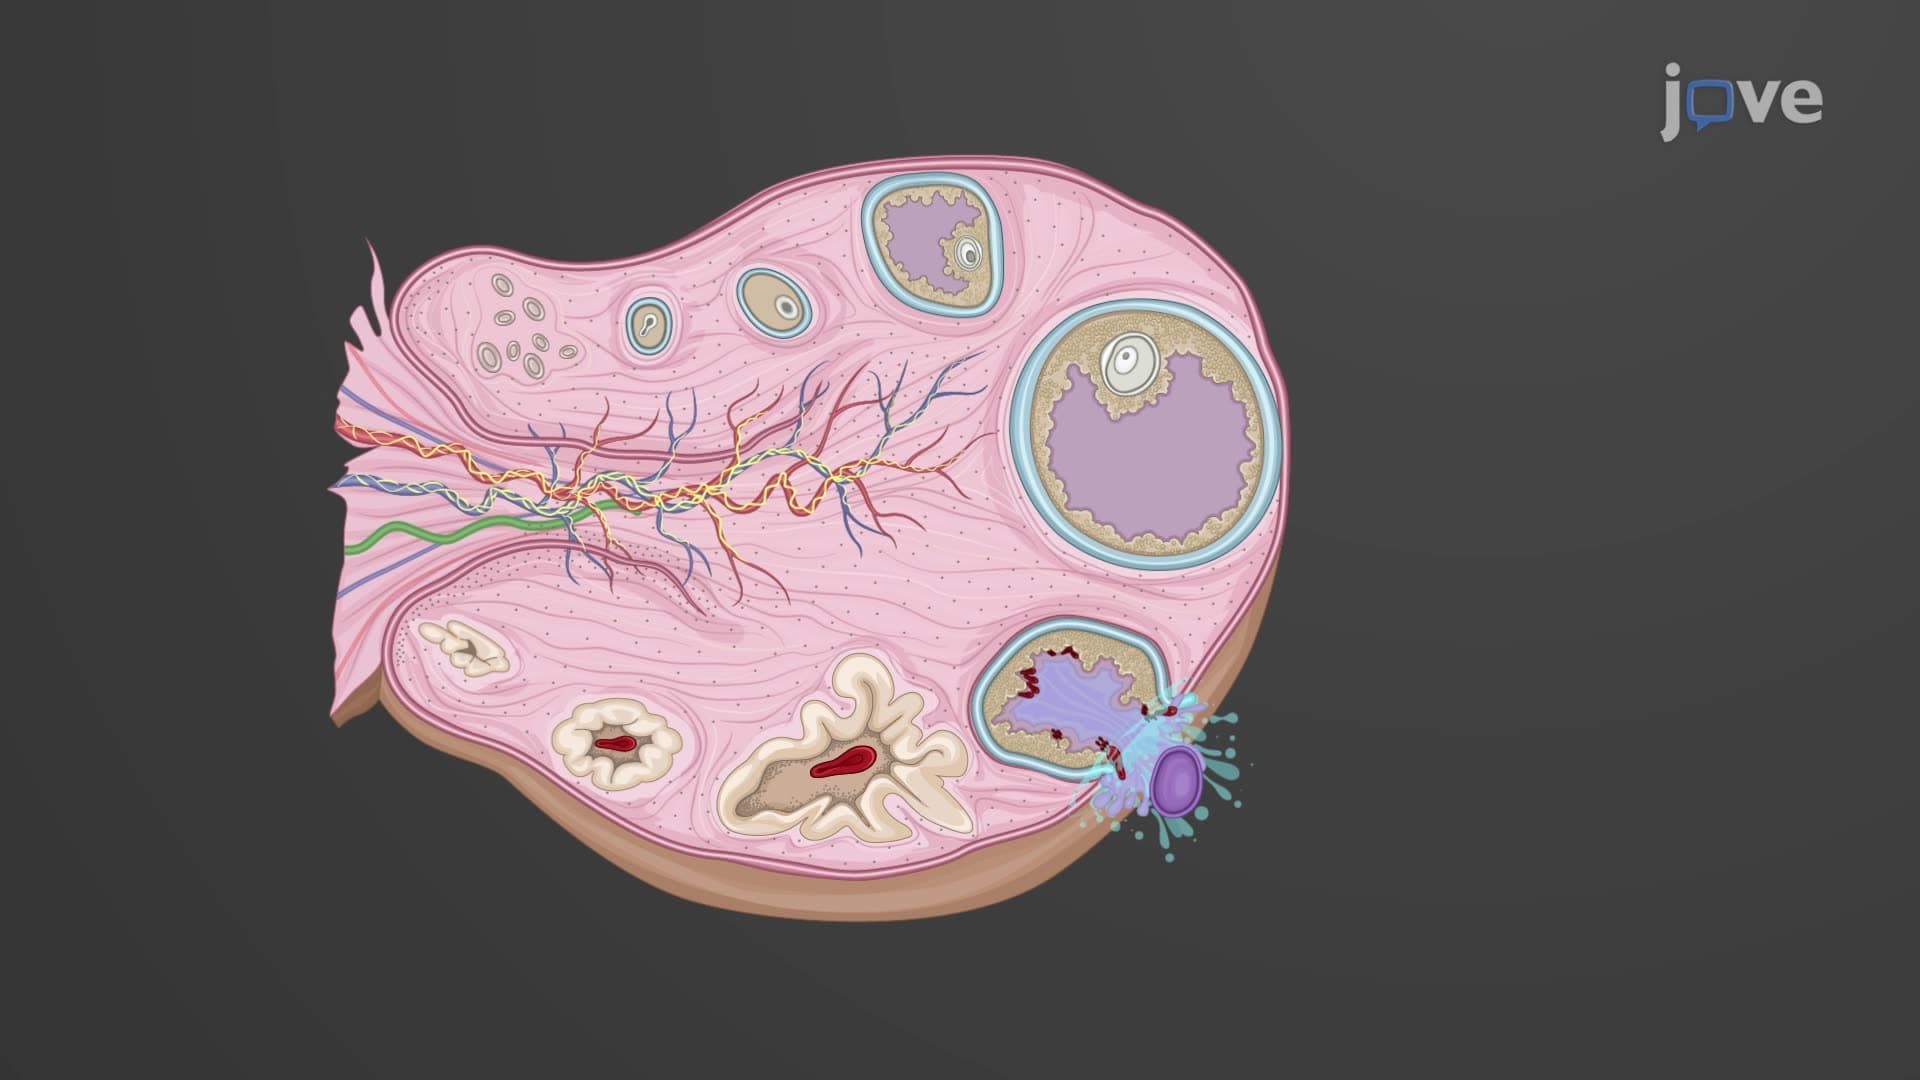
Ovarian Cycle
 01:24
In Vitro Fertilization
The IVF process begins with ovarian stimulation, during which reproductive endocrinologists prescribe hormonal medications to stimulate the ovaries to produce multiple eggs instead of the single...
 01:20
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...
 01:07
Teratogenicity
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH...