Related Experiment Video
Updated: Oct 1, 2026

Galleria mellonella as an Antimicrobial Screening Model
Published on: October 11, 2024
Comparison of once-daily versus twice-daily gentamicin dosing regimens in infants > or = 2500 g
Ghanshyam Agarwal1, Alok Rastogi, Suma Pyati
1Department of Pediatrics, Division of Neonatology, Cook County Children's Hospital, Chicago, IL, USA.

Insights
A once-daily gentamicin regimen of 4 mg/kg demonstrated superior peak serum gentamicin concentrations (SGCs) and safe trough levels in neonates compared to a twice-daily regimen. This suggests SGC monitoring may not be necessary for term infants receiving this once-daily dosing for early-onset sepsis.
Area of Science:
- Neonatal pharmacology
- Pediatric infectious diseases
- Clinical pharmacokinetics
Background:
- Gentamicin dosing regimens for neonates lack standardization.
- Optimizing gentamicin therapy is crucial for treating bacterial infections in newborns.
Purpose of the Study:
- To compare the efficacy and safety of a once-daily gentamicin dosing regimen versus a twice-daily regimen in neonates weighing >= 2500 g.
- To evaluate serum gentamicin concentrations (SGCs) and pharmacokinetic profiles of both dosing regimens.
Main Methods:
- A prospective, randomized controlled trial involving neonates >= 2500 g treated for suspected bacterial infection.
- Infants were randomized to receive either 4 mg/kg every 24 hours (study group, n=20) or 2.5 mg/kg every 12 hours (control group, n=21).
- Serum gentamicin concentrations were monitored, and pharmacokinetic parameters were calculated.
Main Results:
- The once-daily regimen achieved significantly higher peak SGCs at 30 minutes and steady state (48 hours) compared to the twice-daily regimen (p<0.001).
- A higher percentage of infants in the once-daily group achieved therapeutic peak SGCs (95% vs. 81% after first dose; higher therapeutic ranges also favored study group).
- No infants in the once-daily group had elevated trough SGCs requiring dose adjustment, unlike six infants in the control group (p=0.02).
Conclusions:
- The once-daily gentamicin regimen of 4 mg/kg is effective in achieving higher peak SGCs and safe trough concentrations in neonates compared to the standard twice-daily regimen.
- Monitoring of SGCs may not be required for term infants with normal renal function receiving a short course of once-daily gentamicin for suspected early-onset sepsis.
Objective:
There is no uniformity in the current recommendations of dosing regimen of gentamicin for neonates. We conducted a prospective, randomized, controlled trial to compare a once-daily dosing regimen to the twice-daily dosing regimen for neonates > or = 2500 g during the first 7 days after birth.
Study Design:
Infants > or = 2500 g admitted to the Neonatal Intensive Care Unit and prescribed gentamicin for suspected bacterial infection were randomized to receive either 4 mg/kg every 24 hours, study group (n=20), or a standard regimen of 2.5 mg/kg every 12 hours, control group (n=21). Serum gentamicin concentrations (SGCs) were followed and gentamicin pharmacokinetics calculated on all infants.
Results:
Peak SGC 30 minutes after the first dose was 8.2+/-1.7 microg/ml in the study group, compared to 6.4+/-1.5 microg/ml in the control group (p=0.001). Ninety-five percent of study group infants, compared to 81% of the control group, had peak SGCs in therapeutic range after the first dose. Peak SGC at 48 hours (steady state) was 8.9+/-1.5 in the study group and 6.8+/-1.1 in the control group (p=0.0001). On further analysis, a significantly higher percentage of infants in the study group, compared to the control group, had peak SGCs in higher therapeutic ranges of 6 to 12 microg/ml as well as 8 to 12 microg/ml. None of the study infants, compared to six control infants, had trough SGCs > or = 2 microg/ml at steady state. Thus, none of the study group infants, versus six of the control group infants, needed a dosing adjustment at 48 hours (p=0.02, Fisher's exact test).
Conclusion:
We found that 4 mg/kg gentamicin given every 24 hours achieved significantly higher peak SGCs and safe trough concentrations in all infants, compared to the twice-daily regimen of 2.5 mg/kg. We suggest that SGCs may not need to be followed in term infants prescribed a short course of this once-daily regimen for suspected early-onset sepsis if renal functions are normal.
Related Concept Videos
 01:15
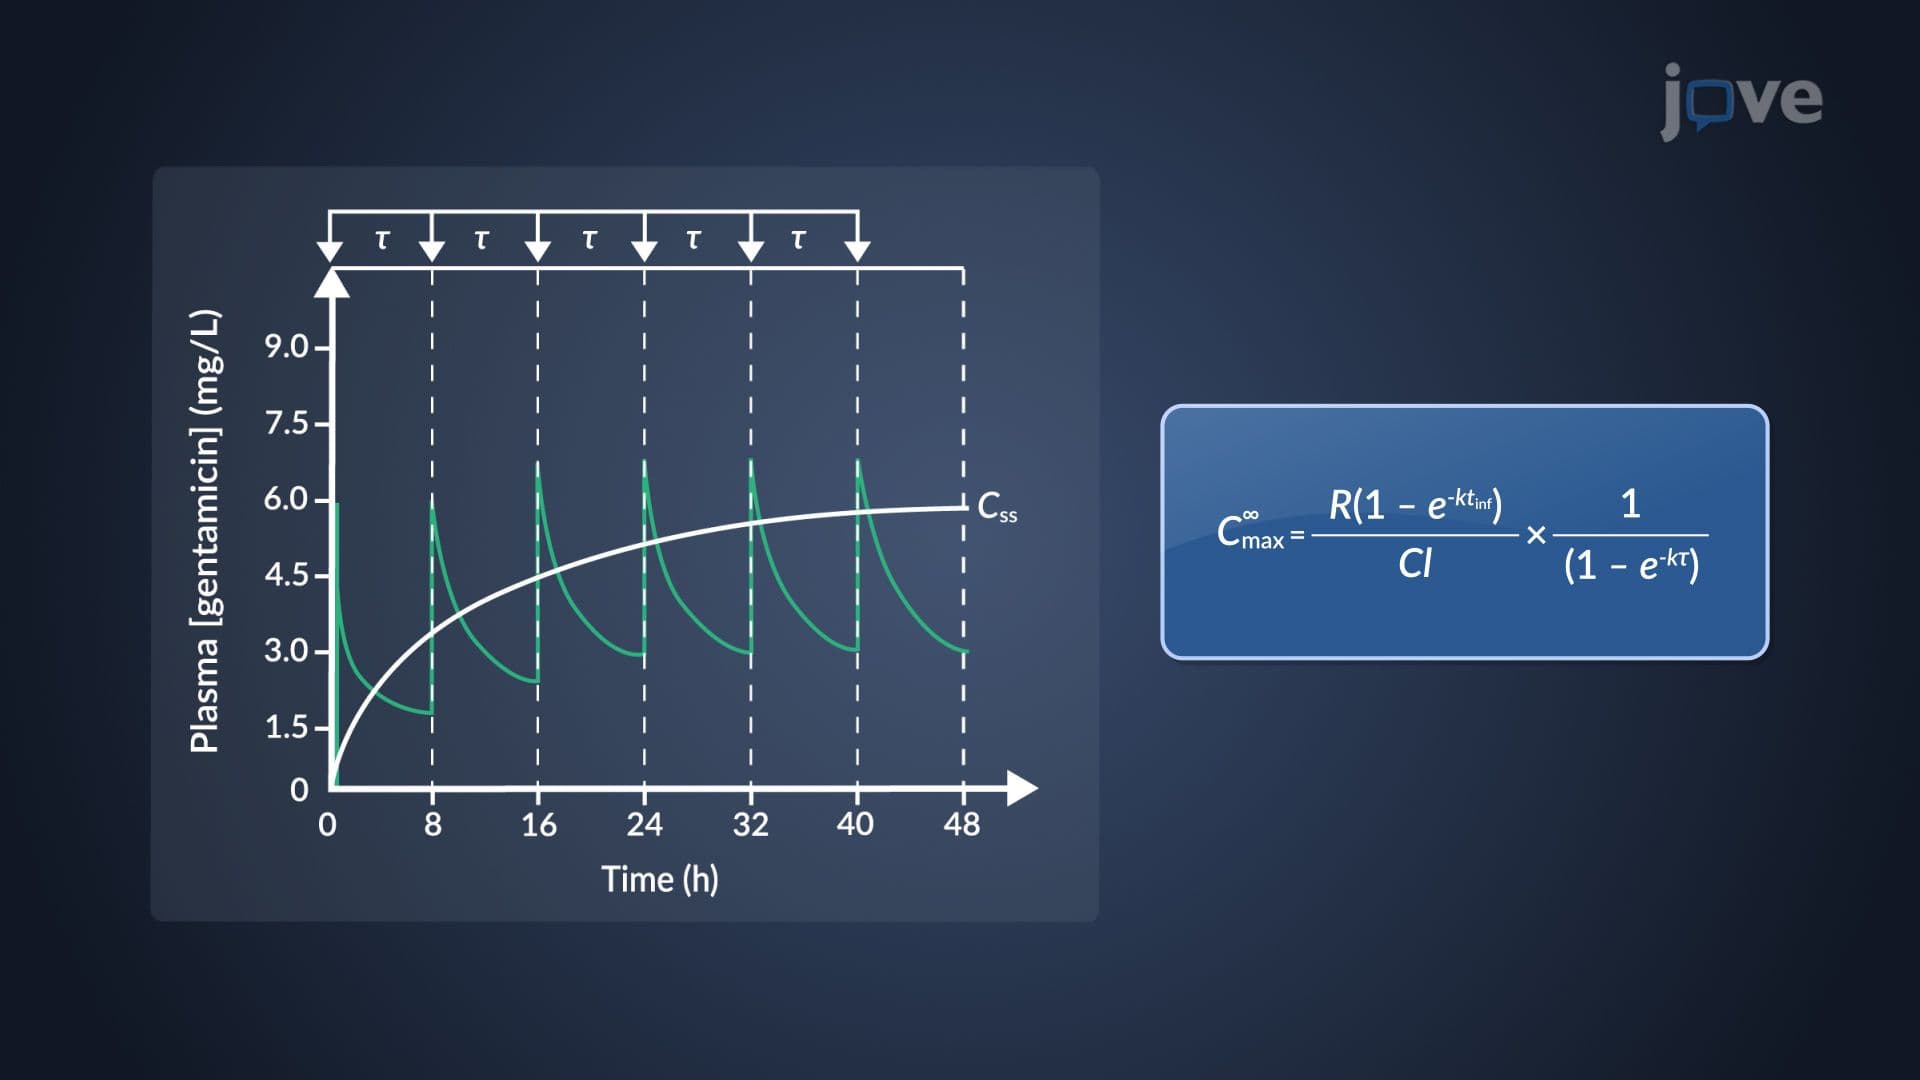
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:29
Drug Dosing: Infants and Children
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:20
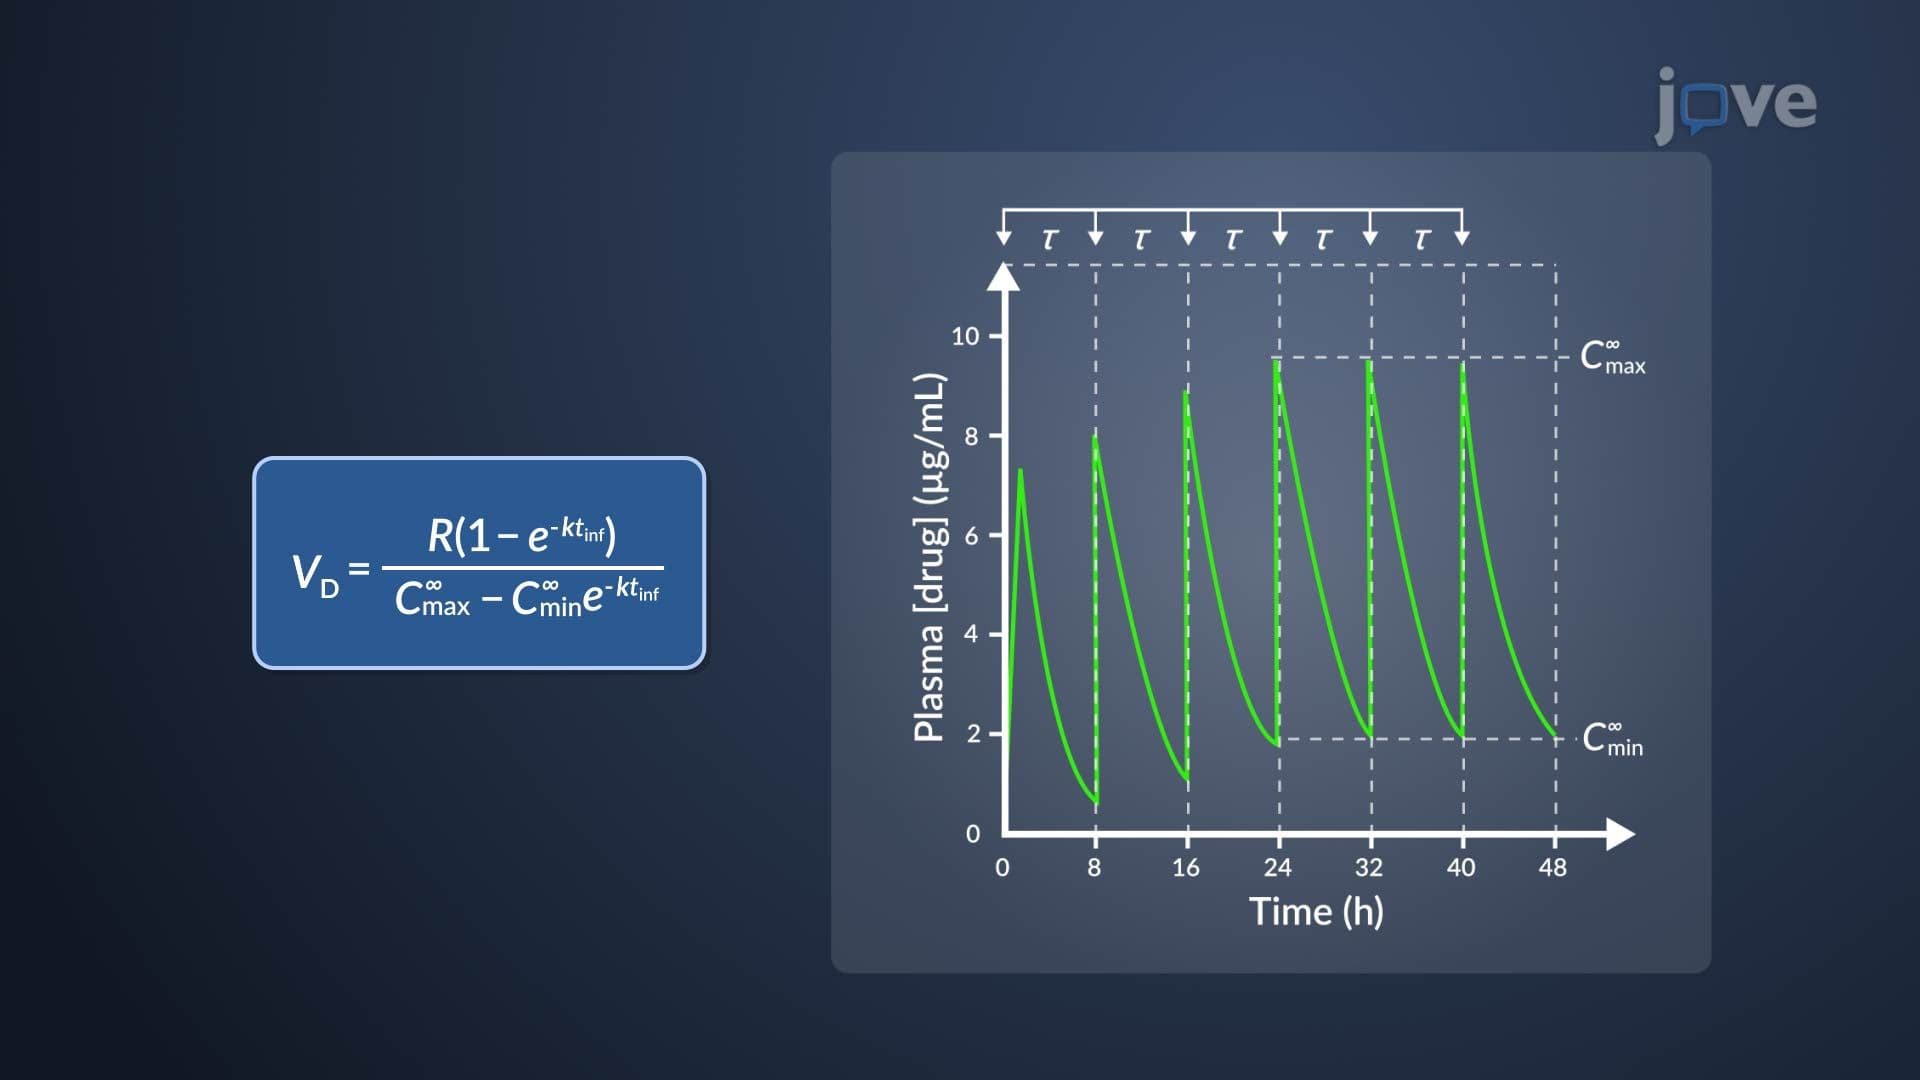
Estimation of k and VD of Aminoglycosides
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant