Resistance to vecuronium in a term neonate

A Sarti1, M Cergol, R Scarpa

  • 1Department of Anaesthesia and Intensive Care, Research and Care Children Hospital IRCCS Burlo Garofolo, Trieste, Italy. sarti@burlo.trieste.it

Related Concept Videos

Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics01:11

Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics

All neuromuscular blocking agents are injected intravenously because they are poorly absorbed from the GI tract. Rapid onset is achieved with intravenous administration, although absorption is also adequate from an intramuscular injection. Since these agents are highly ionized, they do not readily penetrate cell membranes or cross the blood-brain barrier.
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
Drug Dosing: Infants and Children01:29

Drug Dosing: Infants and Children
Pediatric patient dosages diverge from adults due to disparities in body surface area, total body water, and extracellular fluid per kilogram of body weight. The dosing regimen considers the variations in pharmacokinetics and pharmacology across distinct age groups, encompassing preterm newborns, infants, young children, older children, and adolescents. Calculation of pediatric patient doses is predicated on determining body surface area, which exhibits a superior correlation with the child's...
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action01:17

Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action

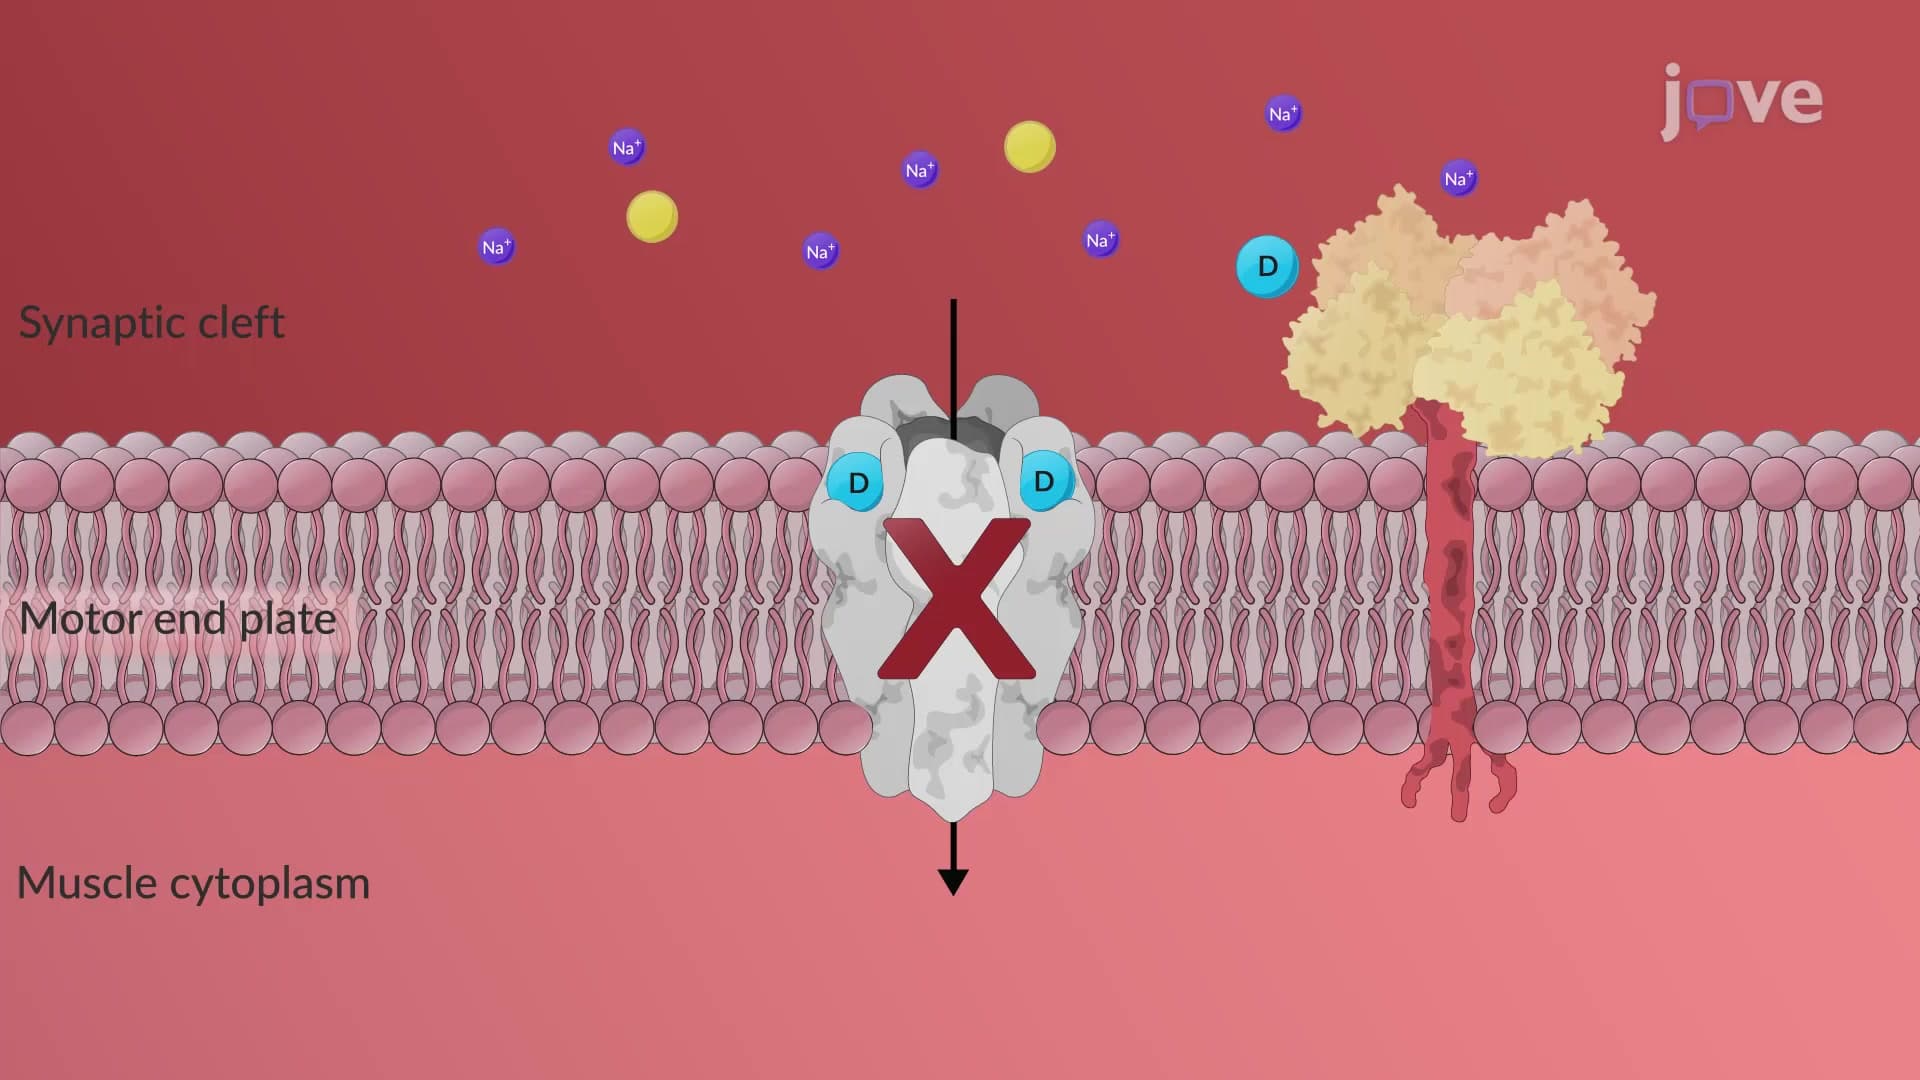
Nondepolarizing neuromuscular blockers induce paralysis by competitively blocking nicotinic acetylcholine receptors at the muscle end plate. Examples include pancuronium, mivacurium, vecuronium, and rocuronium. These quaternary ammonium derivatives are administered intravenously, are poorly absorbed, and are excreted via the kidneys.
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
Teratogenicity01:07

Teratogenicity

The ability of a drug to produce structural deformations and functional abnormalities in the developing embryo or the fetus is called teratogenicity, and the drug producing this effect is known as a teratogen. Teratogenic effects include stillbirth, miscarriage, intrauterine growth restriction, and neurocognitive delay. A teratogen may affect the embryo at different stages of development, which is important in determining the type and extent of the damage. During blastocyst formation, the early...
Depolarizing Blockers: Pharmocokinetics01:19

Depolarizing Blockers: Pharmocokinetics

Depolarizing blockers are administered through intravenous injection. Succinylcholine is the most common choice of depolarizing blockers in emergency clinical practices. Although they have a rapid onset, they readily diffuse away from the motor end plate into the extracellular fluid. They are metabolized by enzymes such as liver butyrylcholinesterase and plasma pseudocholinesterases. This produces a short duration of action, typically 5-10 minutes long, unlike nondepolarizing blockers, which...
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions01:27

Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions

Nondepolarizing neuromuscular blockers prevent the membrane depolarization of muscle cells and inhibit muscle contraction. These are usually administered with anesthetics to achieve complete muscle relaxation. Upon administration, these drugs first block the small, rapidly contracting muscles of the face and hands, followed by the larger muscles of the trunk and the intercostal muscles. The diaphragm is the last muscle to be affected.
Although all competitive neuromuscular blockers are designed...