Related Experiment Video
Updated: Aug 7, 2026
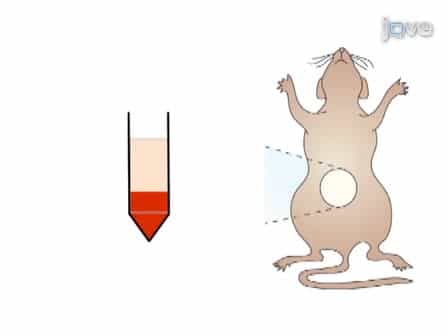
Colon Ascendens Stent Peritonitis (CASP) - a Standardized Model for Polymicrobial Abdominal Sepsis
Published on: December 18, 2010
Procalcitonin and proinflammatory cytokine clearance during continuous venovenous haemofiltration in septic patients
A A Dahaba1, G A Elawady, P H Rehak
1Department of Anaesthesiology and Intensive Care Medicine, Karl Franzens University, Graz, Austria.

Insights
Continuous venovenous hemofiltration (CVVH) effectively removes inflammatory markers like procalcitonin (PCT) and interleukins in septic patients. However, membrane saturation can decrease removal efficiency over time.
Area of Science:
- Critical Care Medicine
- Nephrology
- Immunology
Background:
- Procalcitonin (PCT), IL-6, TNF-alpha, and IL-1beta are key prognostic markers in ICU sepsis.
- Multi-organ failure in septic patients necessitates advanced treatment strategies.
Purpose of the Study:
- To evaluate the efficacy of continuous venovenous hemofiltration (CVVH) with an AN69 membrane in eliminating PCT, TNF-alpha, IL-6, and IL-1beta.
- To assess the impact of CVVH on plasma concentrations of these inflammatory mediators in septic patients.
Main Methods:
- Studied 13 septic patients with multi-organ failure undergoing CVVH.
- Measured plasma concentrations of PCT, IL-6, TNF-alpha, and IL-1beta at 0, 6, and 12 hours during CVVH.
- Analyzed ultrafiltrate for the presence of these mediators.
Main Results:
- CVVH significantly reduced plasma levels of PCT, IL-6, and TNF-alpha.
- These mediators were detected in the ultrafiltrate, confirming their removal.
- Plasma clearance decreased after 12 hours due to membrane saturation.
- IL-1beta was less consistently detected in plasma and ultrafiltrate.
Conclusions:
- CVVH effectively removes PCT, IL-6, and TNF-alpha in septic patients.
- Awareness of potential modification of prognostic marker levels by CVVH is crucial.
- CVVH may be a valuable tool for removing pro-inflammatory mediators when indicated in sepsis.
Abstract:
Procalcitonin (PCT), interleukin-6 (IL-6), tumour necrosis factor a (TNFalpha), and interleukin-1beta (IL-1beta) are important clinical prognostic markers in ICU septic patients. The goal of the study was to determine whether continuous venovenous haemofiltration (CWH), using an AN69 haemofilte, leads to elimination of PCT, TNFalpha, IL-6 and IL-1beta in 13 septic patients with multi-organ failure. At the start of haemofiltration (0), 6 and 12 hours the mean afferent plasma concentration +/- SD of PCT (10.1 +/- 9.1, 7 +/- 6, 5.9 +/- 5.7 ng/ml), IL-6 (804.6 +/- 847.6, 611.7 +/- 528.4, 575.2 +/- 539.2 pg/ml), and that of TNFalpha (4.5 +/- 2.6, 4 +/- 3.1, 3.8 +/- 2.9 pg/ml) significantly declined during CVVH. The efferent plasma concentrations were significantly lower than the corresponding afferent concentrations. PCT; IL-6 and TNFalpha were detectable in the ultrafiltrate of all patients. IL-1beta was only detectable in the plasma of eight patients and the ultrafiltrate of five patients. The plasma clearance of PCT, IL-6 and TNFalpha significantly decreased after 12 hours as a result of a decline in the adsorptive elimination of the mediators due to progressive membrane saturation. We demonstrated that if PCT, IL-6 and TNFalpha are used as clinical prognostic markers in septic patients who are treated with CWIH using an AN69 membrane, one should be aware that their plasma level could be modified by the therapy. In addition CWH could represent an appropriate tool to remove a broad spectrum of proinflammatory mediators, if such removal is required in septic patients.

Related Concept Videos
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Continuous Renal Replacement Therapy
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:25
Acute Inflammation III: Local and Systemic Effects