Related Experiment Video
Updated: Aug 12, 2026


International Expert Consensus and Recommendations for Neonatal Pneumothorax Ultrasound Diagnosis and Ultrasound-guided Thoracentesis Procedure
Published on: March 12, 2020
Thoracoscopic-assisted management of postpneumonic empyema in children refractory to medical response
1Department of Thoracic and Cardiovascular Surgery, Chang Gung Memorial Hospital, Chang Gung University, 199 Tun-Hwa N Road, Taipei, Taiwan 105. hpliu125@ms21.hinet.net

Insights
Video-assisted thoracic surgery (VATS) effectively treats pediatric empyema when medical management fails. This minimally invasive approach offers safe and rapid recovery for children with complicated chest infections.
Area of Science:
- Pediatric Surgery
- Thoracic Surgery
- Infectious Diseases
Background:
- Pediatric empyema often requires surgical intervention in advanced stages.
- Video-assisted thoracic surgery (VATS) is explored for children unresponsive to medical treatment.
Purpose of the Study:
- To evaluate the efficacy and safety of VATS in managing pediatric postpneumonic empyema.
Main Methods:
- Retrospective review of 51 pediatric patients (mean age 5 years) with loculated empyema.
- All patients underwent debridement and empyema cavity evacuation via VATS.
Main Results:
- Mean operative time was 90 minutes with 70 cc blood loss.
- All patients experienced fever resolution within 72 hours post-surgery.
- Mean postoperative hospital stay was 13.7 days; no deaths occurred.
Conclusions:
- VATS is a safe and effective treatment for pediatric empyema.
- Thoracoscopic surgery enhances visualization and debridement of infected lung tissue.
- Early VATS intervention can shorten hospitalization and accelerate recovery.
Background:
Empyema frequently complicates the hospitalization of children; and in advanced stages, it often requires surgical intervention. In this study, we investigated the use of video-assisted thoracic surgery (VATS) for the management of postpneumonic empyema in children who have had an unsatisfactory medical response.
Methods:
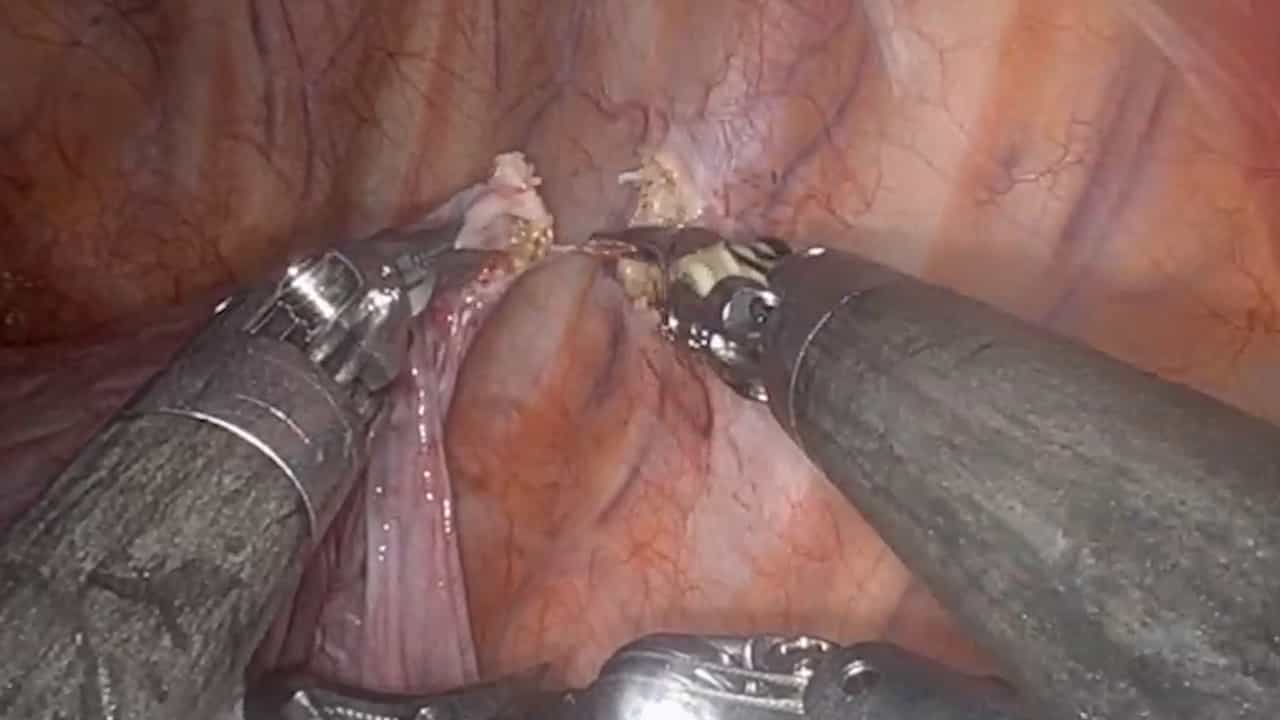
We did a retrospective review of the medical records of 51 consecutive patients with loculated empyema (mean age, 5 years; range, 2 months to 15 years) hospitalized at Chang Gung Memorial Hospital between 1995 and 2000. All patients underwent debridement of the necrotic lung tissue and evacuation of the loculated empyema cavity using a VATS approach.
Results:
The mean operating time for the 51 patients was 90 min (range, 50-210); mean blood loss was 70 cc. Fever subsided within 72 h postoperatively in all patients. On average, chest tubing was removed on the 7th postoperative day (range, 4-18 days). However, in one patient who suffered from a prolonged air leak, the chest tube was not removed until day 18. The mean postoperative stay for all patients was 13.7 days (range, 9-23). No deaths occurred, and all of the children made a good recovery. A follow-up revealed that one of the 51 children patient suffered a left upper lung abscess 7 months after discharge. Left upper lobectomy was performed in this case, and the patient was discharged uneventfully 10 days after the operation.
Conclusions:
VATS is a safe and effective treatment for pediatric empyema. Thoracoscopic-assisted surgery facilitates visualization, evacuation, and debridement of the necrotizing lung tissue. Early surgical intervention can avoid lengthy hospitalization and prolonged intravenous antibiotic therapy, and it can accelerate clinical recovery.

Related Concept Videos
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...