Assessment of ventilatory sensitivity to carbon dioxide changes during orthostasis
Related Experiment Video
Updated: Sep 30, 2026
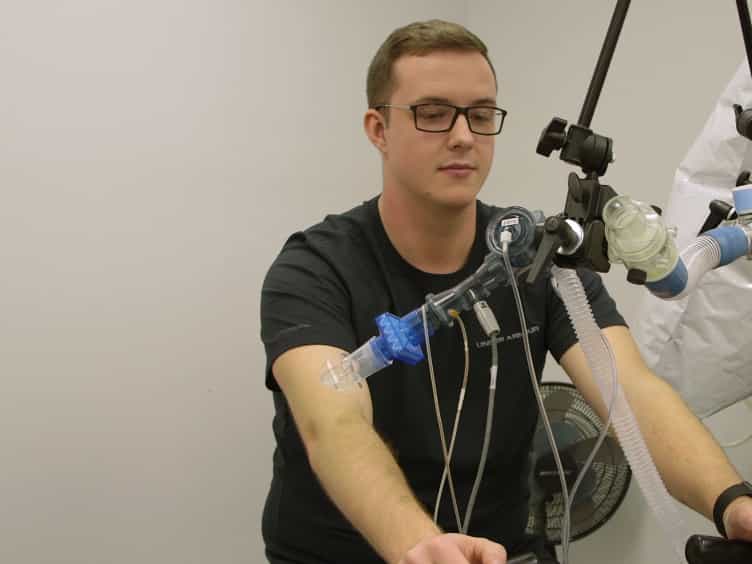
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Letetia Richardson1, Zbigniew Topor, Divyesh Bhakta
1Center for Biomedical Engineering, University of Kentucky, Lexington, KY 40506-0070, USA.

Abstract:
Investigators have anecdotally reported changes in respiratory pattern preceding symptoms of orthostatic intolerance for several years. Evidence from recent studies support these observations, and show that alterations in respiration often precede pre-syncope during orthostasis. These observations suggest the possibility that changes in interaction between the chemo and baro-reflex control systems may produce phasic or dynamic changes in respiratory and hemodynamic parameters such that these changes are important in orthostasis intolerance. Our objective in the present study was to develop a method to obtain a quantitative index of ventilatory sensitivity to changes in inspired during orthostasis. Based on an approach previously developed by one of the authors (EB), we used, during supine and 70 degrees head up tilt, pseudo-random binary changes in inspired CO2 to quantify ventilatory sensitivity to CO2 disturbances. A pneumotach was used to measure airflow. From these recordings, we used a prediction error based systems identification algorithm to quantify ventilatory impulse response to CO2 stimulus. Results from 7 subjects showed that the integrated ventilatory response (area under impulse response curve) to CO2 was larger during tilt than that during supine (mean [std] 5.3 [2.6] Vs 3.0 [1.6] ml/min/0.01LCO2). These results suggest that the changes in ventilation due to disturbances in CO2 are likely to be larger during orthostasis than those during supine. Such an elevated response would indicate that the role of chemo-reflex control of breathing in cardiovascular instability culminating in orthostatic intolerance is likely to be important and should be further investigated.

Related Concept Videos
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:31
Chemical Factors Affecting Respiration Centers
CO2 has a potent influence on respiration and is strictly regulated. Under...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and HCO3− values are examined to...