Related Experiment Video
Updated: Jul 18, 2026


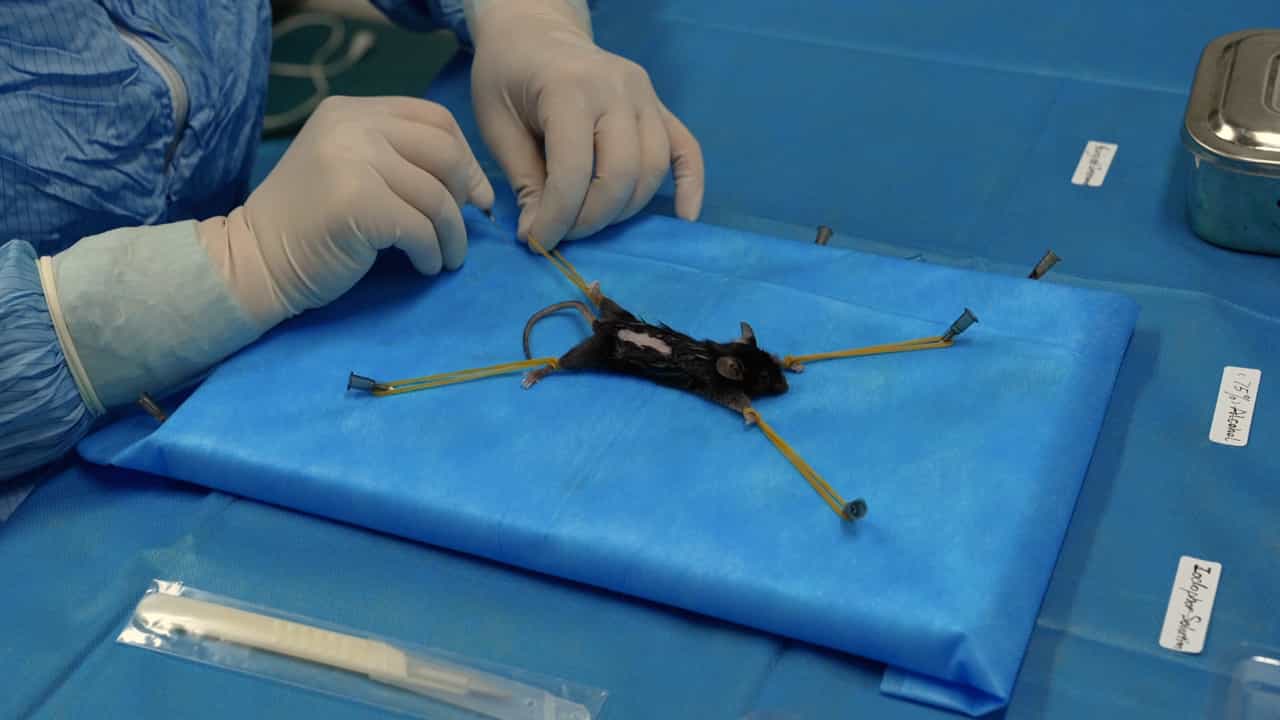
A Method to Study the Impact of Chemically-induced Ovarian Failure on Exercise Capacity and Cardiac Adaptation in Mice
Published on: April 7, 2014
Cardiovascular disease outcomes during 6.8 years of hormone therapy: Heart and Estrogen/progestin Replacement Study
Deborah Grady1, David Herrington, Vera Bittner
1Department of Epidemiology and Biostatistics, University of California, San Francisco, 74 New Montgomery St, Suite 600, San Francisco, CA 94105, USA. dgrady@itsa.ucsf.edu

Context:
The Heart and Estrogen/progestin Replacement Study (HERS) found no overall reduction in risk of coronary heart disease (CHD) events among postmenopausal women with CHD. However, in the hormone group, findings did suggest a higher risk of CHD events during the first year, and a decreased risk during years 3 to 5.
Objective:
To determine if the risk reduction observed in the later years of HERS persisted and resulted in an overall reduced risk of CHD events with additional years of follow-up.
Design And Setting:
Randomized, blinded, placebo-controlled trial of 4.1 years' duration (HERS) and subsequent unblinded follow-up for 2.7 years (HERS II) conducted at outpatient and community settings at 20 US clinical centers.
Participants:
A total of 2763 postmenopausal women with CHD and average age of 67 years at enrollment in HERS; 2321 women (93% of those surviving) consented to follow-up in HERS II.
Intervention:
Participants were randomly assigned to receive 0.625 mg/d of conjugated estrogens and 2.5 mg of medroxyprogesterone acetate (n = 1380), or placebo (n = 1383) during HERS; open-label hormone therapy was prescribed at personal physicians' discretion during HERS II. The proportions with at least 80% adherence to hormones declined from 81% (year 1) to 45% (year 6) in the hormone group, and increased from 0% (year 1) to 8% (year 6) in the placebo group.
Main Outcome Measures:
The primary outcome was nonfatal myocardial infarction and CHD death. Secondary cardiovascular events were coronary revascularization, hospitalization for unstable angina or congestive heart failure, nonfatal ventricular arrhythmia, sudden death, stroke or transient ischemic attack, and peripheral arterial disease.
Results:
There were no significant decreases in rates of primary CHD events or secondary cardiovascular events among women assigned to the hormone group compared with the placebo group in HERS, HERS II, or overall. The unadjusted relative hazard (RH) for CHD events in HERS was 0.99 (95% confidence interval [CI], 0.81-1.22); HERS II, 1.00 (95% CI, 0.77-1.29); and overall, 0.99 (0.84-1.17). The overall RHs were similar after adjustment for potential confounders and differential use of statins between treatment groups (RH, 0.97; 95% CI, 0.82-1.14), and in analyses restricted to women who were adherent to randomized treatment assignment (RH, 0.96; 95% CI, 0.77-1.19).
Conclusions:
Lower rates of CHD events among women in the hormone group in the final years of HERS did not persist during additional years of follow-up. After 6.8 years, hormone therapy did not reduce risk of cardiovascular events in women with CHD. Postmenopausal hormone therapy should not be used to reduce risk for CHD events in women with CHD.
More Related Videos

Related Concept Videos
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:22
Heart Failure VI: Adjunct Therapies
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care
 01:29
Cardiomyopathy VI: Nursing Management