Related Experiment Video
Updated: Sep 30, 2026
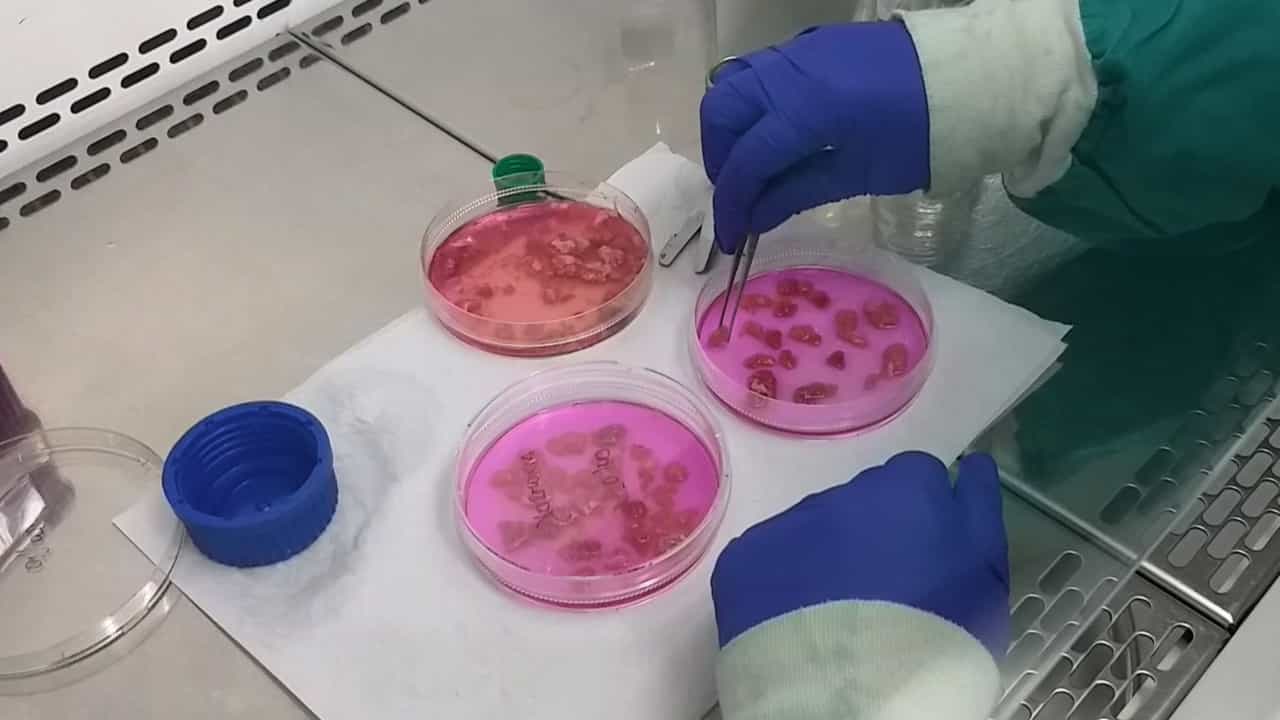
Disruption of the Mouse Blood-Brain Barrier by Small Extracellular Vesicles from Hypoxic Human Placentas
Published on: January 26, 2024
Hypertension in pregnancy and preeclampsia. Knowledge and clinical practice among obstetrician-gynecologists
John T Repke1, Michael L Power, Gerald B Holzman
1Department of Obstetrics and Gynecology, University of Nebraska Medical Center, 983255 Nebraska Medical Center, Omaha, NE 68198-3255, USA. jrepke@unmc.edu

Objective:
To examine the knowledge and practice patterns of obstetrician-gynecologists concerning management of hypertensive disorders of pregnancy.
Study Design:
Surveys were mailed to 1,116 fellows of the American College of Obstetrics and Gynecology; 416 of them constituted the Collaborative Ambulatory Research Network. Seven hundred more were chosen at random. The survey contained questions on physician and patient demography and on knowledge and practice patterns concerning management of various hypertensive disorders during pregnancy.
Results:
A total of 401 completed surveys were analyzed. There was no difference between respondents and nonrespondents in either sex ratio (P = .410) or age (46.9 +/- 0.4 versus 48.1 +/- 0.4 years, P = .131). Most respondents (84.5%) would manage mild preeclampsia on an outpatient basis, and most (58.6%) usually managed preeclampsia independently. There was considerable variation in clinical practice. For example, about one of four respondents (27.4%) do not use seizure prophylaxis during labor in mild preeclampsia. Among physicians who do utilize magnesium sulfate for seizure prophylaxis, the mean standard loading dose was 4.5 +/- .1 g intravenously. More than half the respondents (54.9%) would employ preeclampsia prevention procedures. Most respondents (74.6%) said that there is a role for management of severe preeclampsia remote from term. Intrauterine growth restriction would be used as an indication for immediate delivery by 60.6% of respondents; female physicians were more likely to use intrauterine growth retardation as an indication for immediate delivery (chi 2 = 5.7, P = .017).
Related Concept Videos
 01:29
Hypertension II: Pathophysiology
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:18
Hypertension and Regulation of Blood Pressure
 01:28
Hypertension I: Introduction
 01:23
Hypertension V: Nursing Management
 01:33
Hormonal Regulation