Chromogranin 'A' in normal subjects, essential hypertensives and adrenalectomized patients
Related Experiment Video
Updated: Sep 30, 2026
A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Bernini Giampaolo1, Moretti Angelica, Salvetti Antonio
1Department of Internal Medicine, University of Pisa, Italy. g.bernini@med.unipi.it

Objective:
Chromogranin A (CgA) is an acidic glycoprotein co-stored in vesicles and co-released with catecholamines. Although currently used as a humoral marker of endocrine tumours, several aspects of CgA secretion still need to be clarified in humans.
Patients:
Fifty-four controls, 83 essential hypertensive and six adrenalectomized patients were studied.
Design:
In the controls and hypertensive patients, CgA and catecholamines were measured before (supine position) and after changes in posture (2' upright position), insulin-induced hypoglycaemia (0.15 IU/kg i.v.) and glucagon injection (1 mg i.v.). In addition, blood samples were taken in the morning (0800 h) and in the afternoon (1800 h), and every 5 h for 24 h. In the adrenalectomized patients, blood samples were obtained in the morning and in the afternoon.
Measurements:
CgA was measured by an immunoradiometric assay, and noradrenaline and adrenaline by high-performance liquid chromatography.
Results:
In controls, posture slightly increased plasma catecholamines without affecting CgA levels. Hypoglycaemia evoked a rise in noradrenaline (P < 0.04), adrenaline (P < 0.01) and CgA (79.6 +/- 11.8 vs. 46.1 +/- 10.1 microg/l, P < 0.03). Glucagon injection increased plasma adrenaline (P < 0.01) but not noradrenaline or CgA levels. At variance with blood pressure and catecholamines, CgA increased significantly in the afternoon (51.1 +/- 4.0 vs. 45.0 +/- 3.9 microg/l, P < 0.05); it also had a circadian rhythm, with peak values during the night (at 2300 h, 65.4 +/- 9.0 microg/l) and a nadir in the morning (at 0800 h, 43.1 +/- 6.6 microg/l). In hypertensives, basal and stimulated CgA levels as well as diurnal/circadian variations of this peptide were similar to those in normal subjects. In adrenalectomized patients plasma CgA in the morning (34.3 +/- 6.5 microg/l) was lower (P < 0.03) than in all controls and hypertensives studied, but also showed an afternoon increment (46.4 +/- 6.6 microg/l, P < 0.003). No correlation was found between CgA and catecholamines or blood pressure in all subjects or in the subgroups.
Conclusions:
In normal humans, chromogranin A and catecholamines are not always co-secreted, and co-secretion occurs only for marked exocytotic adrenergic stimuli, such as hypoglycaemic stress. In addition, chromogranin A has a circadian rhythm unrelated to plasma catecholamines. Basal plasma concentrations and the secretory pattern of chromogranin A in hypertensives do not differ from the findings in controls. Finally, the adrenal glands contribute partially to circulating chromogranin A and are not involved in the circadian rhythm of this peptide in humans.

Related Concept Videos
 01:26
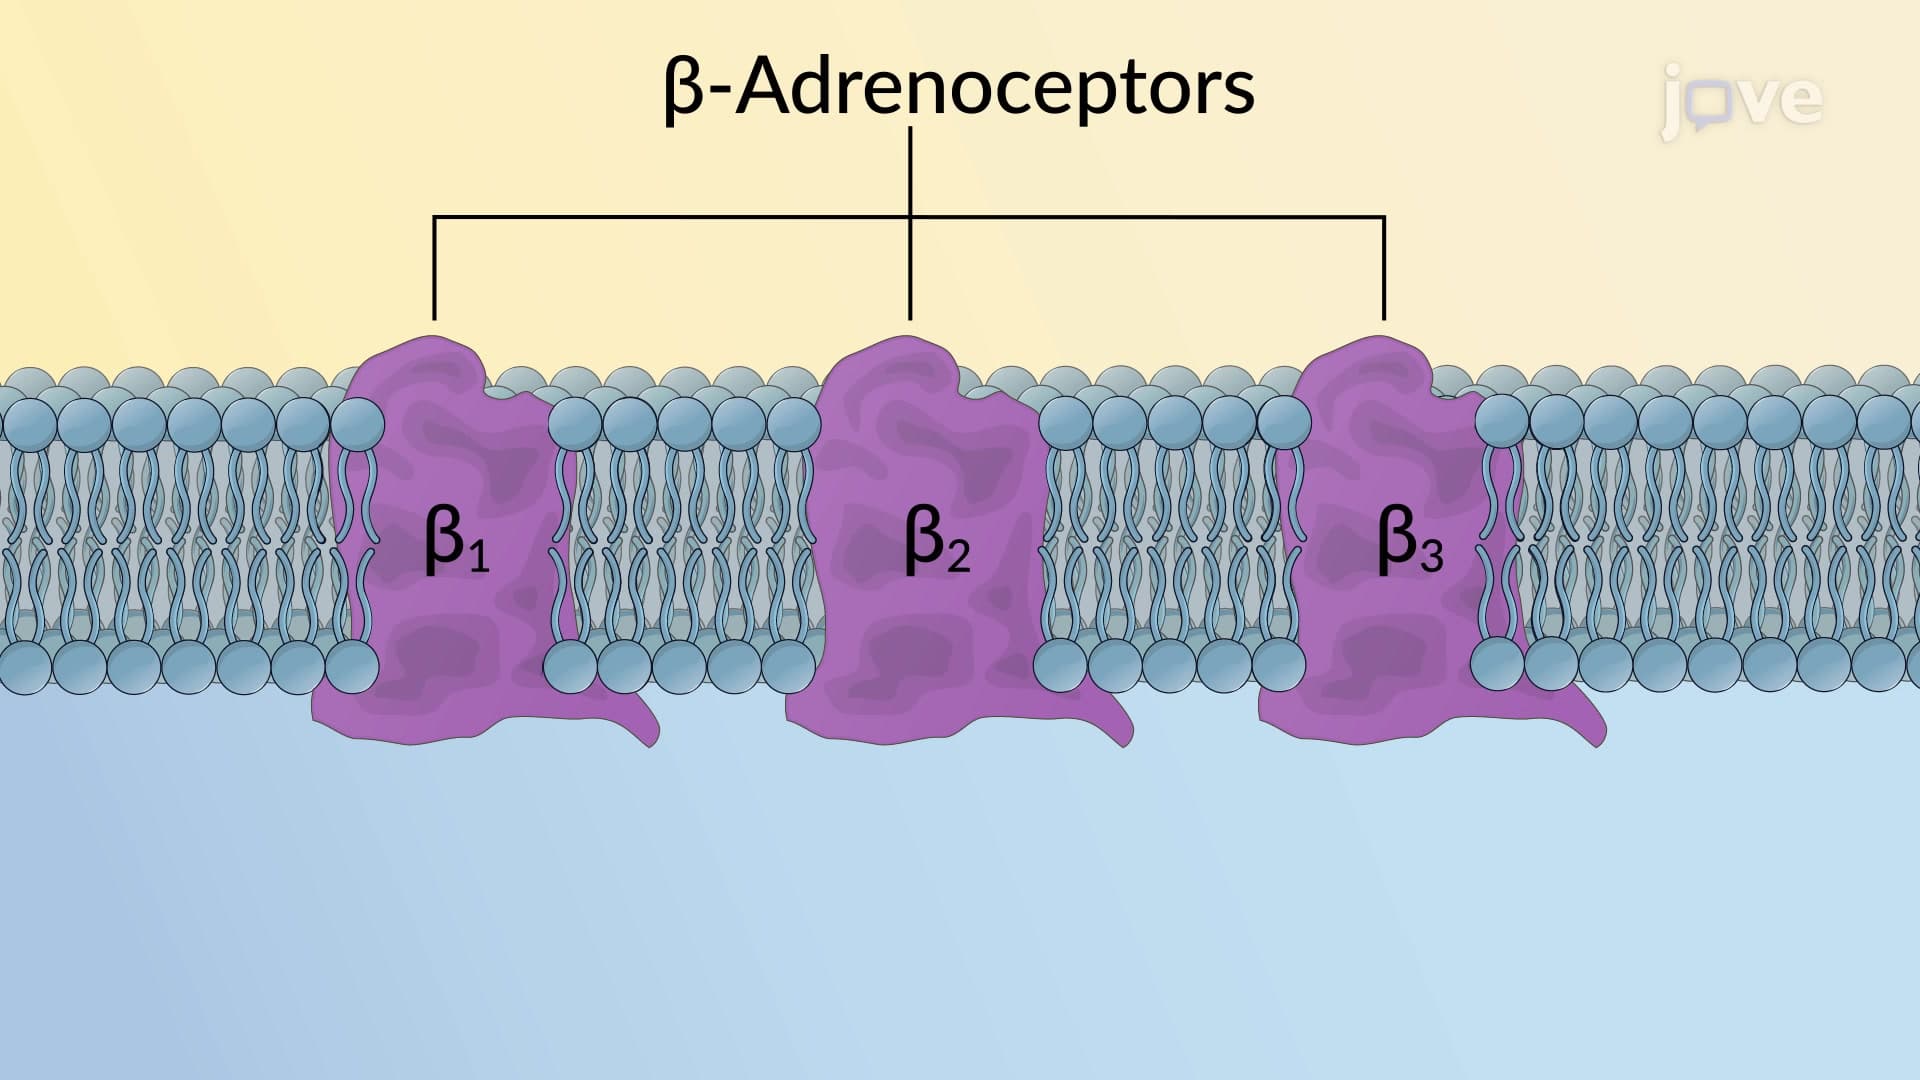
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:17
Antihypertensive Drugs: Action of β1 Blockers
 01:31
Hormones of the Adrenal Glands
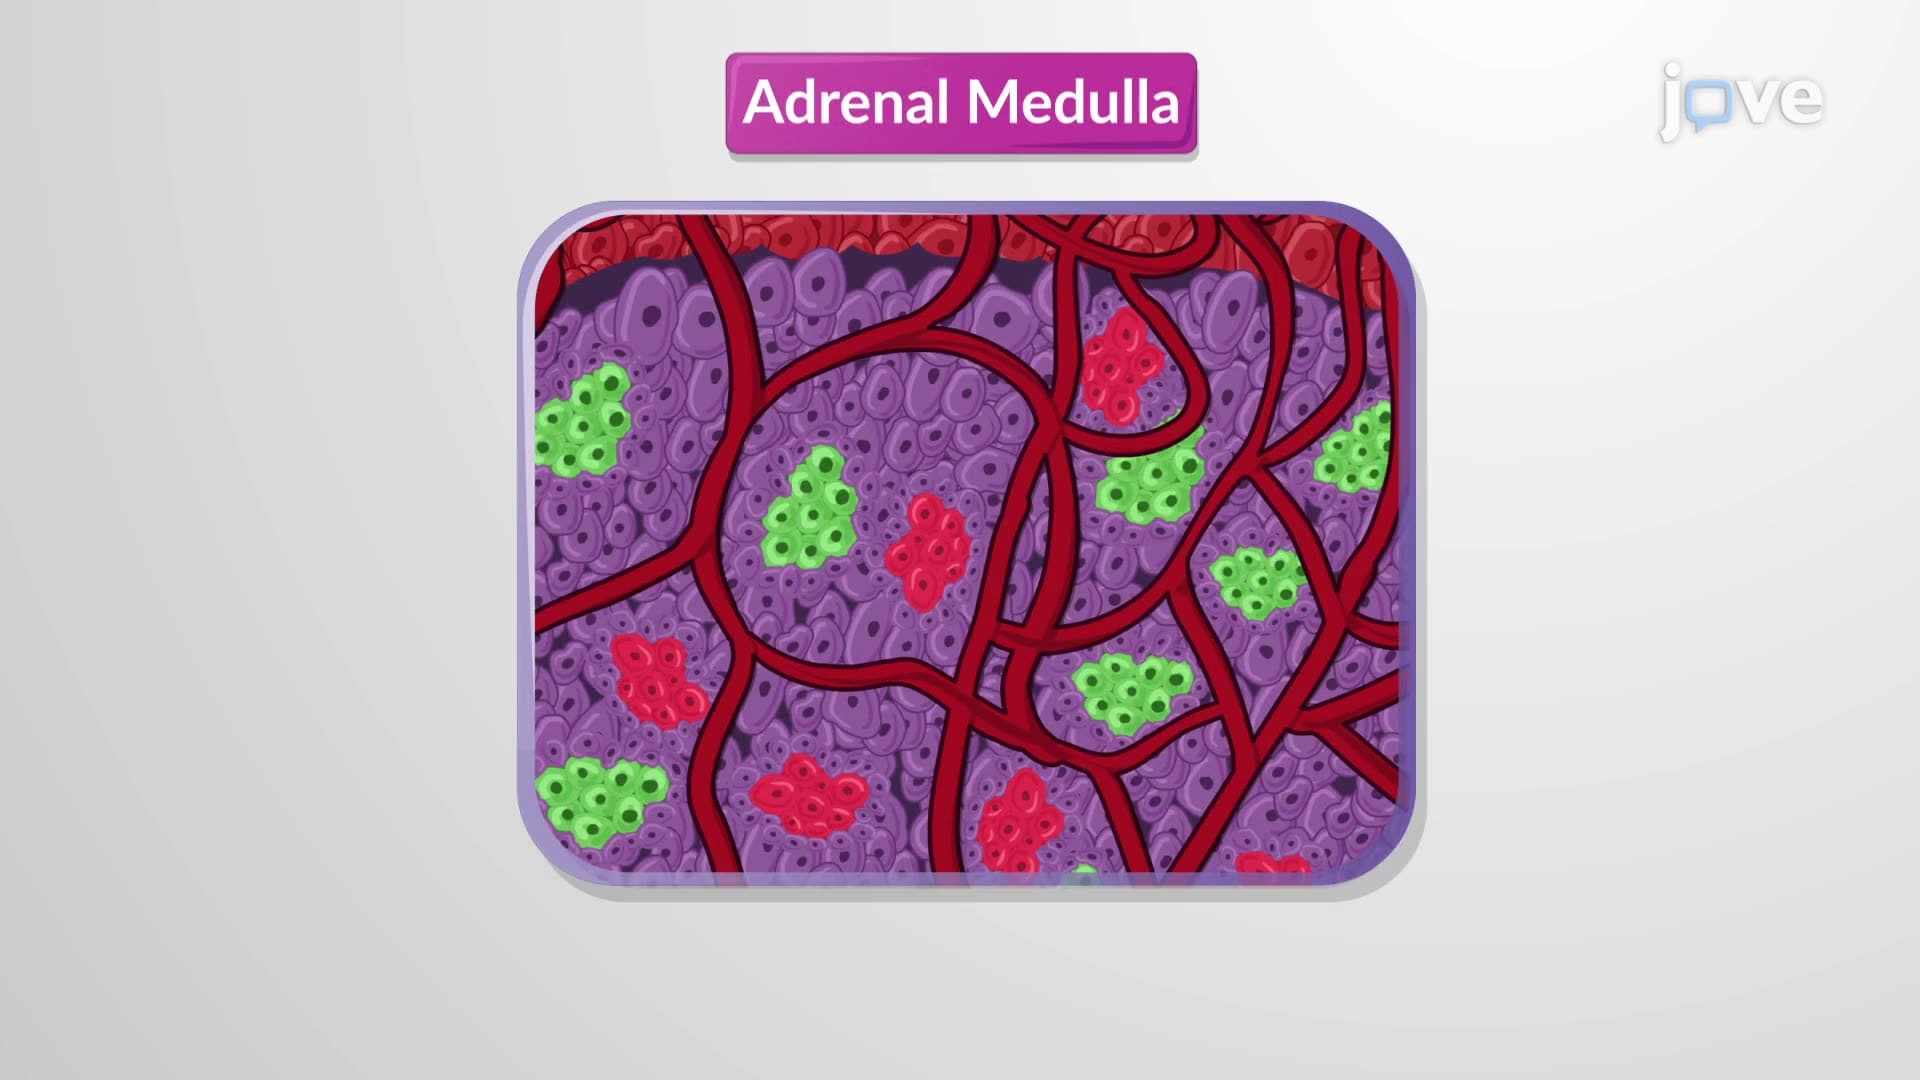
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and corticosterone...
 01:17
Anatomy of the Adrenal Glands
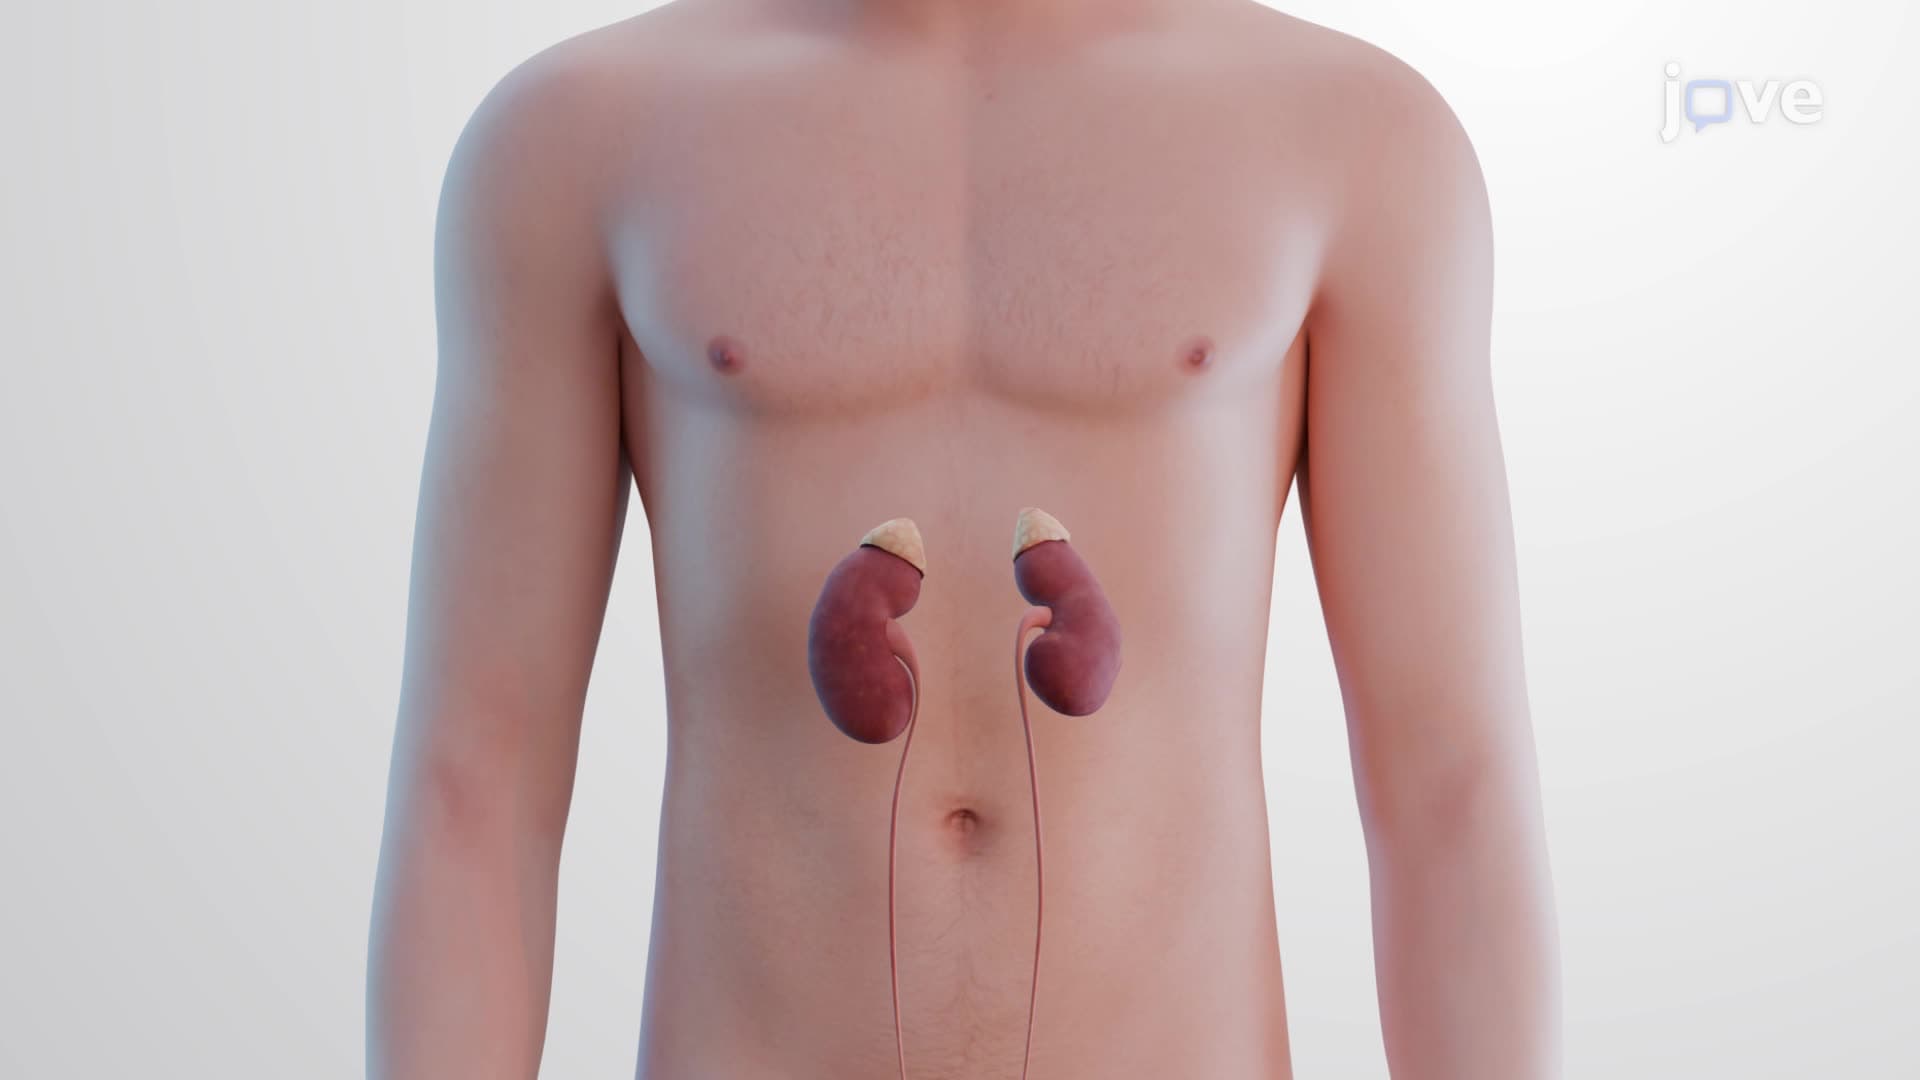
These glands possess a distinctive yellow tinge due to the stored cholesterol and fatty acids required for hormone synthesis. They are encased in a fibrous capsule and cushioned by fat.
The adrenal gland comprises two distinct regions...
 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
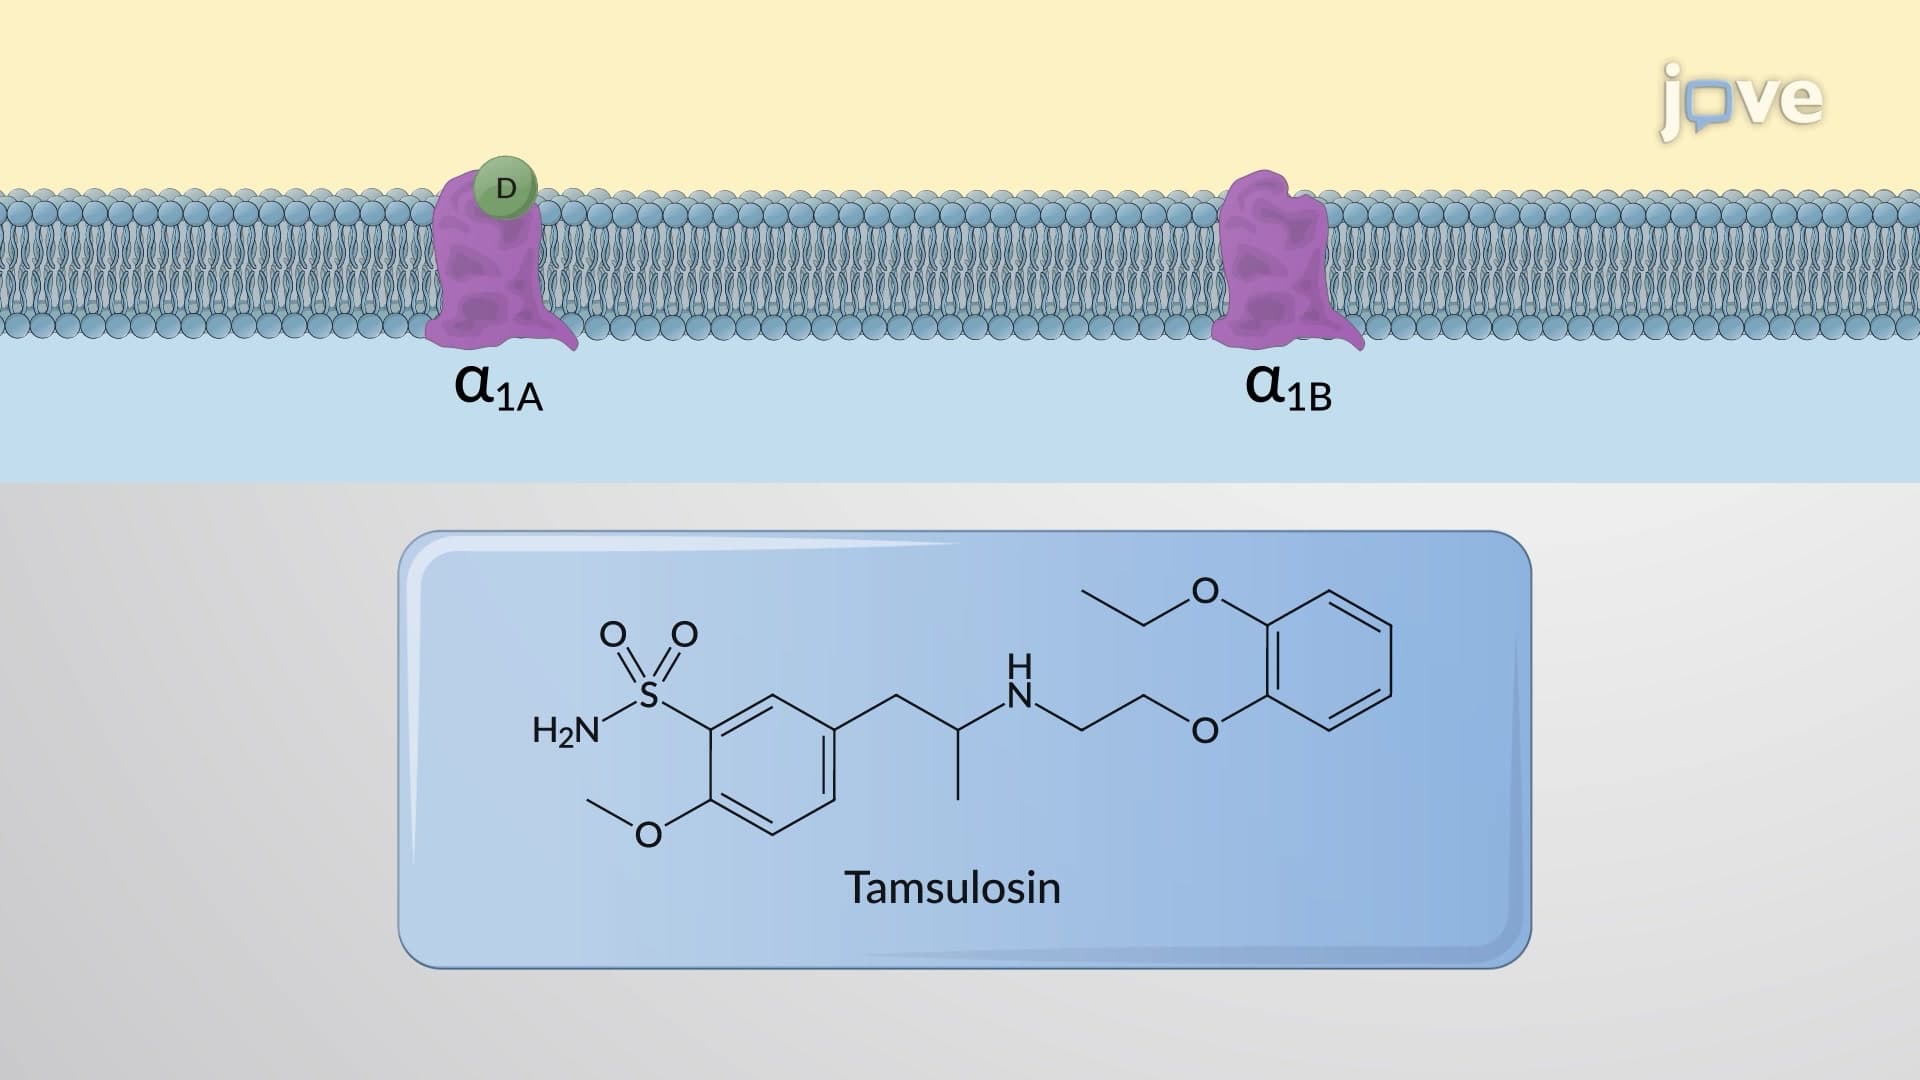
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
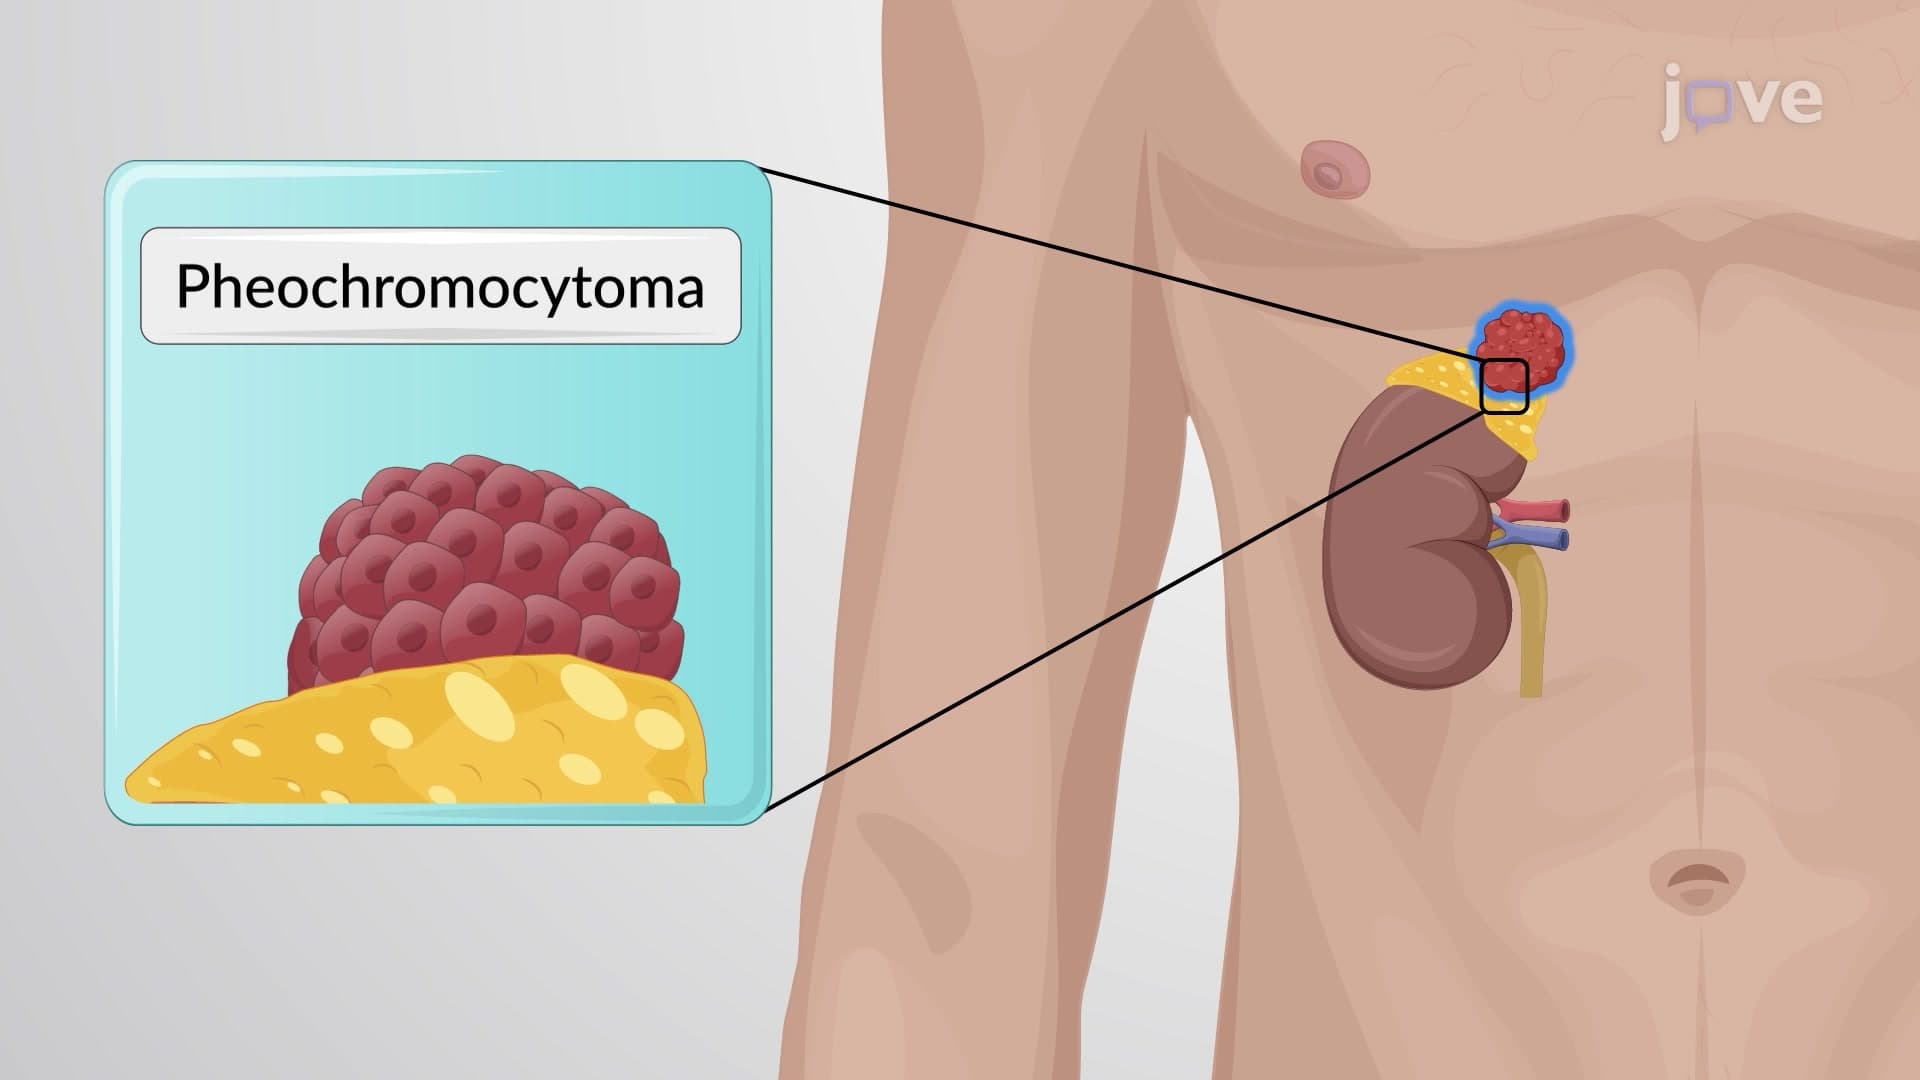
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...