Related Experiment Videos

Thiazolidinedione-induced edema

Nancee V Niemeyer1, Laurel M Janney

  • 1Department of Pharmacy Service, Iowa City Veterans Affairs Medical Center, Iowa 52246-2208, USA.

Pharmacotherapy
|July 20, 2002
PubMed

Related Concept Videos

Oral Hypoglycemic Agents: Biguanides and Glitazones01:26

Oral Hypoglycemic Agents: Biguanides and Glitazones
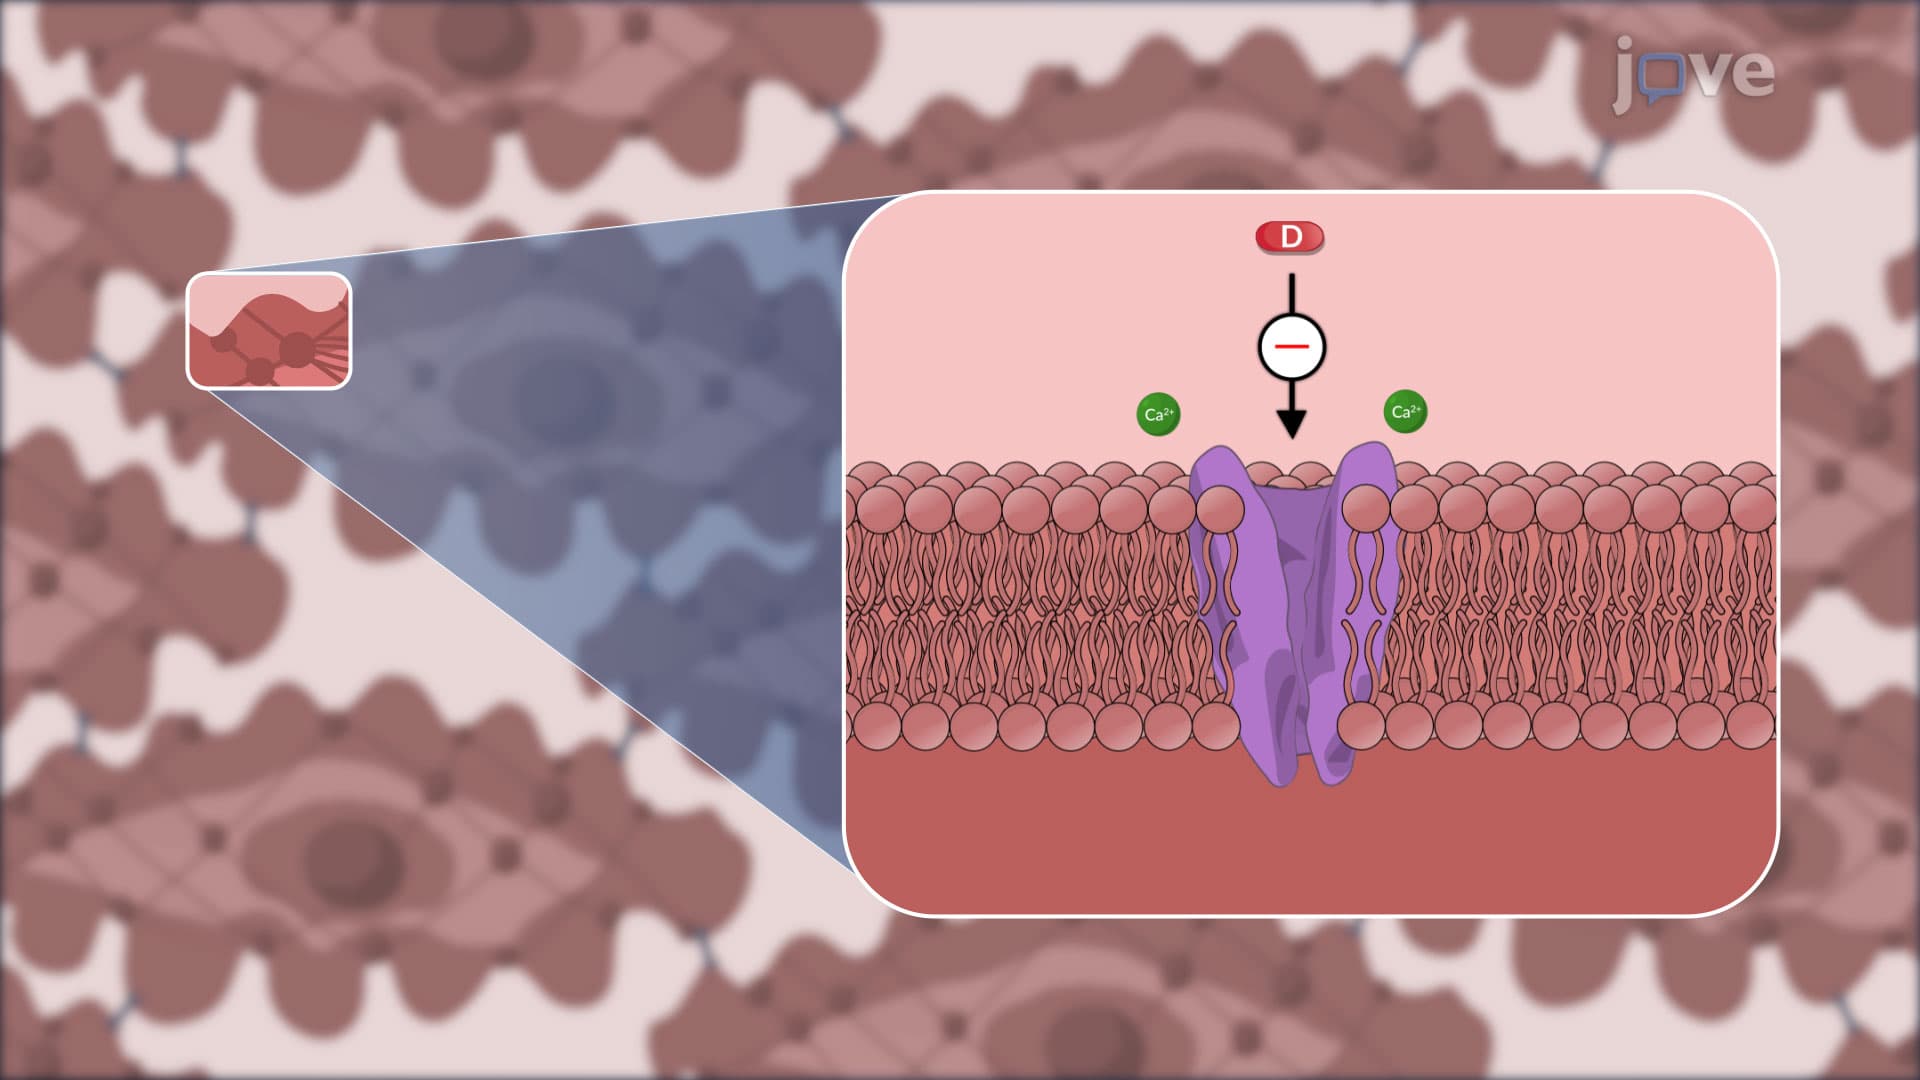
Biguanides, particularly metformin (Glucophage), are insulin sensitizers that enhance glucose uptake, thereby reducing insulin resistance. Unlike sulfonylureas, metformin doesn't prompt insulin secretion, which helps to curb hypoglycemia risk. Metformin is beneficial in treating conditions like polycystic ovary syndrome due to its insulin-resistance reduction capability. The drug's primary action involves curtailing hepatic gluconeogenesis, a significant contributor to high blood glucose levels...
Antihypertensive Drugs: Thiazide-Class Diuretics01:15

Antihypertensive Drugs: Thiazide-Class Diuretics

Thiazide diuretics are sulfonamide derivatives featuring a benzothiadiazine ring system in their molecular structure. Based on this structure, thiazide diuretics can be categorized into two groups: thiazide-type and thiazide-like diuretics. Thiazide-type diuretics, including hydrochlorothiazide and chlorothiazide, consist of a benzothiadiazine backbone with an attached sulfonamide group. Thiazide-like diuretics, such as chlorthalidone and indapamide, lack the thiazide ring but demonstrate...
Type I Diabetes III: Clinical Manifestations01:19

Type I Diabetes III: Clinical Manifestations
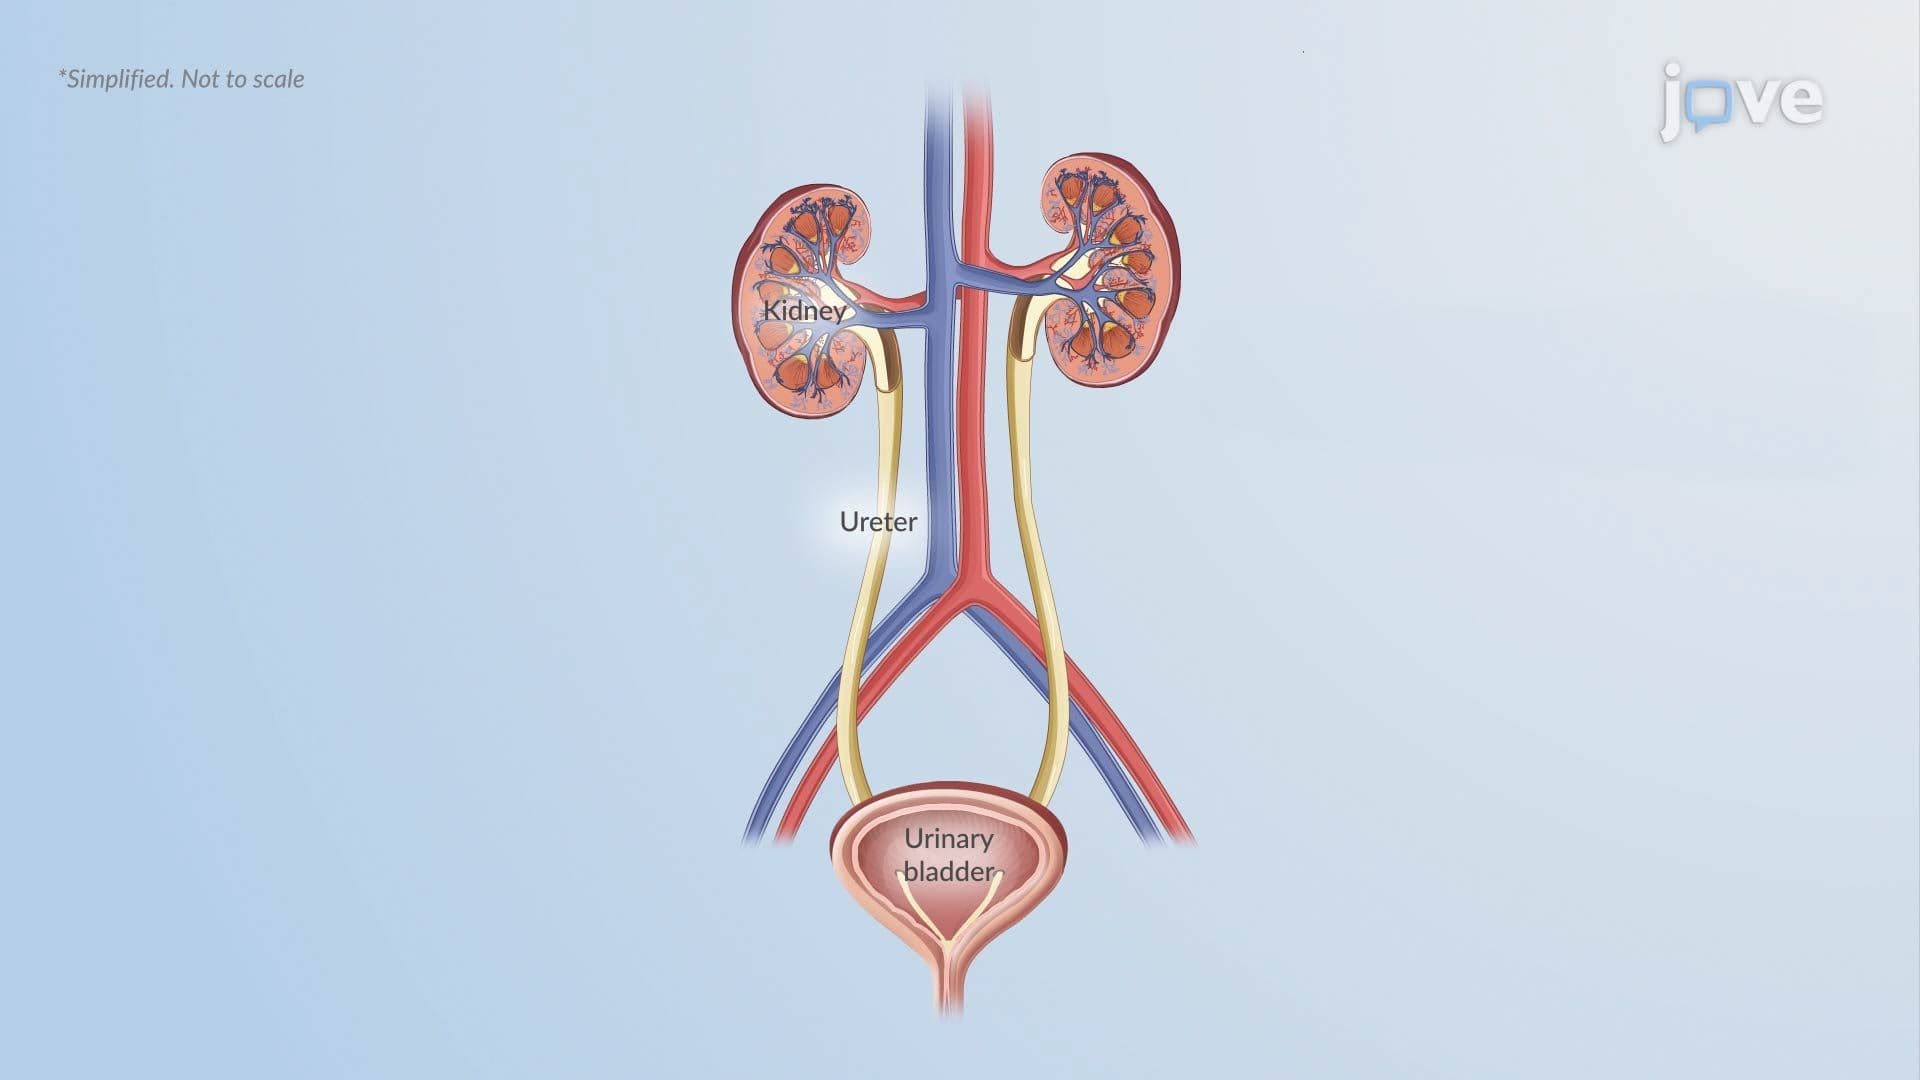
Type 1 diabetes mellitus typically presents with rapid-onset symptoms due to the body’s inability to utilize glucose in the absence of insulin. Since insulin is required for glucose uptake into cells, its deficiency leads to hyperglycemia and cellular energy deprivation, resulting in characteristic clinical features.Polyuria and PolydipsiaOne of the earliest, most prominent symptoms is polyuria (excessive urination). When blood glucose concentrations rise above the renal threshold, the kidneys...
Diabetes Insipidus II: Pathophysiology01:22

Diabetes Insipidus II: Pathophysiology

Normally, water balance is maintained through three interconnected mechanisms: the hypothalamic thirst center, the synthesis and release of antidiuretic hormone (ADH, or vasopressin), and the kidneys' responsiveness to this hormone. ADH is synthesized in the hypothalamus, released from the posterior pituitary, and acts on the distal nephron, allowing water reabsorption and concentrated urine production.Diabetes Insipidus and Its TypesIn diabetes insipidus (DI), this regulatory system is...
Cerebral Edema l: Introduction01:19

Cerebral Edema l: Introduction

Cerebral edema is a pathological increase in brain water content that disrupts intracranial pressure regulation and impairs neurological function. Because the cranial vault is rigid, even modest increases in tissue volume can compromise cerebral perfusion, distort neural structures, and initiate secondary injury. Cerebral edema develops through four principal mechanisms: vasogenic, cytotoxic, interstitial, and ionic.Vasogenic EdemaVasogenic edema arises from disruption of the blood–brain...
Hyperglycemia01:29

Hyperglycemia

Hyperglycemia is an abnormally high blood glucose level. It is diagnosed by fasting glucose ≥126 mg/dL, 2-hour oral glucose tolerance test (or OGTT) ≥200 mg/dL, random glucose ≥200 mg/dL with symptoms, or HbA1c ≥6.5%. However, HbA1c results may be unreliable in certain conditions, such as anemia or hemoglobinopathies, and the diagnosis should be confirmed unless classic symptoms are present. Postprandial hyperglycemia is typically considered significant when glucose levels exceed 180 mg/dL two...