Related Experiment Video
Updated: Sep 30, 2026
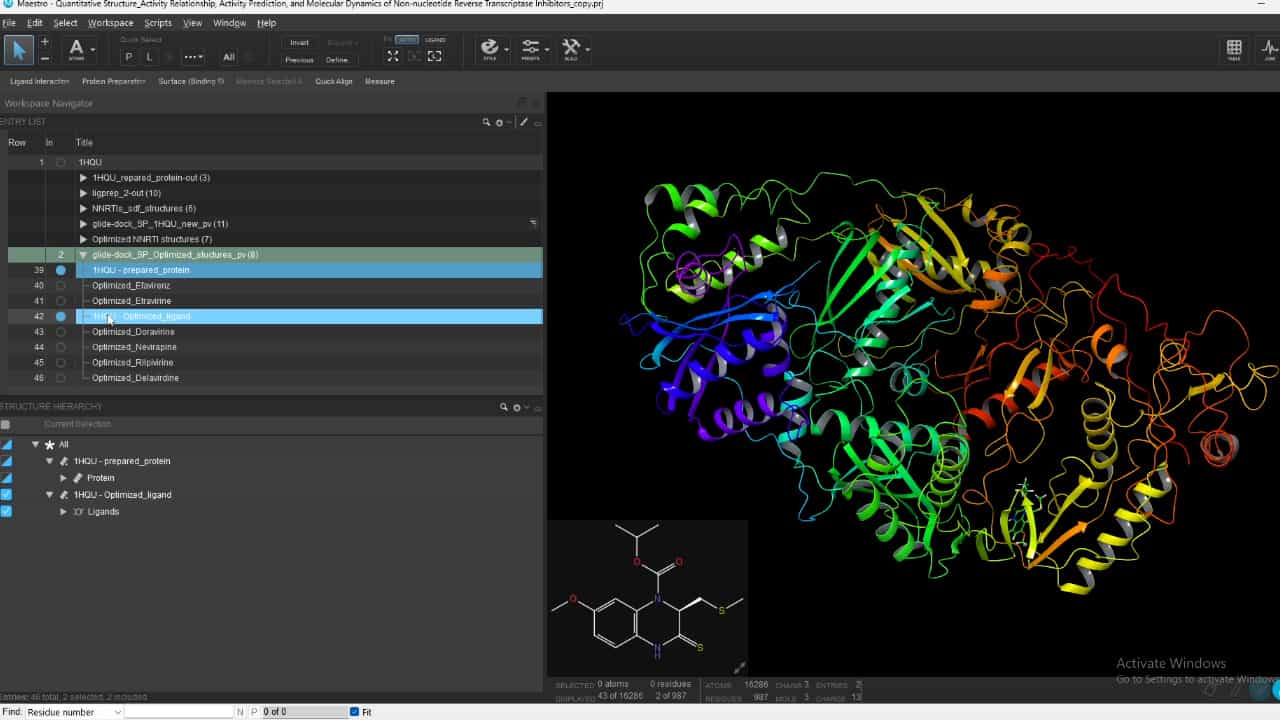

Quantitative Structure-Activity Relationship, Activity Prediction, and Molecular Dynamics of Non-nucleotide Reverse Transcriptase Inhibitors
Published on: May 9, 2025
Pharmacokinetic interactions between efavirenz and rifampicin in HIV-infected patients with tuberculosis
Luis F López-Cortés1, Rosa Ruiz-Valderas, Pompeyo Viciana
1Infectious Diseases Service, University Hospital Virgen del Rocío, Seville, Spain. lflopez@telefonica.net

Objective:
To evaluate the pharmacokinetic interactions between efavirenz and rifampicin (rifampin) in patients with HIV infection and tuberculosis.
Design:
Nonblind, randomised, pharmacokinetic study.
Patients:
24 patients (21 male, 3 female; mean age 37 years) with HIV infection and tuberculosis.
Interventions:
Patients were randomised to one of the following treatments: group A (n = 16) received antituberculosis drugs without rifampicin, plus highly active antiretroviral therapy (HAART) including efavirenz 600 mg once daily, on days 1 to 7. Patients were then switched to rifampicin in bodyweight-adjusted fixed-dose combination plus HAART including efavirenz 600 mg once daily (group A-1; n = 8) or efavirenz 800 mg once daily (group A-2; n = 8). Group B (n = 8) received rifampicin in bodyweight-adjusted fixed-dose combination on days 1 to 7; on day 8, HAART including efavirenz 800 mg once daily was added. Blood samples were obtained on days 7 and 14.
Methods:
Plasma concentrations of efavirenz and rifampicin were quantified by using validated high performance liquid chromatography assays, and pharmacokinetic parameter values were determined by noncompartmental methods. The differences between pharmacokinetic parameters on days 7 and 14 were used to assess interactions.
Results:
There was a correlation between the pharmacokinetic parameters of efavirenz and the dose/kg administered. For efavirenz, mean (median) peak concentration, trough concentration and area under the concentration-time curve over the administration interval decreased 24% (24%), 25% (18%) and 22% (10%), respectively, in the presence of rifampicin. Large interpatient variability was observed, suggesting that plasma concentration monitoring of efavirenz may be advisable. Overall, the pharmacokinetics of efavirenz 800 mg plus rifampicin were similar to those of efavirenz 600 mg without rifampicin. The pharmacokinetics of rifampicin did not change substantially in the presence of efavirenz. Differences in patients' bodyweight appeared to cause further differences in exposure to efavirenz. Plasma concentrations of efavirenz in patients weighing <50 kg were similar to those previously described in HIV-infected patients without concomitant tuberculosis. However, plasma concentrations in patients weighing >or=50 kg were almost halved compared with those in patients weighing <50 kg.
Conclusions:
Although the minimal effective efavirenz plasma concentration that assures virological success is not currently known, it may be advisable to increase the dosage of efavirenz to 800 mg once daily when it is coadministered with rifampicin. Rifampicin can be used with efavirenz without dosage modification.
Related Concept Videos
 01:26
Pharmacokinetics: Drug–Food and Drug–Viral Interactions
 01:25
Pharmacokinetics: Drug–Drug Interactions
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...