Related Experiment Video
Updated: Sep 30, 2026


Bladder Smooth Muscle Strip Contractility as a Method to Evaluate Lower Urinary Tract Pharmacology
Published on: August 18, 2014
The tachykinin NK-2 receptor antagonist SR48968 does not block noncholinergic contractions in unstable human bladder
Kate H Moore1, David S H Lam, William Lynch
1The Detrusor Muscle Laboratory, Pitney Clinical Sciences Building, Pelvic Floor Unit, St. George Hospital, Kogarah, NSW 2217, Sydney, Australia. k.moore@unsw.edu.au

Abstract:
Concentration-response curves to acetylcholine, and responses to electrical field stimulation (EFS) were compared in detrusor muscle strips, from control patients and those with idiopathic detrusor instability (IDI). Responses were similar in both groups. However, atropine abolished responses to EFS in 80% of control but only 33% of IDI patients (P>0.05), with the residual atropine-resistant response in most IDI patients abolished by tetrodotoxin. The post-atropine residual response was unaffected by the tachykinin NK-2 receptor antagonist SR48968. Despite the known existence of NK-2 receptors in the human detrusor, there was no evidence for tachykinin contribution to EFS-induced contractions.
More Related Videos


Related Concept Videos
 01:17
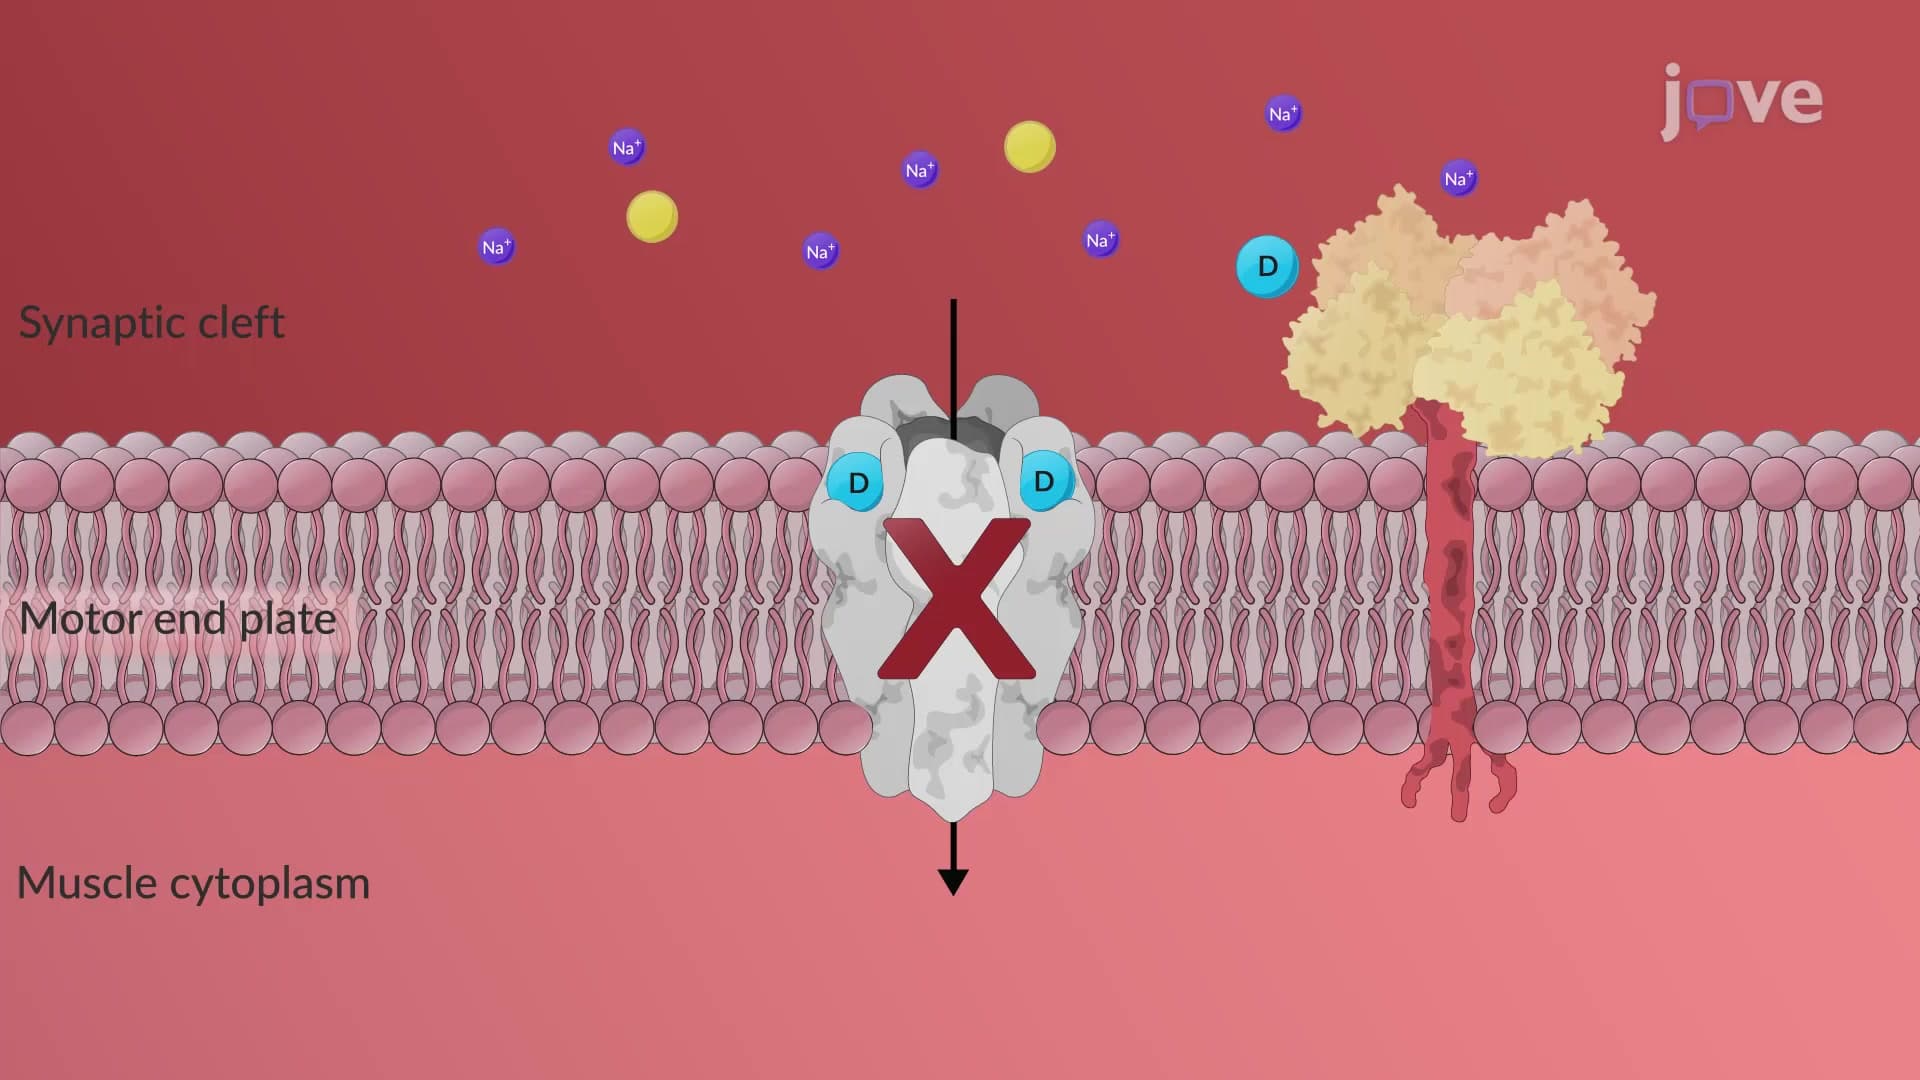
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:28
Drugs Acting on Autonomic Ganglia: Blockers
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...