[Bronchopulmonary carcinoid tumours]
Related Experiment Video
Updated: Sep 30, 2026
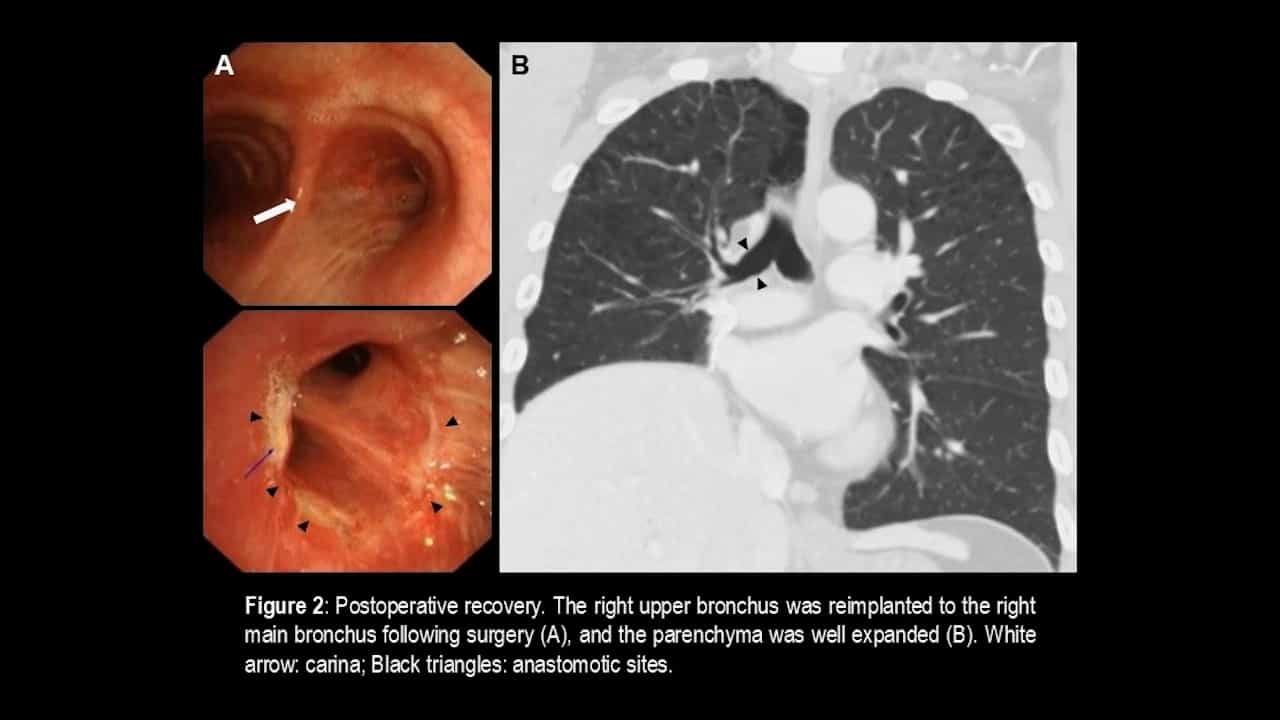
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
O Rena1, P L Filosso, E Ruffini
1Cattedra di Chirurgia Toracica, Università degli Studi, Turin, Italy. ottavio.rena@tiscalinet.it

Abstract:
Carcinoids are neuroendocrine neoplasms. Bronchial carcinoids are unusual, malignant primary neoplasms that characteristically involve the central airways and typically exhibit well-defined margins and bronchial-related growth. Bronchial carcinoids include low-grade typical carcinoids and the more aggressive atypical ones. They usually affect patients in the 3rd through the 7th decade of life who are often symptomatic with cough, hemoptysis or obstructive pneumonia. Rarely, the initial symptoms are related to the secretion of hormones causing carcinoid or other endocrine syndromes. Bronchial carcinoids radiologically manifest as hilar or perihilar masses, with or without associated atelectasis, pneumonia or bronchiectasis. At CT-scan the relationship of these tumors with the bronchial tree is usually seen, and they show contrast enhancement or calcification. Even if the radiological signs may be suggestive for bronchial carcinoid, the definitive diagnosis is reached only by the tissue sampling. Bronchoscopic biopsy is the more effective way to identify the nature of carcinoid tumors because of their frequent central location. The treatment of choice is the surgical resection which should be carried out with maximum respect for the residual lung and bronchial tissues. Endoscopic ablations in well defined cases, bronchotomy and lung resections with or without bronchoplastic procedures have been described. Hilar and mediastinal lymph node sampling and examination should be ever performed during open procedures. Positivity of the nodal tissues could influence the resection procedure and is related with the prognosis, specially for the atypical carcinoids. Chemo- and radiation therapy are not effective in improving the long-term outcome in those patients with advanced disease. The long-term outcome is strictly related with the histological subtype and the lymph node status. Local recurrences and distant metastases are more frequent in the atypical carcinoids which manifest a more aggressive behavior. During the last decade, the importance of the use of somatostatine analogues (octreotide) in the staging, early detection of the recurrent disease and its management such as that of the associated carcinoid syndrome became clear.
Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:23
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...
 01:17
Other Pulmonary Disorders
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema