Related Experiment Video
Updated: Jun 23, 2026
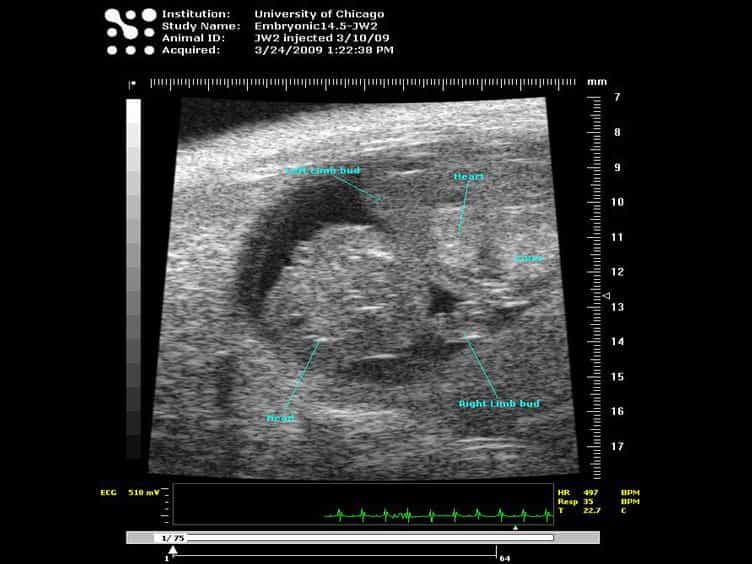

Murine Fetal Echocardiography
Published on: February 15, 2013
Fetal cardiomyopathies: pathogenic mechanisms, hemodynamic findings, and clinical outcome
Simone R F F Pedra1, Jeffrey F Smallhorn, Greg Ryan
1Division of Cardiology, The Hospital for Sick Children, Toronto, Ontario, Canada.

Insights
Fetal cardiomyopathies (CMs) have diverse causes and poor outcomes. Diastolic dysfunction in fetal CM significantly increases mortality risk, highlighting its importance in prenatal care.
Area of Science:
- Cardiology
- Perinatology
- Fetal Medicine
Background:
- Prenatal diagnosis of fetal structural heart defects is established, but fetal cardiomyopathies (CMs) remain understudied.
- Information on pathogenic mechanisms, hemodynamics, and outcomes of fetal CM is limited.
Purpose of the Study:
- To investigate the pathogenic mechanisms, hemodynamic findings, and perinatal outcomes of fetal cardiomyopathies (CMs).
- To identify risk factors associated with mortality in fetuses diagnosed with CM.
Main Methods:
- Retrospective review of fetal echocardiograms and perinatal histories of 55 fetuses with CM.
- Classification of CM into dilated and hypertrophic types, with analysis of associated conditions and cardiac function.
- Statistical analysis, including logistic regression, to determine mortality risk factors.
Main Results:
- 55 fetuses diagnosed with CM: 22 dilated CM and 33 hypertrophic CM.
- Causes included congenital infections, maternal antibodies, genetic syndromes, twin-twin transfusion syndrome, and idiopathic cases.
- High perinatal mortality (63% in continued pregnancies), with systolic dysfunction, diastolic dysfunction, and atrioventricular valve regurgitation as risk factors. Diastolic dysfunction showed an 8-fold increased mortality risk.
Conclusions:
- Fetal cardiomyopathies encompass a wide range of intrinsic and extrinsic etiologies.
- Affected fetuses often experience poor perinatal outcomes.
- Diastolic dysfunction is a critical predictor of mortality in fetal CM, necessitating close monitoring.
Background:
Although the prenatal diagnosis of most fetal structural heart defects and dysrhythmias has been described, there is a paucity of information about cardiomyopathies (CMs) in prenatal life.
Methods And Results:
To determine the pathogenic mechanisms, hemodynamic findings, and outcome of fetal CM, we reviewed the fetal echocardiograms and perinatal histories of 55 affected fetuses. Dilated CM was diagnosed in 22 cases, including 2 with congenital infections, 5 familial cases, 6 with endocardial fibroelastosis related to maternal anti-Ro/La antibodies, and 9 idiopathic cases. Thirty-three had hypertrophic CM, 7 associated with maternal diabetes, 2 with Noonan's syndrome, 2 with alpha-thalassemia, 18 with twin-twin transfusion syndrome, 1 with familial hypertrophy, and 3 with idiopathic hypertrophy. Systolic dysfunction was present in all cases of dilated CM and 15 cases of hypertrophic CM. Diastolic dysfunction was present in 19 of 30 fetuses with assessment of diastolic function parameters. Significant mitral or tricuspid valve regurgitation was seen in 32 cases. Eight fetuses were hydropic and 23 had signs of early hydrops. Seven pregnancies were terminated. Of 46 continued pregnancies with follow-up, 29 (63%) died perinatally. The presence of systolic dysfunction, diastolic dysfunction, and significant atrioventricular valve regurgitation were identified as risk factors for mortality. By multiple logistic regression, diastolic dysfunction was associated with an 8-fold increased risk relative to the other parameters.
Conclusions:
Fetal CM has a broad spectrum of intrinsic and extrinsic causes. A poor outcome is observed in many affected fetuses. Diastolic dysfunction in fetal CM is associated with the highest risk of mortality.

Related Concept Videos
 01:17
Pathophysiology of Heart Failure
 01:21
Myocarditis I: Introduction
 01:29
Heart Failure II: Pathophysiology
 01:25
Cardiomyopathy I: Introduction and Classification
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy