Related Experiment Video
Updated: Aug 16, 2026


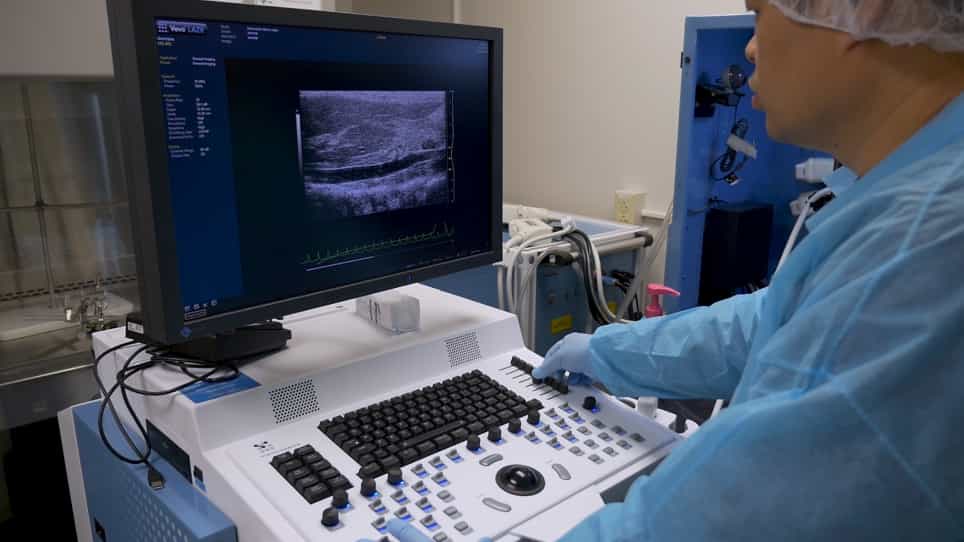
Manufacturing Abdominal Aorta Hydrogel Tissue-Mimicking Phantoms for Ultrasound Elastography Validation
Published on: September 19, 2018
[Growth rate of abdominal aortic aneurysms. Ultrasounds study and clinical outcome]
G Simoni1, A Beghello, M Buscaglia
1Dipartimento di Discipline Chirurgiche, Morfologiche e Metodologie Integrate (DiCMI), Sezioni di Chirurgia Vascolare, Università degli Studi di Genova, Genova, Italy.

Background:
The standard treatment for abdominal aortic aneurysms (AAA) >55 mm is actually represented by surgical repair mainly or by endovascular repair, in selected cases; conversely the debate is still open for those ranging 40-55 mm. These last and smaller aneurysms are usually followed-up by ultrasounds (US), in order to detect too fast expansions and to prevent sudden ruptures. Aim of this study is to present the results of the US follow-up of a series of asymptomatic AAAs and the correlation between expansion rate and associated risk factors.
Methods:
All patients evaluated for an AAA between March 1991 and December 2000 were included and, according to the maximum diameters of the infrarenal aorta, were divided into 3 groups: A (26-29 mm), B (30-39 mm) and C (>39 mm). Groups A and B underwent US follow up at 6-month intervals, while group C underwent a complete preoperative evaluation.
Results:
The mean follow up was 36+/-24 months for the entire series (225 AAA); the mean expansion rate was 1 mm/year for group A, <1.5 mm/year for group B for the first 5 years with a sharp increase (5 mm/year) in the following 2 years and 3 mm/year for group C up to 5 years. Among the associated risk factors, hypertension and smoking have confirmed their main role, independent from the initial diameter (p<0.01). Eight ruptures (3.8%) occurred in patients unsuitable for surgery or who refused it and in 7 cases they were lethal. The range between diagnosis and death (19-61 months) and the maximum size (38-93 mm) were absolutely unpredictable. The remaining 40 deaths were related to vascular diseases (MI and stroke 29.8%) or concurrent neoplasms (29.8%) mainly. The surgical treatment was carried out as elective repair on 45 patients (mortality rate 2.2%) and in emergency in 2 cases, both dead, with a mean interval from diagnosis to surgery of 28+/-17 months.
Conclusions:
Our results agree with the literature data concerning the dilatative trend and the risk factors and, according to these, elective repair in patients with AAA ranging 45-55 mm should be considered.
Related Concept Videos
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:30
Aneurysm I: Introduction
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:26
Aneurysm III: Interprofessional Care