Related Experiment Videos
Duration of antibiotics in children with osteomyelitis and septic arthritis
M B Vinod1, J Matussek, N Curtis
1Department of General Paediatrics, Royal Children's Hospital, University of Melbourne, Melbourne, Victoria, Australia.

Insights
Short-duration antibiotic treatment for pediatric osteomyelitis (OM) and septic arthritis (SA) showed good outcomes, with a low recurrence rate of 1.4%. This suggests short courses may be a safe and effective standard treatment for uncomplicated cases.
Area of Science:
- Pediatric infectious diseases
- Musculoskeletal infections
Background:
- Acute osteomyelitis (OM) and septic arthritis (SA) are common pediatric infections.
- Traditionally, long-duration antibiotic therapy has been the standard treatment for these conditions.
- This study evaluated outcomes at a center where short-duration antibiotic treatment was intended as routine.
Purpose of the Study:
- To assess the outcomes of children diagnosed with acute osteomyelitis and septic arthritis.
- To determine if short-duration antibiotic treatment (< or = 3.5 weeks) is effective for these pediatric infections.
- To evaluate the long-term functional status and recurrence rates in treated children.
Main Methods:
- Retrospective chart review of children with acute OM and SA.
- Telephone interviews were conducted for long-term outcome assessment.
- Patients selected were low-risk for complications, with illness duration <= 14 days and no underlying conditions.
Main Results:
- Thirty-two children with OM, 34 with SA, and five with both were included.
- The median antibiotic treatment duration exceeded the intended short course for most patients (OM: 5.4 weeks, SA: 4.4 weeks, OMSA: 5.0 weeks).
- Only 22% received antibiotics for 3.5 weeks or less; the overall recurrence rate was low at 1.4%, with all patients achieving normal function at follow-up.
Conclusions:
- Most patients received longer antibiotic courses than planned, contrary to hospital protocols.
- Children treated with shorter antibiotic courses (< or = 3.5 weeks) experienced good outcomes.
- The findings support the potential for short-duration treatment as a standard for uncomplicated pediatric OM/SA, warranting prospective evaluation.
Objective:
To evaluate the outcomes of children with acute osteomyelitis and septic arthritis at a hospital where short-duration antibiotic treatment (< or = 3.5 weeks) was considered routine.
Methodology:
We carried out a retrospective chart review, with telephone interviews to follow up and determine long-term outcomes. Patients were selected to be at low risk for complications (illness < or = 14 days, no underlying disease, uncomplicated presentation).
Results:
Thirty-two children with osteomyelitis (OM), 34 with septic arthritis (SA) and five with OM and SA (OMSA) were included. Blood cultures were positive (mainly Staphylococcus aureus) in 15% of patients who had not had prior antibiotic treatment, and microbiological confirmation (positive blood culture, Gram stain or culture of surgical specimen) was obtained in 36%. The median duration of antibiotic treatment was 5.4, 4.4 and 5.0 weeks for OM, SA and OMSA, respectively. Only 22% of patients received antibiotics for 3.5 weeks or less. Overall, the recurrence rate was 1.4%. At follow-up, only two patients had mild occasional pain at the site of the original infection; all patients had normal function.
Conclusions:
Contrary to expectations and local protocols, most patients were treated with conventional long-duration therapy. Patients treated for short courses had good outcomes. The low rate of complications may make randomized controlled equivalence trials unfeasible. Increasing evidence of the efficacy and safety of short-duration treatment (3-3.5 weeks) for acute, uncomplicated OM or SA in children suggests that this could be accepted as the standard treatment. However, this should be evaluated prospectively using a register, with at least 12 months' of follow-up.
Related Concept Videos
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:25
Mechanism of Antibiotic Resistance in MRSA
 01:25
Clinical Significance of Antibiotic Resistance
 01:26
Urine Studies II: Urine Culture and Sensitivity Test
 01:15
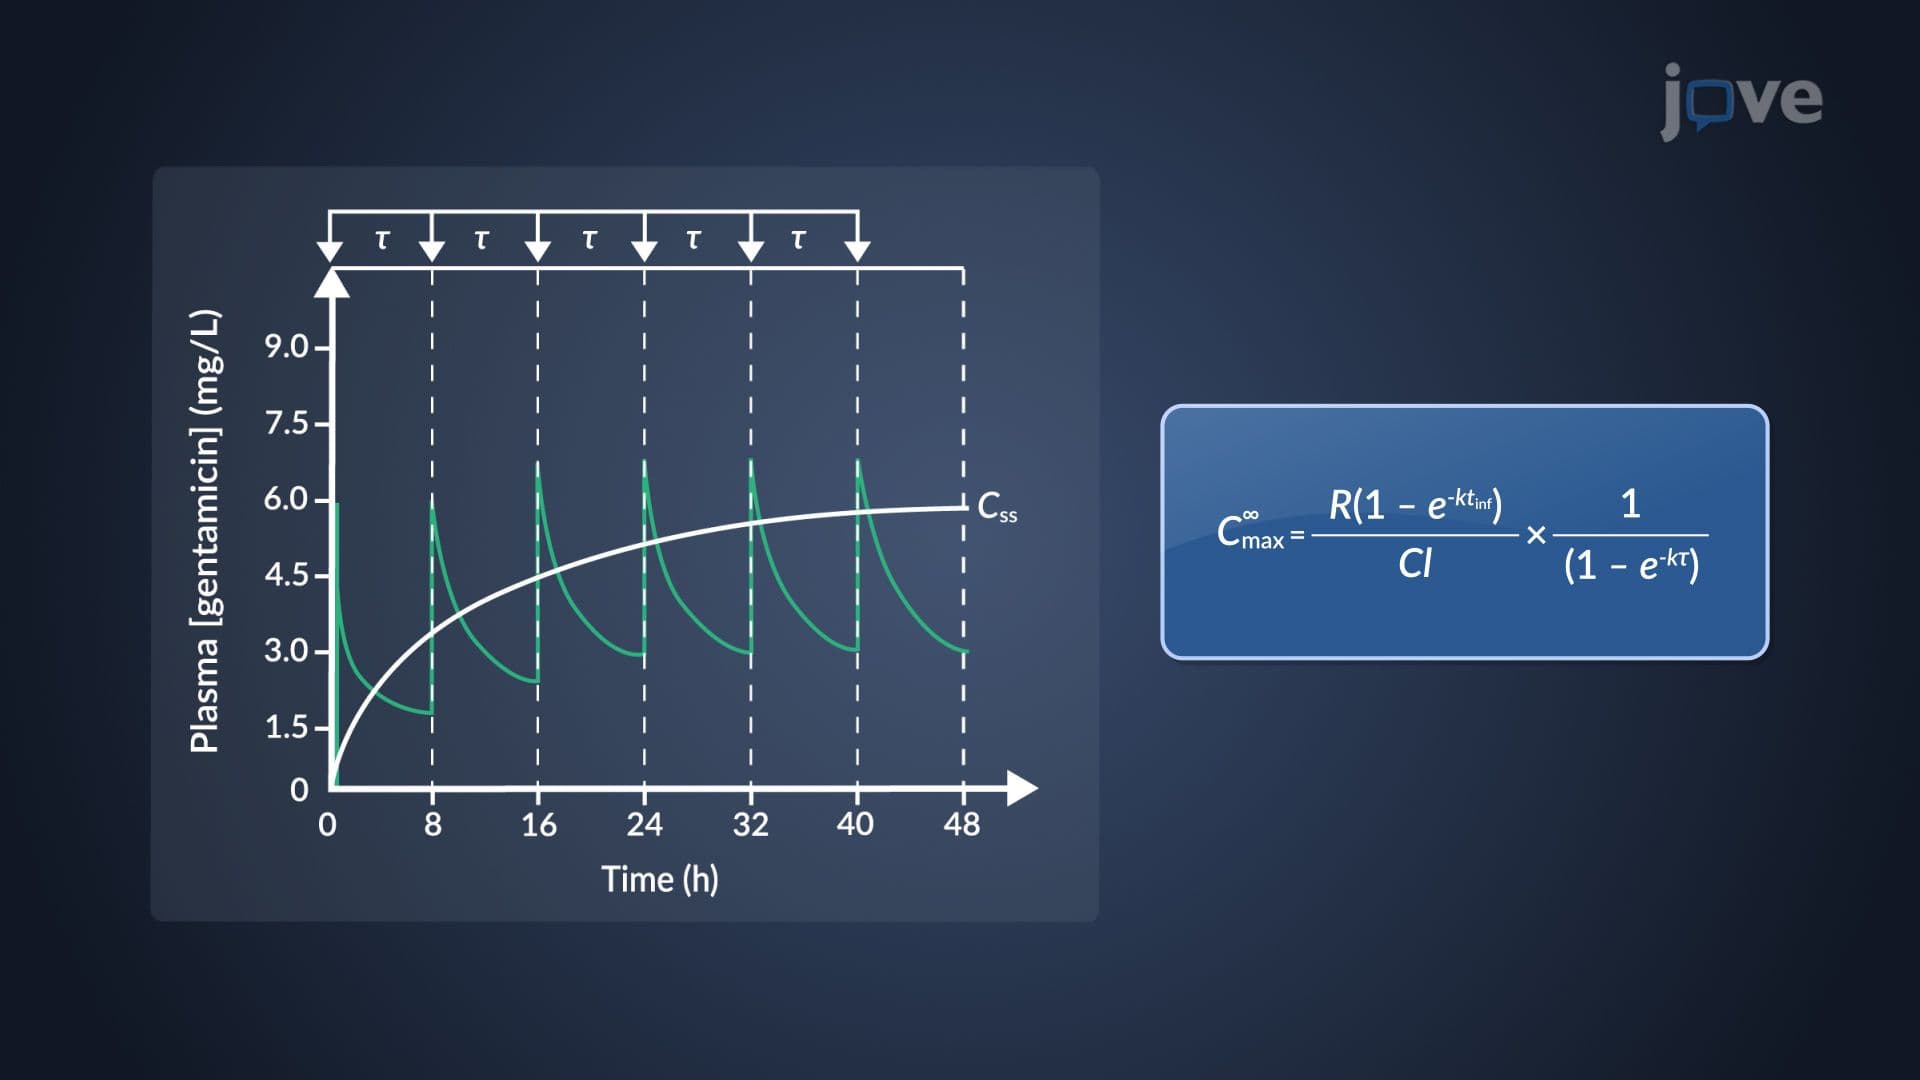
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care