Related Experiment Video
Updated: Sep 30, 2026


Methods for Studying Uterine Contributions to Pregnancy Establishment in an Ovariectomized Mouse Model
Published on: April 7, 2023
Effective, despite misconceptions. The IUD with progesterone must be replaced once a year, while the IUD with copper

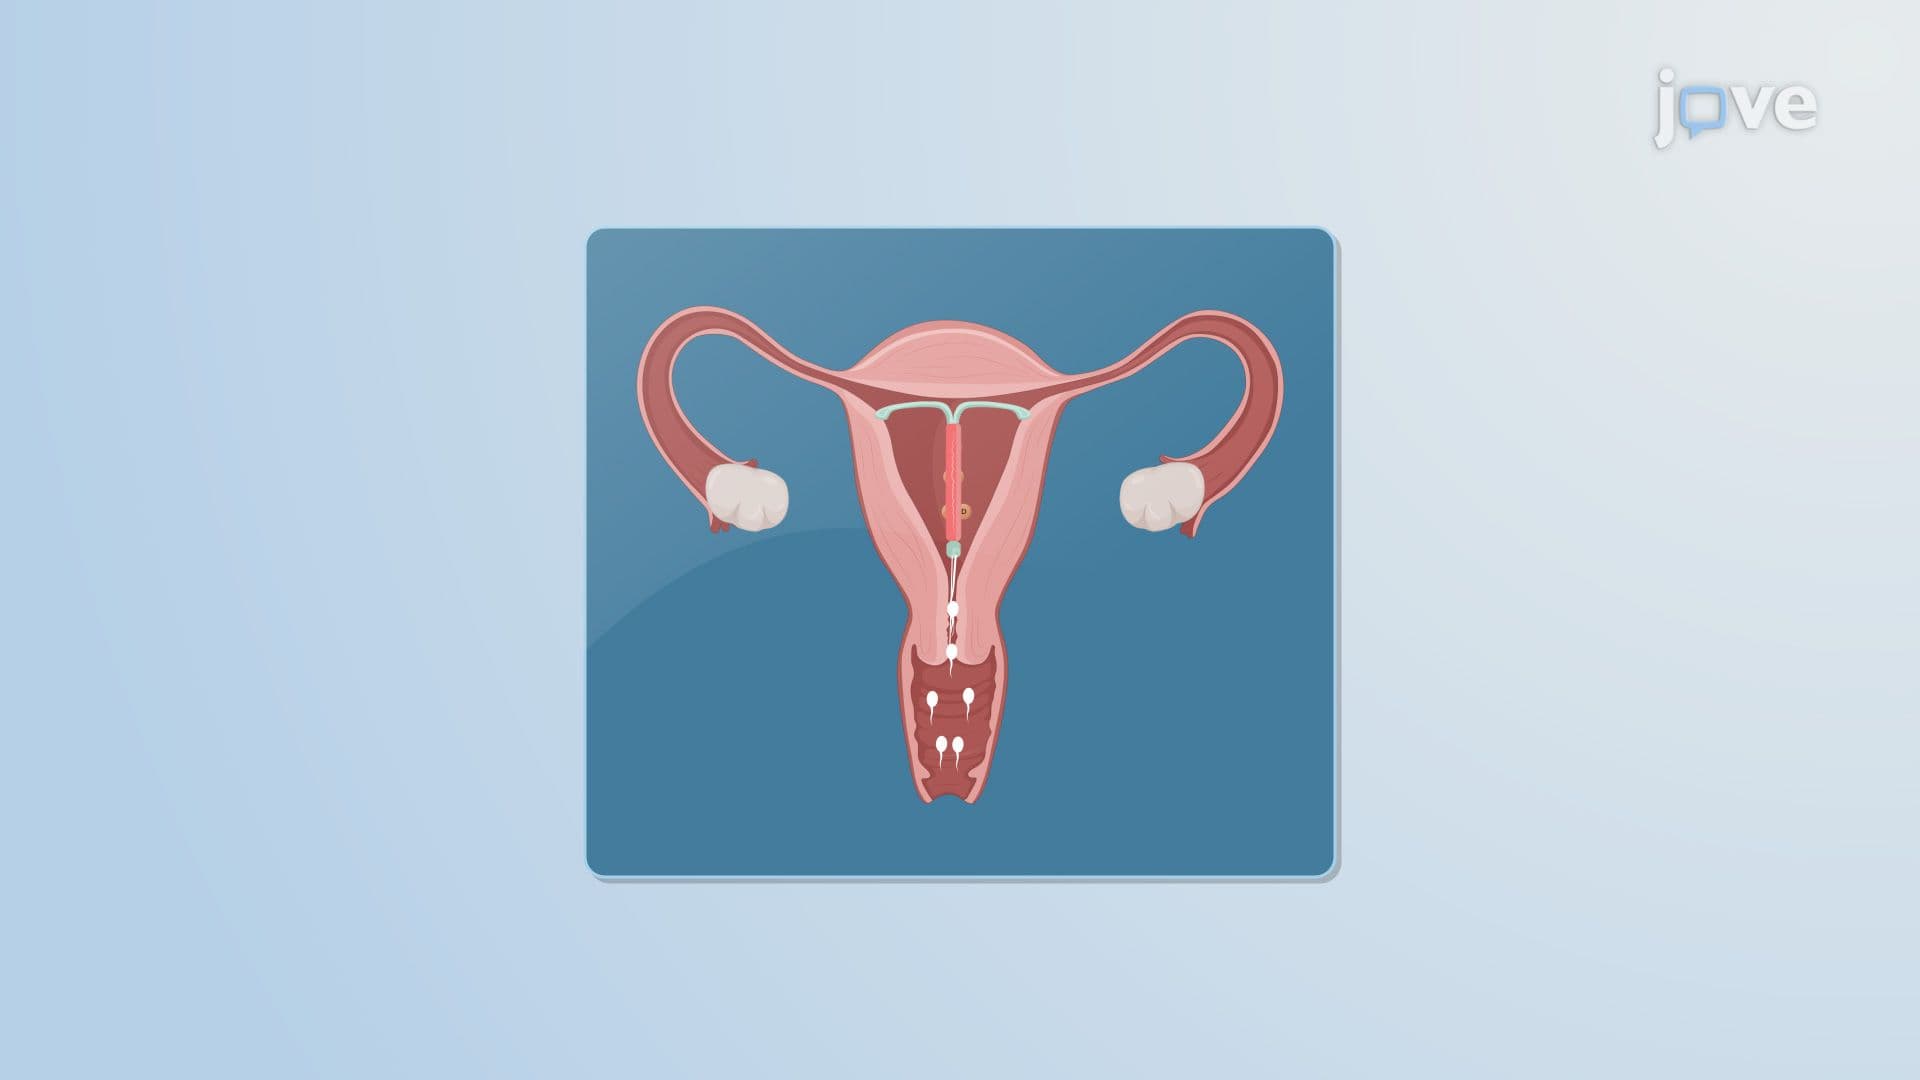
Many women have misconceptions about the intrauterine device, or IUD. The IUD is a safe and effective contraceptive method for many women. It is more effective than the condom, diaphragm, or spermicides, and also is more convenient than these methods, since it doesn't interfere with different sexual activities. The IUD is a small, T-shaped plastic device containing either copper or progesterone, and is inserted by a doctor into a woman's uterus. A thin plastic thread (1-2 inches long) protrudes through the cervix so that the user can cross-check to make sure the device is in place. Depending on the IUD type, small amounts of copper or progesterone are slowly released to prevent fertilization of the egg, or to prevent a fertilized egg from attaching to the uterine wall. The IUD with progesterone must be replaced once a year, while the IUD with copper may be left in for up to 10 years. The IUD is a good choice for women who can't take oral contraceptives and for women who have completed their families but want surgical sterilization. Because the IUD carries a slightly higher risk of ectopic pregnancy (a fertilized egg that implants outside the uterus), it is not usually recommended for women who already are at increased risk of the condition, such as those who have had a pelvic infection, a previous ectopic pregnancy or multiple sex partners. Common side effects of the IUD include some discomfort while the IUD is being inserted and some cramping and spotting during the first few weeks after insertion. Menstrual periods usually become slightly longer and heavier in women using the copper IUD, but become lighter in women using the progesterone IUD. Occasionally, the IUD will slip partially out of the uterus or be expelled entirely in the first few months.
Many women have misconceptions about the intrauterine device, or IUD. The IUD is a safe and effective contraceptive method for many women. It is more effective than the condom, diaphragm, or spermicides, and also is more convenient than these methods, since it doesn't interfere with different sexual activities. The IUD is a small, T-shaped plastic device containing either copper or progesterone, and is inserted by a doctor into a woman's uterus. A thin plastic thread (1-2 inches long) protrudes through the cervix so that the user can cross-check to make sure the device is in place. Depending on the IUD type, small amounts of copper or progesterone are slowly released to prevent fertilization of the egg, or to prevent a fertilized egg from attaching to the uterine wall. The IUD with progesterone must be replaced once a year, while the IUD with copper may be left in for up to 10 years. The IUD is a good choice for women who can't take oral contraceptives and for women who have completed their families but want surgical sterilization. Because the IUD carries a slightly higher risk of ectopic pregnancy (a fertilized egg that implants outside the uterus), it is not usually recommended for women who already are at increased risk of the condition, such as those who have had a pelvic infection, a previous ectopic pregnancy or multiple sex partners. Common side effects of the IUD include some discomfort while the IUD is being inserted and some cramping and spotting during the first few weeks after insertion. Menstrual periods usually become slightly longer and heavier in women using the copper IUD, but become lighter in women using the progesterone IUD. Occasionally, the IUD will slip partially out of the uterus or be expelled entirely in the first few months.
Related Concept Videos
 01:21
Intrauterine Drug Delivery Systems
 01:22
Birth Control Methods
 01:27
Ovarian Cycle
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:19
The Menstrual Cycle
The menstrual phase occurs from days 1 to 5 and involves the shedding of the stratum functionalis, as a uterine...