Related Experiment Video
Updated: Aug 1, 2026

Carotid Artery Infusions for Pharmacokinetic and Pharmacodynamic Analysis of Taxanes in Mice
Published on: October 27, 2014
Pharmacokinetics and pharmacodynamics of piperacillin/tazobactam when administered by continuous infusion and
David S Burgess1, Travis Waldrep
1College of Pharmacy, University of Texas at Austin, USA. burgessd@uthscsa.edu

Background:
Although intermittent bolus dosing is currently the standard of practice for many antimicrobial agents, beta-lactams exhibit time-dependent bacterial killing. Maximizing the time above the minimum inhibitory concentration (MIC) for a pathogen is the best pharmacodynamic predictor of efficacy. Use of a continuous infusion has been advocated for maximizing the time above the MIC compared with intermittent bolus dosing.
Objective:
This study compared the pharmacokinetics and pharmacodynamics of piperacillin/tazobactam when administered as an intermittent bolus versus a continuous infusion against clinical isolates of Pseudomonas aeruginosa and Klebsiella pneumoniae.
Methods:
Healthy volunteers were randomly assigned to receive piperacillin 3 g/ tazobactam 0.375 g q6h for 24 hours, piperacillin 6 g/tazobactam 0.75 g continuous infusion over 24 hours, and piperacillin 12 g/tazobactam 1.5 g continuous infusion over 24 hours. Five clinical isolates each of P aeruginosa and K pneumoniae were used for pharmacodynamic analyses.
Results:
Eleven healthy subjects (7 men, 4 women; mean +/- SD age, 28 +/- 4.7 years) were enrolled. Mean steady-state serum concentrations of piperacillin were 16.0 +/- 5.0 and 37.2 +/- 6.8 microg/mL with piperacillin 6 and 12 g, respectively. Piperacillin/tazobactam 13.5 g continuous infusion (piperacillin 12 g/tazobactam 1.5 g) was significantly more likely to produce a serum inhibitory titer > or = 1:2 against P aeruginosa at 24 hours than either the 6.75 g continuous infusion (piperacillin 6 g/tazobactam 0.75 g) or 3.375 g q6h (piperacillin 3 g/ tazobactam 0.375 g). There were no statistical differences against K pneumoniae between regimens. The median area under the inhibitory activity-time curve (AUIC) for the 13.5 g continuous infusion was higher than that for 3.375 g q6h and the 6.75 g continuous infusion against both P aeruginosa and Kpneumoniae (P < or = 0.007, 13.5 g continuous infusion and 3.375 g q6h vs 6.75 g continuous infusion against K pneumoniae). The percentage of subjects with an AUIC > or = 125 was higher with both 3.375 g q6h and the 13.5 g continuous infusion than with the 6.75 g continuous infusion against P aeruginosa and K pneumoniae (both, P < 0.001 vs 6.75 g continuous infusion against K pneumoniae).
Conclusions:
Piperacillin 12 g/tazobactam 1.5 g continuous infusion consistently resulted in serum concentrations above the breakpoint for Enterobacteriaceae and many of the susceptible strains of P aeruginosa in this study in 11 healthy subjects. Randomized controlled clinical trials are warranted to determine the appropriate dose of piperacillin/tazobactam.

Related Concept Videos
 01:09
One-Compartment Model: IV Infusion
The one-compartment model for IV infusion uses mathematical equations to describe the rate of change in drug quantity in the body. At steady-state or infusion equilibrium, the drug input...
 01:19
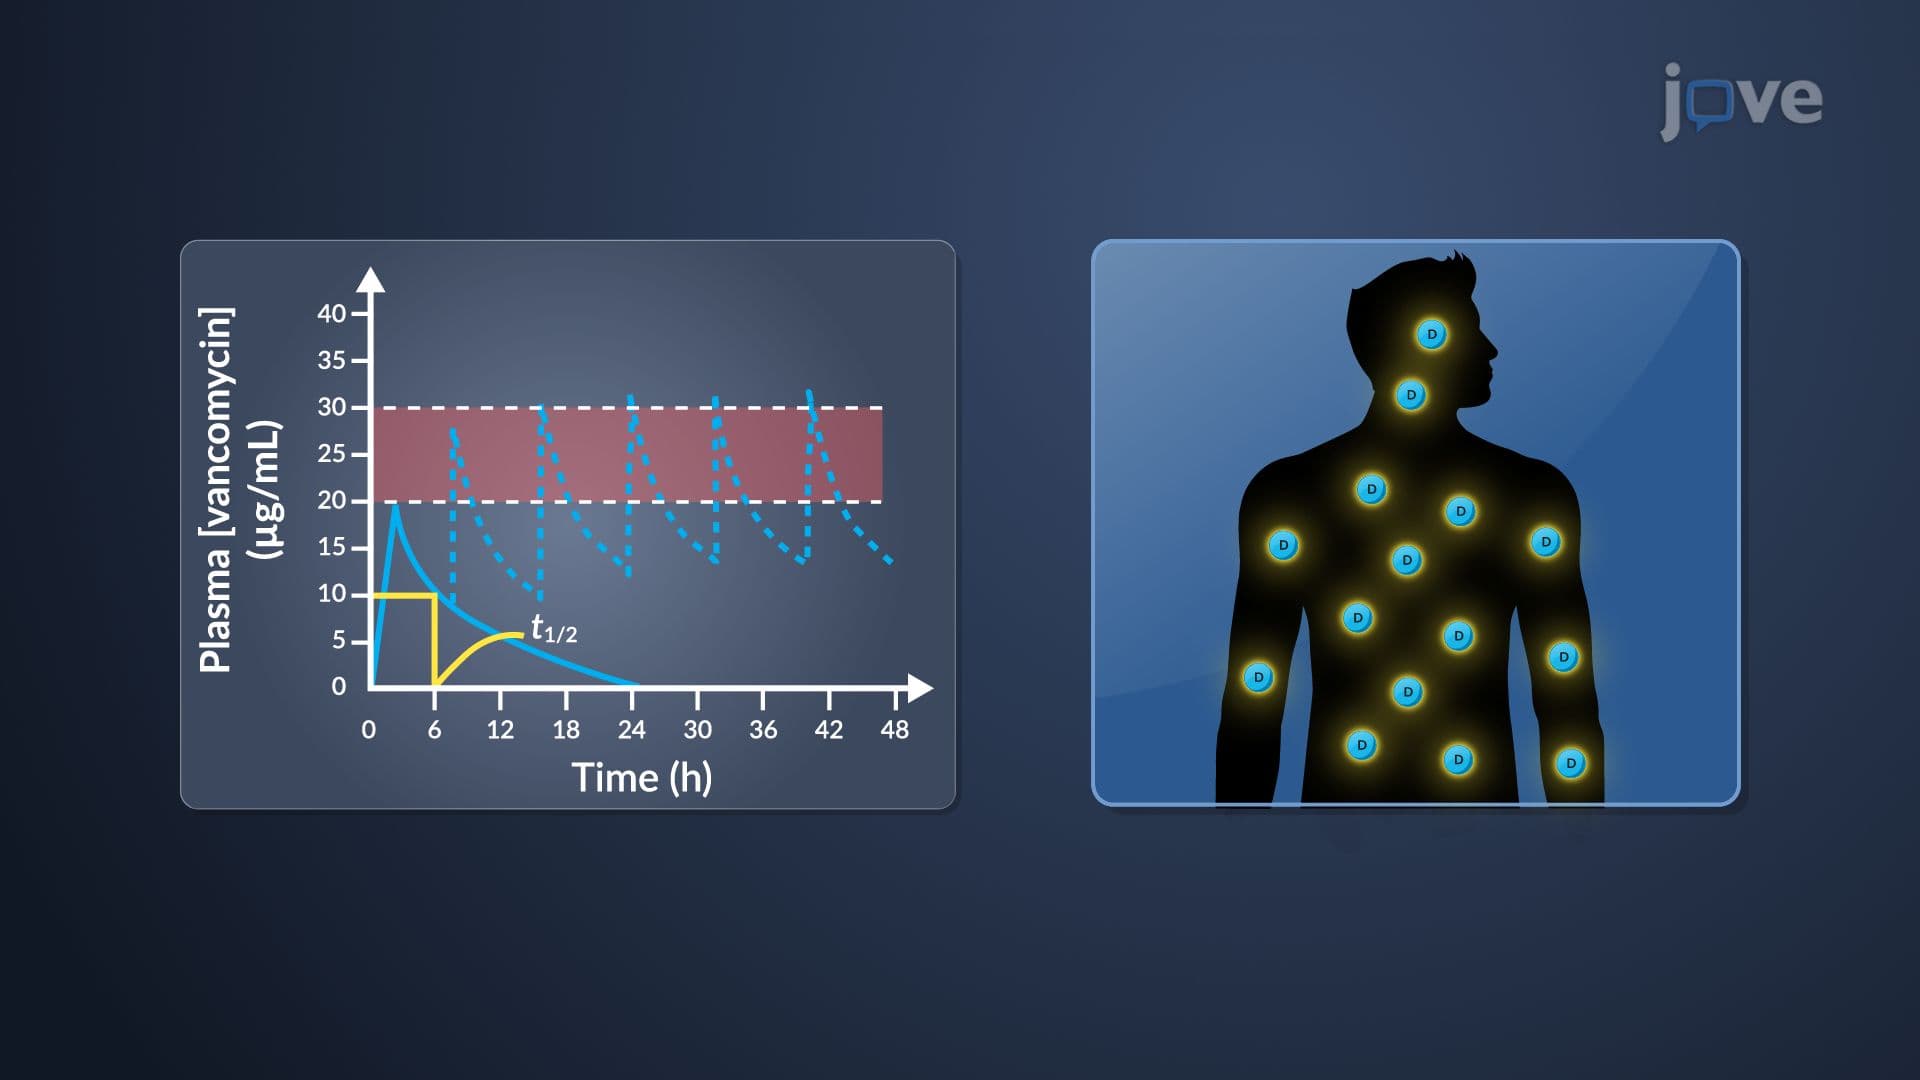
Dosage Interval and Administration Route: Determination Methods
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:15
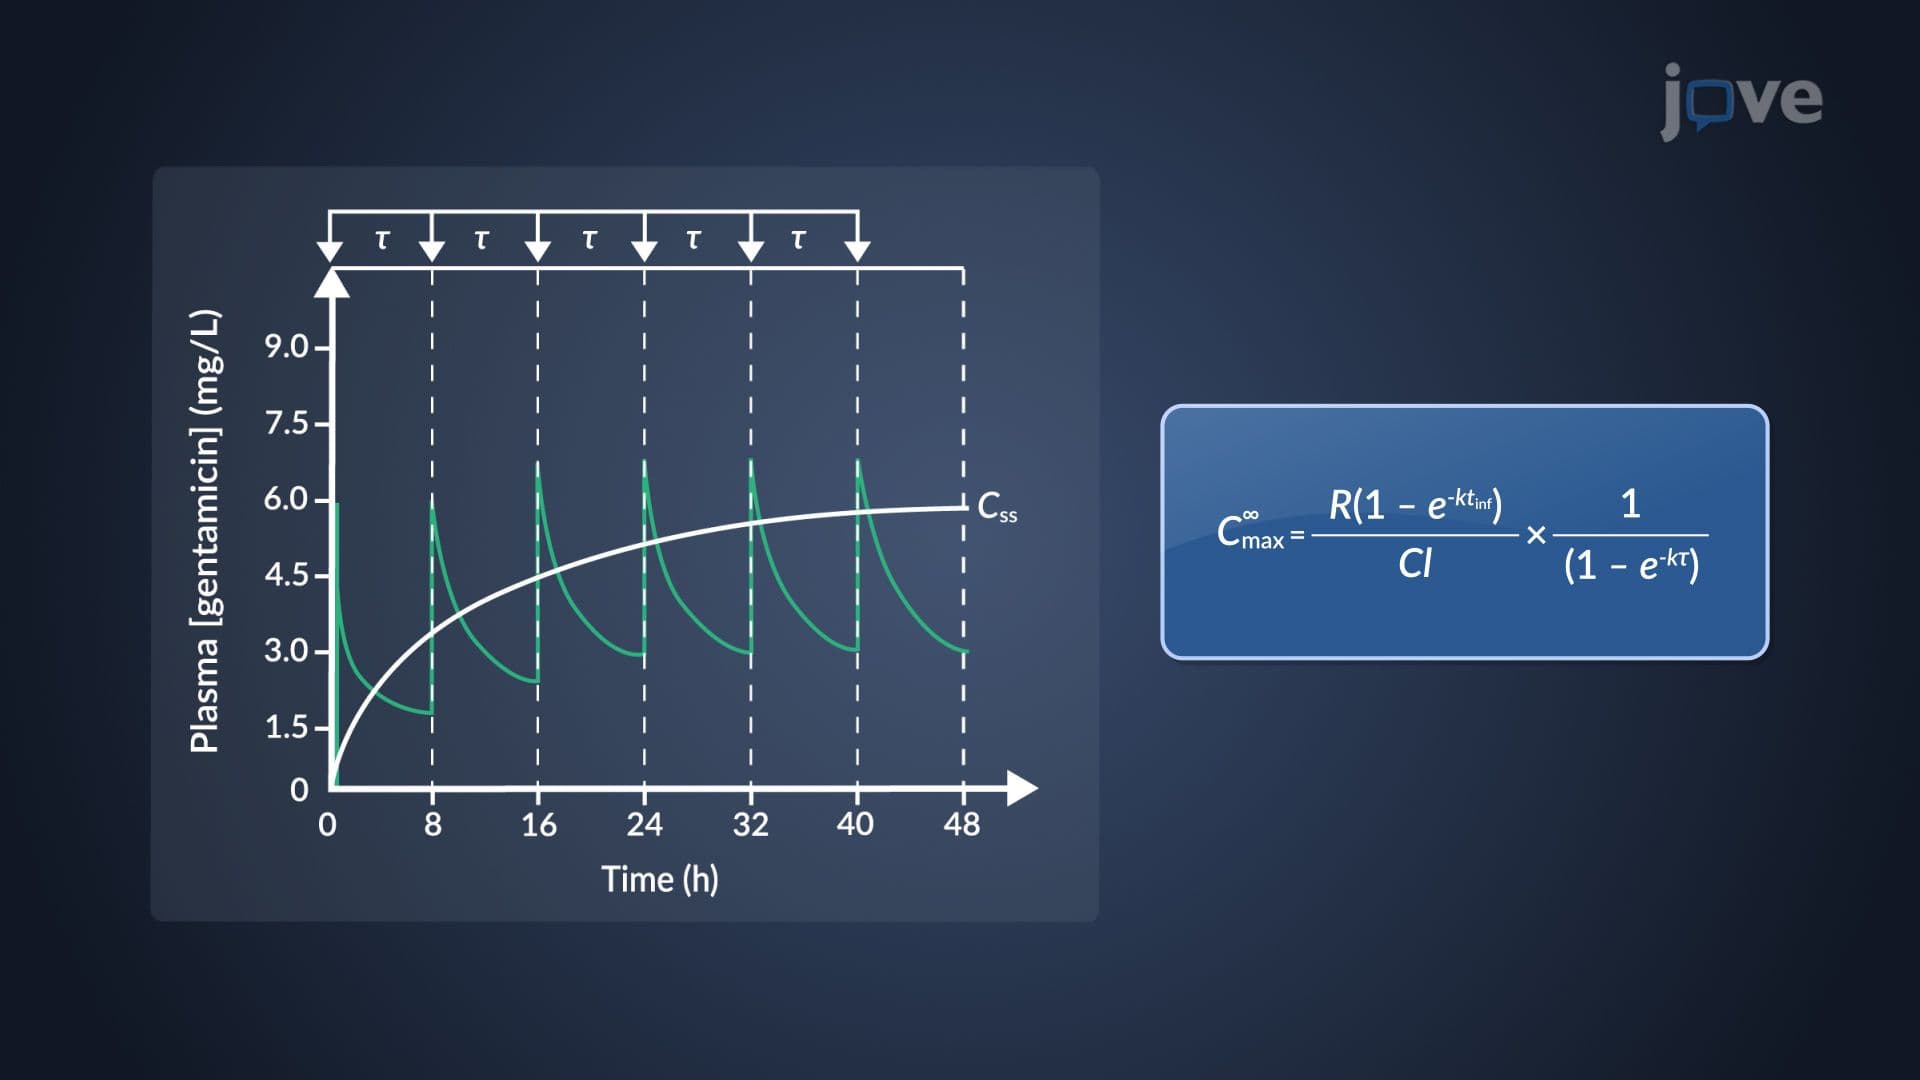
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:28
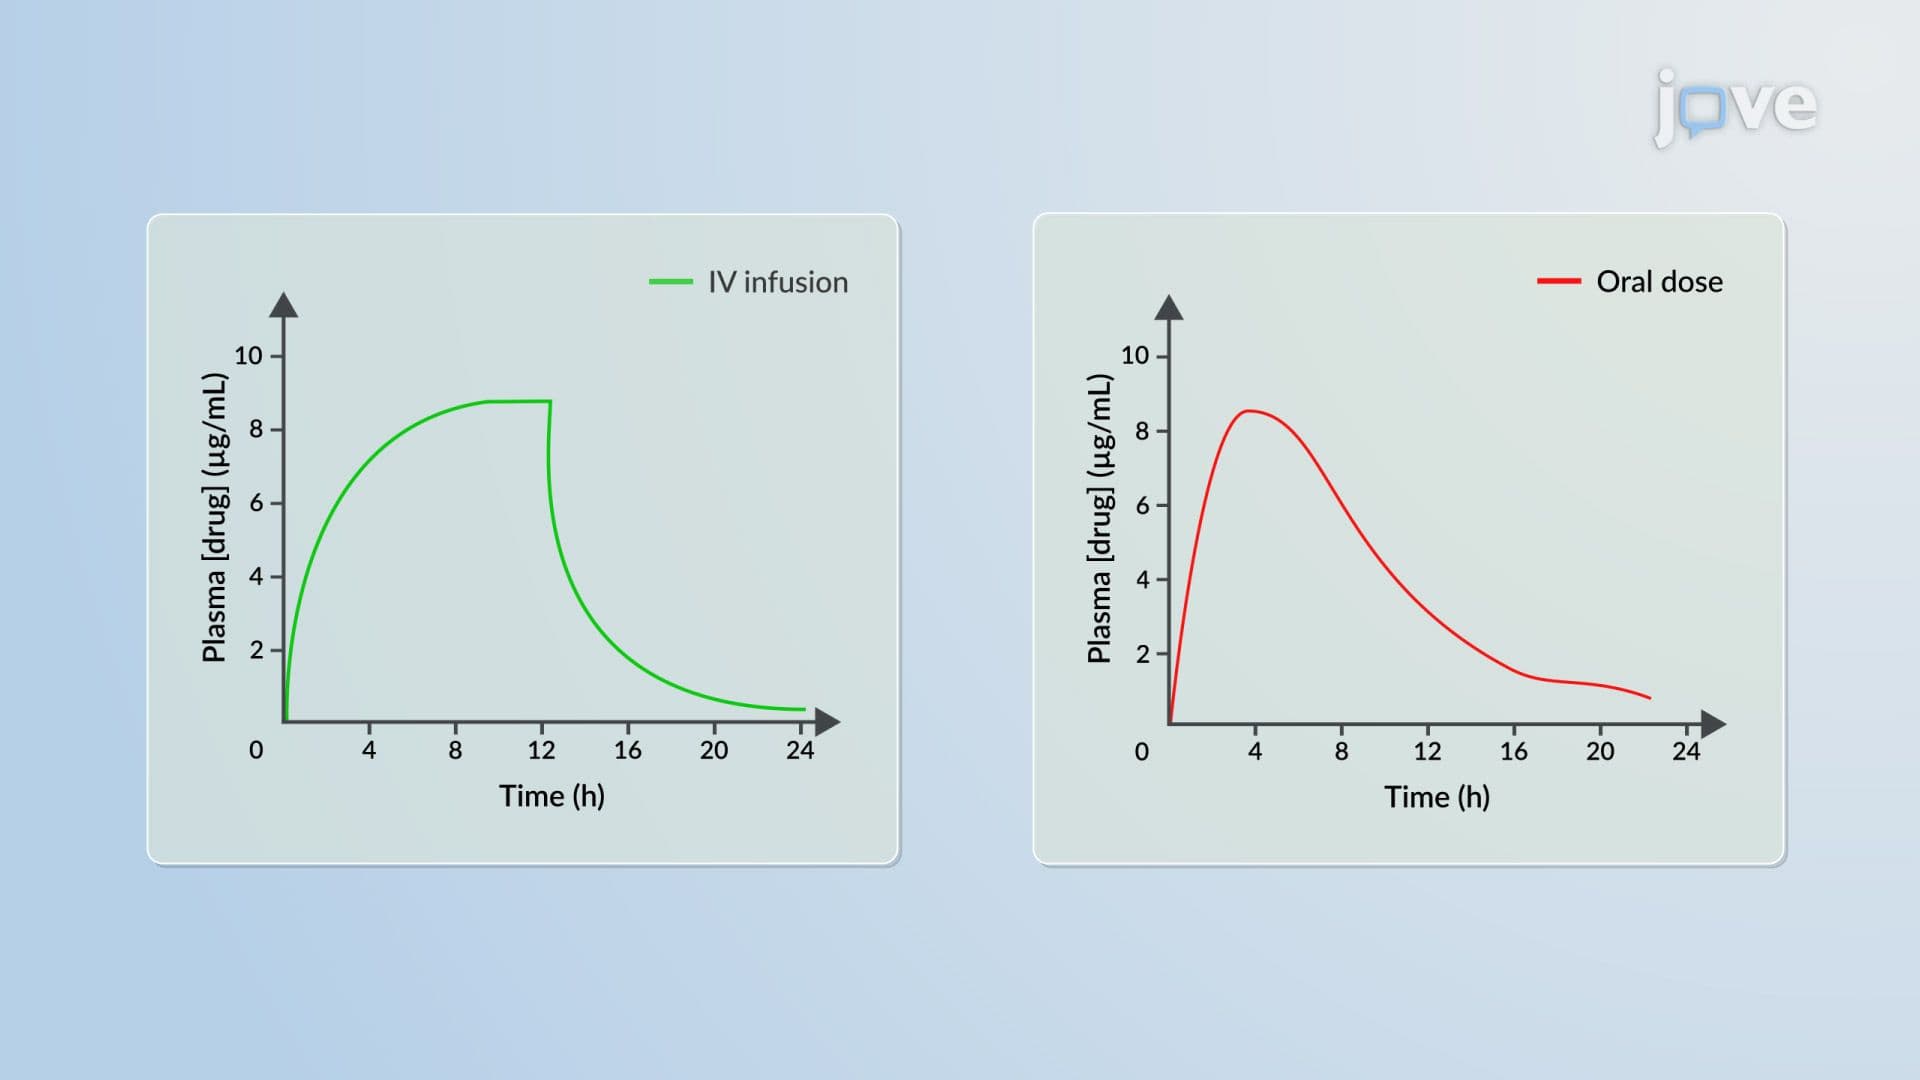
IV Infusion to Oral Dosing: Conversion Methods
 01:14
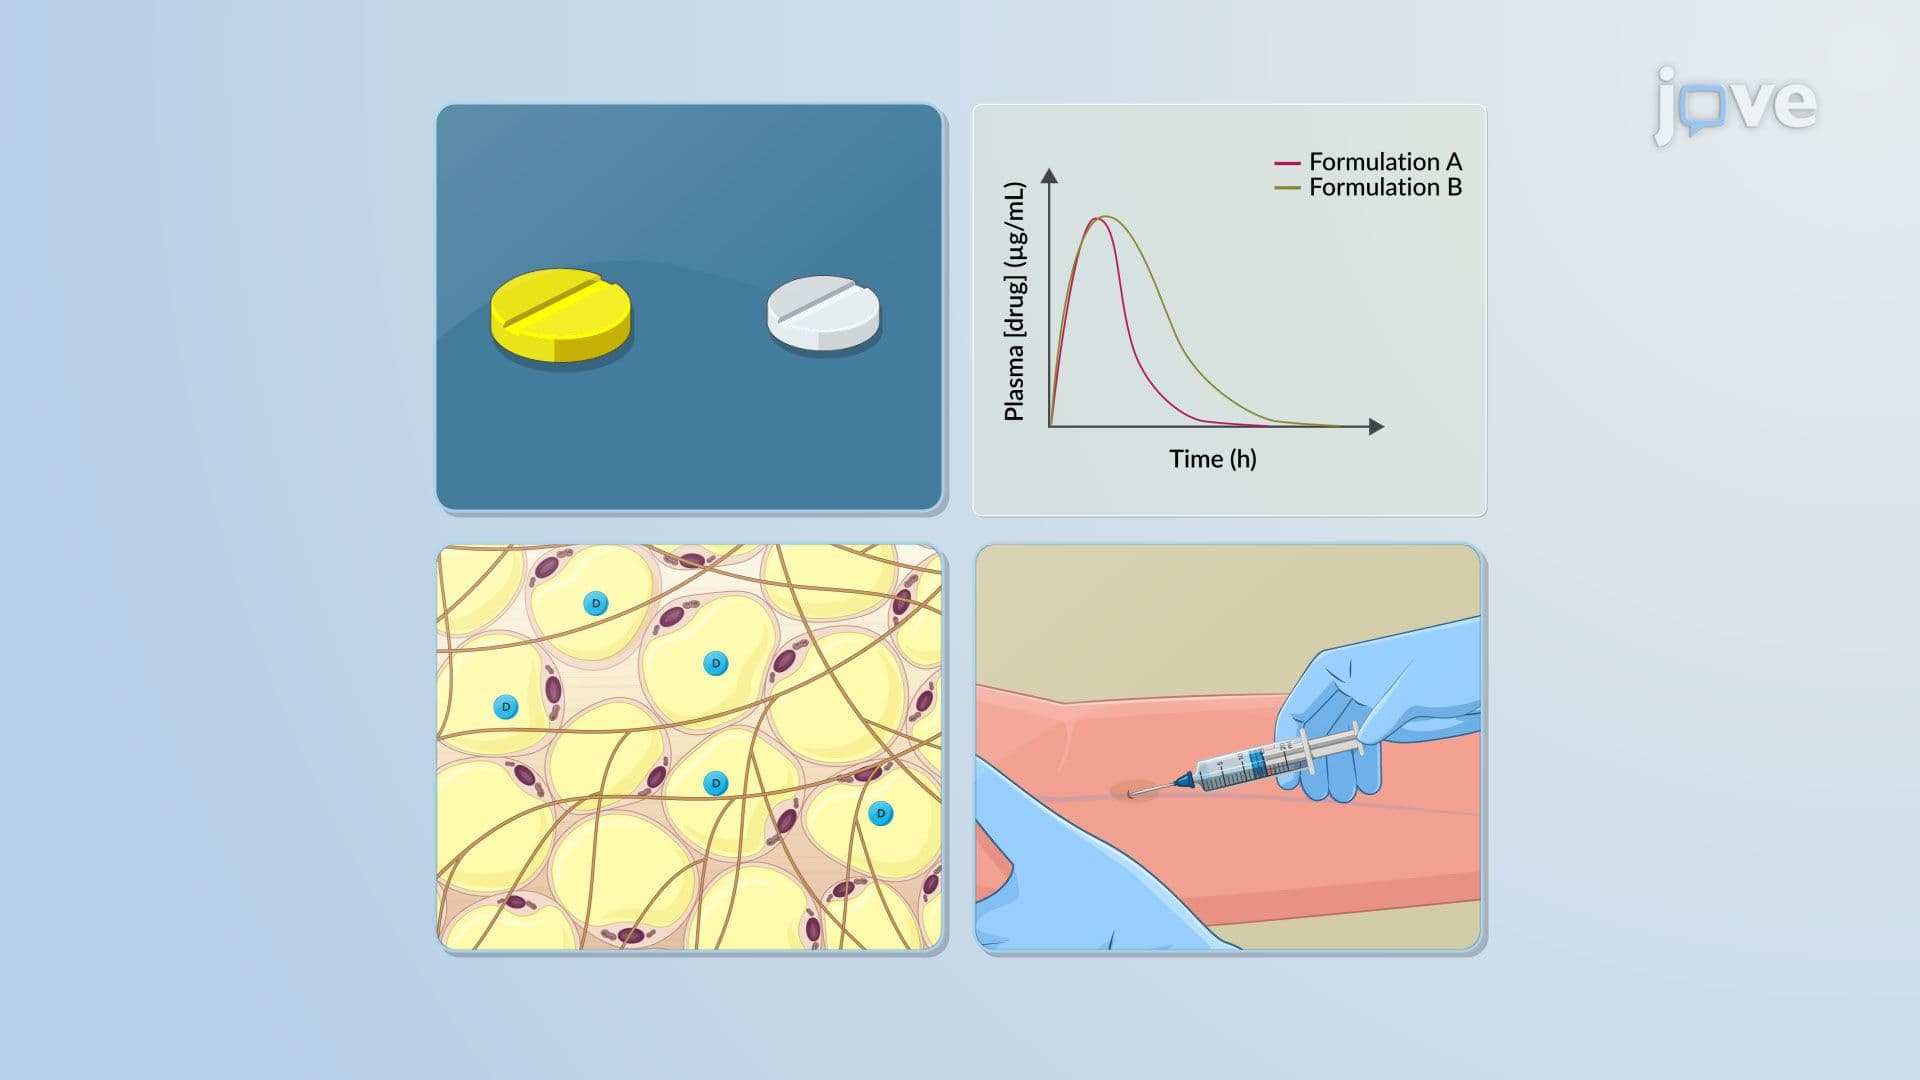
Pharmacokinetic–Pharmacodynamic Relationship: Duration of Dose-Effect Relationship