Quantifying the physician contribution to managed care pharmacy expenses: a random effects approach
Related Experiment Video
Updated: Sep 29, 2026

Inverse Probability of Treatment Weighting (Propensity Score) using the Military Health System Data Repository and National Death Index
Published on: January 8, 2020
Mark E Cowen1, Robert L Strawderman
1Department of Medicine, St. Joseph Mercy Hospital, University of Michigan Medical School, Ann Arbor, MI 48105, USA. cowenm@allegiancellc.com

Background:
Despite the availability of more sophisticated techniques, few alternatives to ordinary least squares (OLS) regression have been utilized to profile physician prescribing in managed care. It is not known to what extent the modest R values derived from OLS models reflect incomplete risk adjustment or widely varying physician prescribing patterns.
Objectives:
To quantify the role of interphysician variability relative to overall variability in managed care pharmacy expenses, and to examine the extent to which different statistical approaches generate meaningful differences in profile results.
Research Design:
Comparison of three basic statistical modeling approaches: OLS, fixed effects regression, and random effects (ie, hierarchical) regression models.
Setting:
Two managed care populations that differed more than 2-fold in per member pharmacy expenditures in 1999, one from the Midwestern United States, the other from three Western States.
Main Outcome Measures:
The intraclass correlation coefficient (ICC, the proportion of variability in expenses attributable to differences among physicians) and the range of projected expenses attributed to each physician's prescribing style.
Results:
The ICCs were small for aggregated pharmacy expenditures, 0.04 or less in both populations. As determined by OLS, the most costly physician contributed 94,399 U.S. dollars in excess expenses to the organization whereas the most parsimonious saved 89,940 U.S. dollars. When derived from random effects models, the range in performance was 63% of that derived from OLS.
Conclusions:
In the populations studied, systematic prescribing differences among physicians were small relative to the overall variability in pharmacy expenses, suggesting other factors were more likely driving these costs. Random effects models generated smaller estimates of the individual physicians' contribution to costs, sometimes considerably, relative to those derived from OLS and fixed effects approaches.
Related Concept Videos
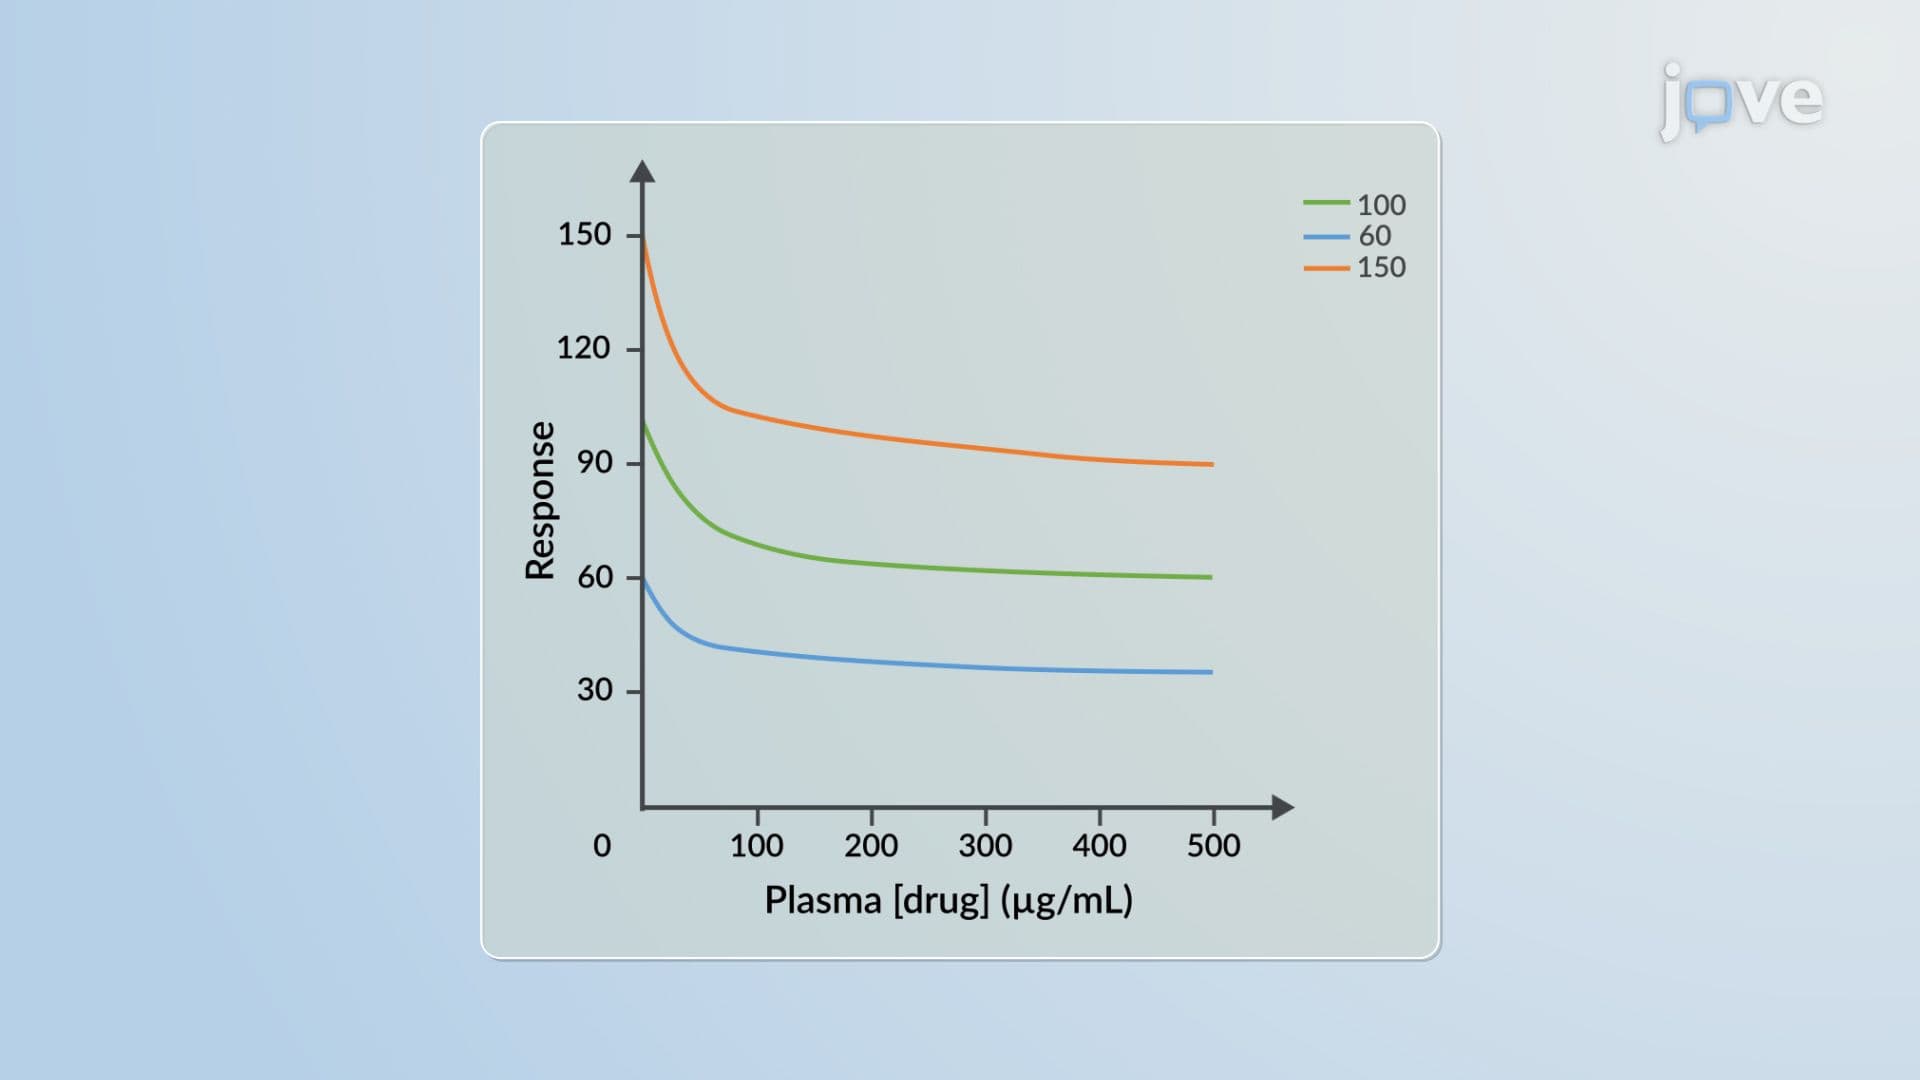 01:09
Pharmacodynamic Models: Additive and Proportional Drug Effect Model
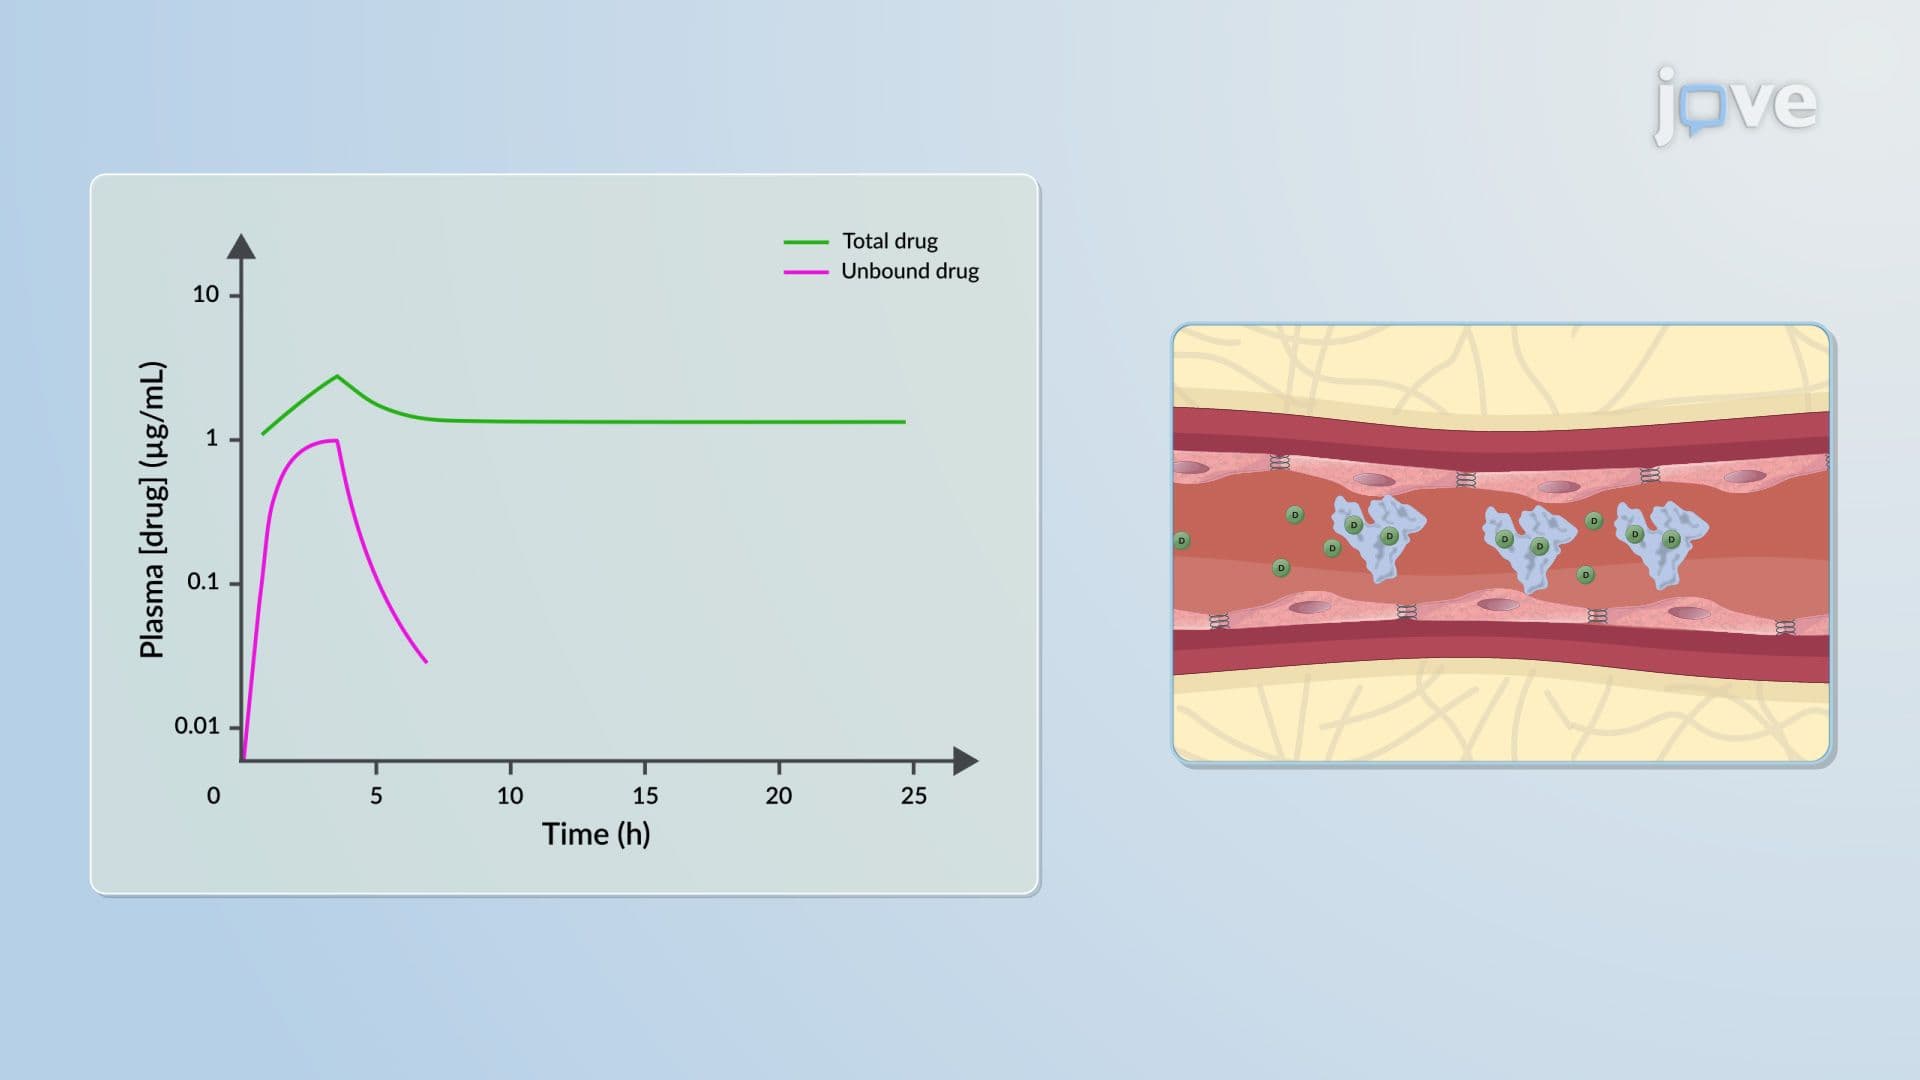 01:24
Pharmacokinetic–Pharmacodynamic Relationship: Problems
 00:59
Model-Independent Approaches for Pharmacokinetic Data: Noncompartmental Analysis
One important characteristic of noncompartmental analyses is that drug exposure increases proportionally with increasing doses. This relationship...
 01:15
Pharmacodynamic Models: Linear Concentration–Effect Model
 01:12
Analysis of Population Pharmacokinetic Data
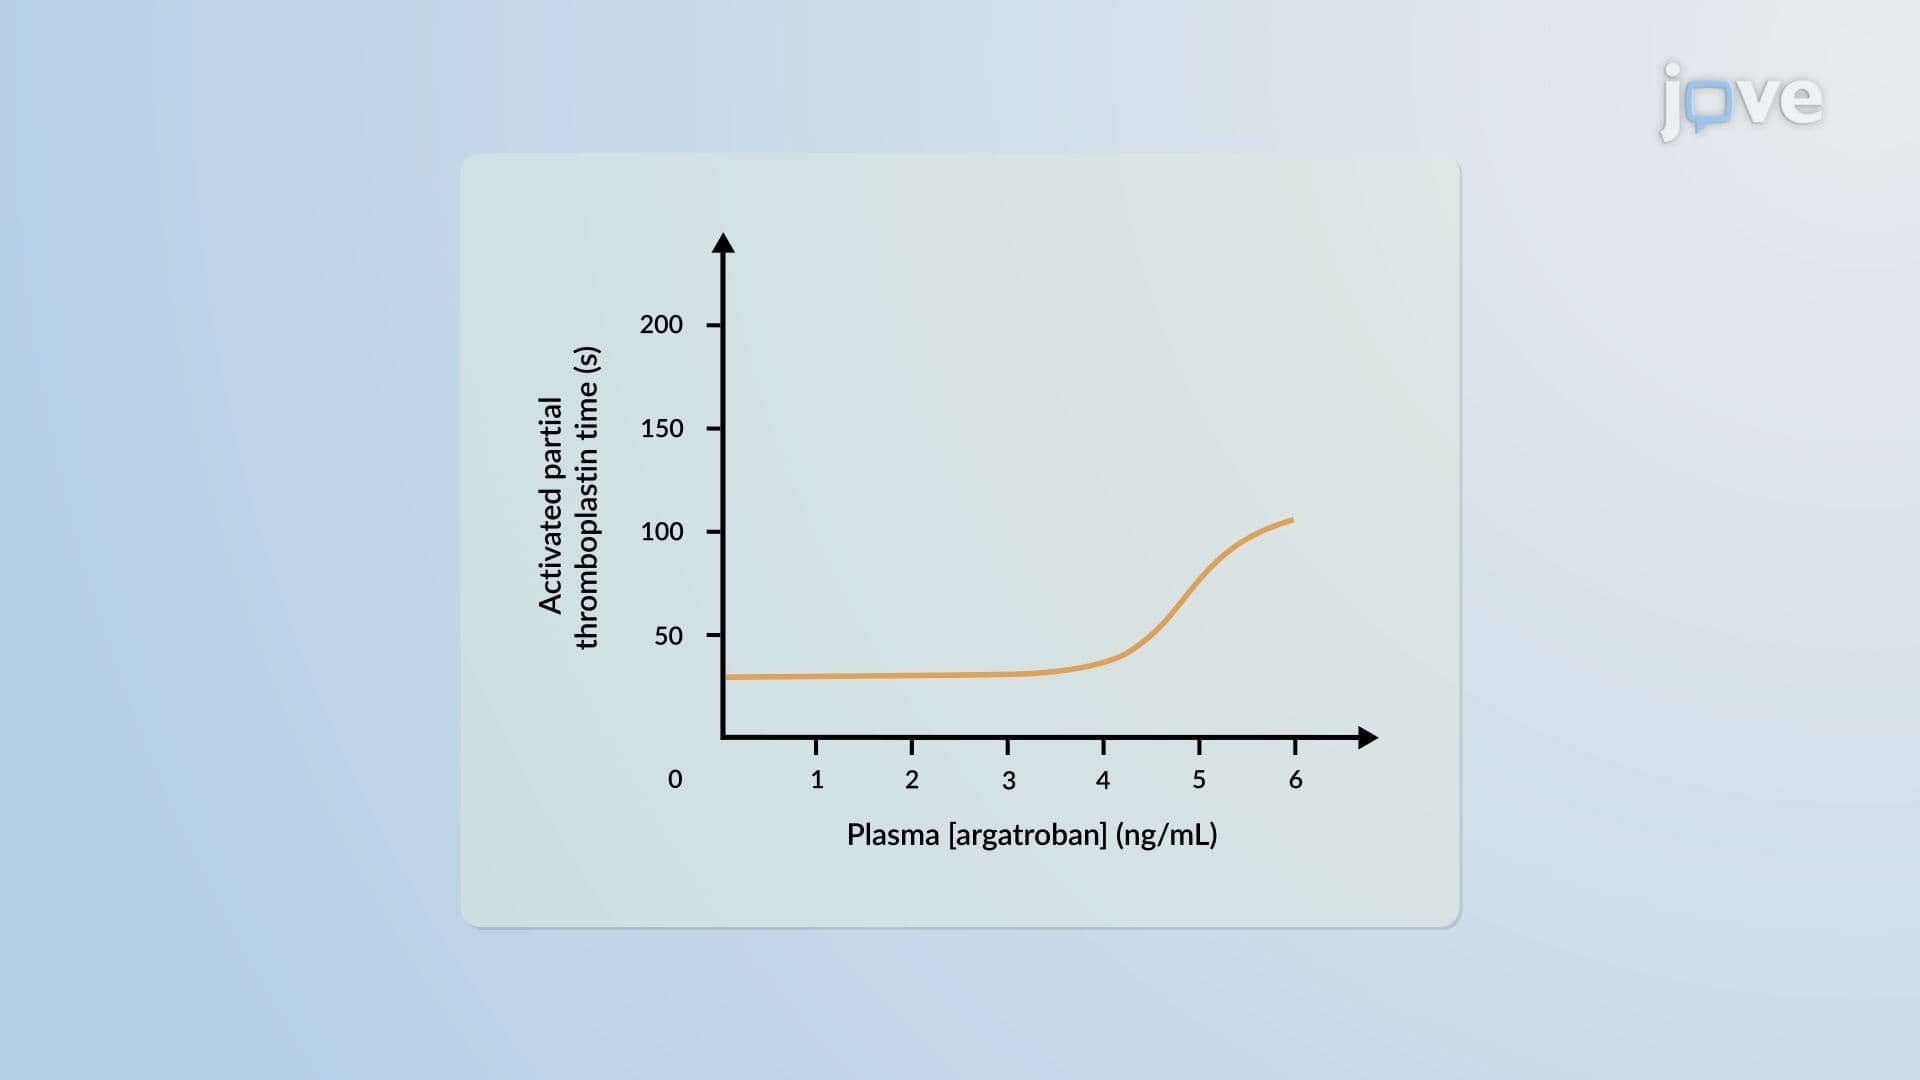 01:29
Pharmacodynamic Models: Direct Effect Model and Indirect Response Model