Pityriasis lichenoides: a clonal T-cell lymphoproliferative disorder
Related Experiment Video
Updated: Sep 29, 2026

Wild-type Blocking PCR Combined with Sanger Sequencing for Detection of Low-frequency Somatic Mutation
Published on: August 23, 2024
Cynthia Magro1, A Neil Crowson, Al Kovatich
1Department of Pathology Ohio State University Medical Center, Columbus, OH 43210, USA.

Abstract:
Pityriasis lichenoides (PL) is a papulosquamous disorder often considered a form of reactive dermatosis and classified with small plaque parapsoriasis (digitate dermatosis). However, some patients with PL have developed large plaque parapsoriasis (LPP) and mycosis fungoides (MF), and lymphoid atypia and T-cell clonality have been reported in lesions of PL. We set out to explore the possibility that PL is a form of T-cell dyscrasia. Cases were selected by natural language search from an outpatient dermatopathology database; 35 cases were reviewed and clinicians and patients were contacted. Hematoxylin and eosin-stained sections were examined and immunophenotyping was carried out on paraffin-embedded, formalin-fixed tissue using antibodies to CD2, CD3, CD4, CD5, CD7, CD8, CD20, CD30, and CD56. In paraffin-embedded tissue, T-cell receptor (TCR)-gamma chain rearrangement was sought through polymerase chain reaction single stranded conformational polymorphism analysis. There were 14 males and 21 females with a mean age of 40 years held clinically to have PL chronica (PLC) (28 cases) and/or PL et varioliformis acuta (PLEVA) (7 cases). Five patients developed large atrophic poikilodermatous and/or annular plaques compatible with MF and/or LPP in a background of typical PLC. All biopsies showed tropism of lymphocytes to an epidermis manifesting psoriasiform hyperplasia, dyskeratosis, parakeratosis, and intraepithelial collections of Langerhans' cells and lymphocytes mimicking Pautrier's microabascesses. Epidermal atrophy, dermal fibroplasia, poikilodermatous alterations, and a dominance of intraepidermal cerebriform cells were seen only in patients with chronic persistent disease (i.e., PLC) and in some cases corresponded with clinical progression to MF. All cases had a T cell-dominant infiltrate, with a CD7 deletion in 21 of 32 biopsies examined; the CD7-negative cells were typically the largest and most atypical forms, often in a cohesive array within the upper layers of the epidermis. In 17 biopsies in which a CD4 stain was satisfactory for evaluation, 50% or more of the intraepidermal population was CD4 positive in 8 biopsies, whereas in 11 biopsies 50% or more of the dermal infiltrate was CD4 positive. The CD4-positive cells frequently had a cerebriform nuclear morphology and were CD7 negative. Most cases had an admixture of CD8-positive lymphocytes in excess of 40% or more of the intraepidermal and/or dermal infiltrate; it was the dominant intraepidermal infiltrate in 10 cases. The CD8-positive cells, typically small, round, and CD7 positive, showed a directed pattern of migration into acrosyringia and suprapapillary plates, with satellitosis around CD4-positive/CD8-negative/CD7-negative atypical lymphocytes. CD56 positivity was seen among the intraepidermal lymphoid cells and roughly paralleled the CD8 profile. In general, CD8-positive lymphocytes dominated in cases of PLEVA, whereas CD4-positive lymphocytes were very conspicuous and composed the dominant intraepidermal populace only in those biopsies of progressive PL/PLC. Clonality was shown in 25 of 27 biopsies in which amplifiable DNA was obtained. Intraepithelial atypical lymphocytes, phenotypic abnormalities, and TCR-gamma rearrangements suggest that PLC and PLEVA are a form of T-cell dyscrasia. Lesions may follow a recalcitrant course characteristic of MF and premycotic disorders such as LPP. The aberrant phenotype cell is similar to that defining MF: a CD4-positive T lymphocyte with a CD5 and CD7 deletion. Directed epidermal migration seen in biopsies procured from incipient lesions along with occasional temporal association to viral or drug exposure suggests that an abnormal immune response to an antigenic trigger may be the inciting event.
Related Concept Videos
 01:16
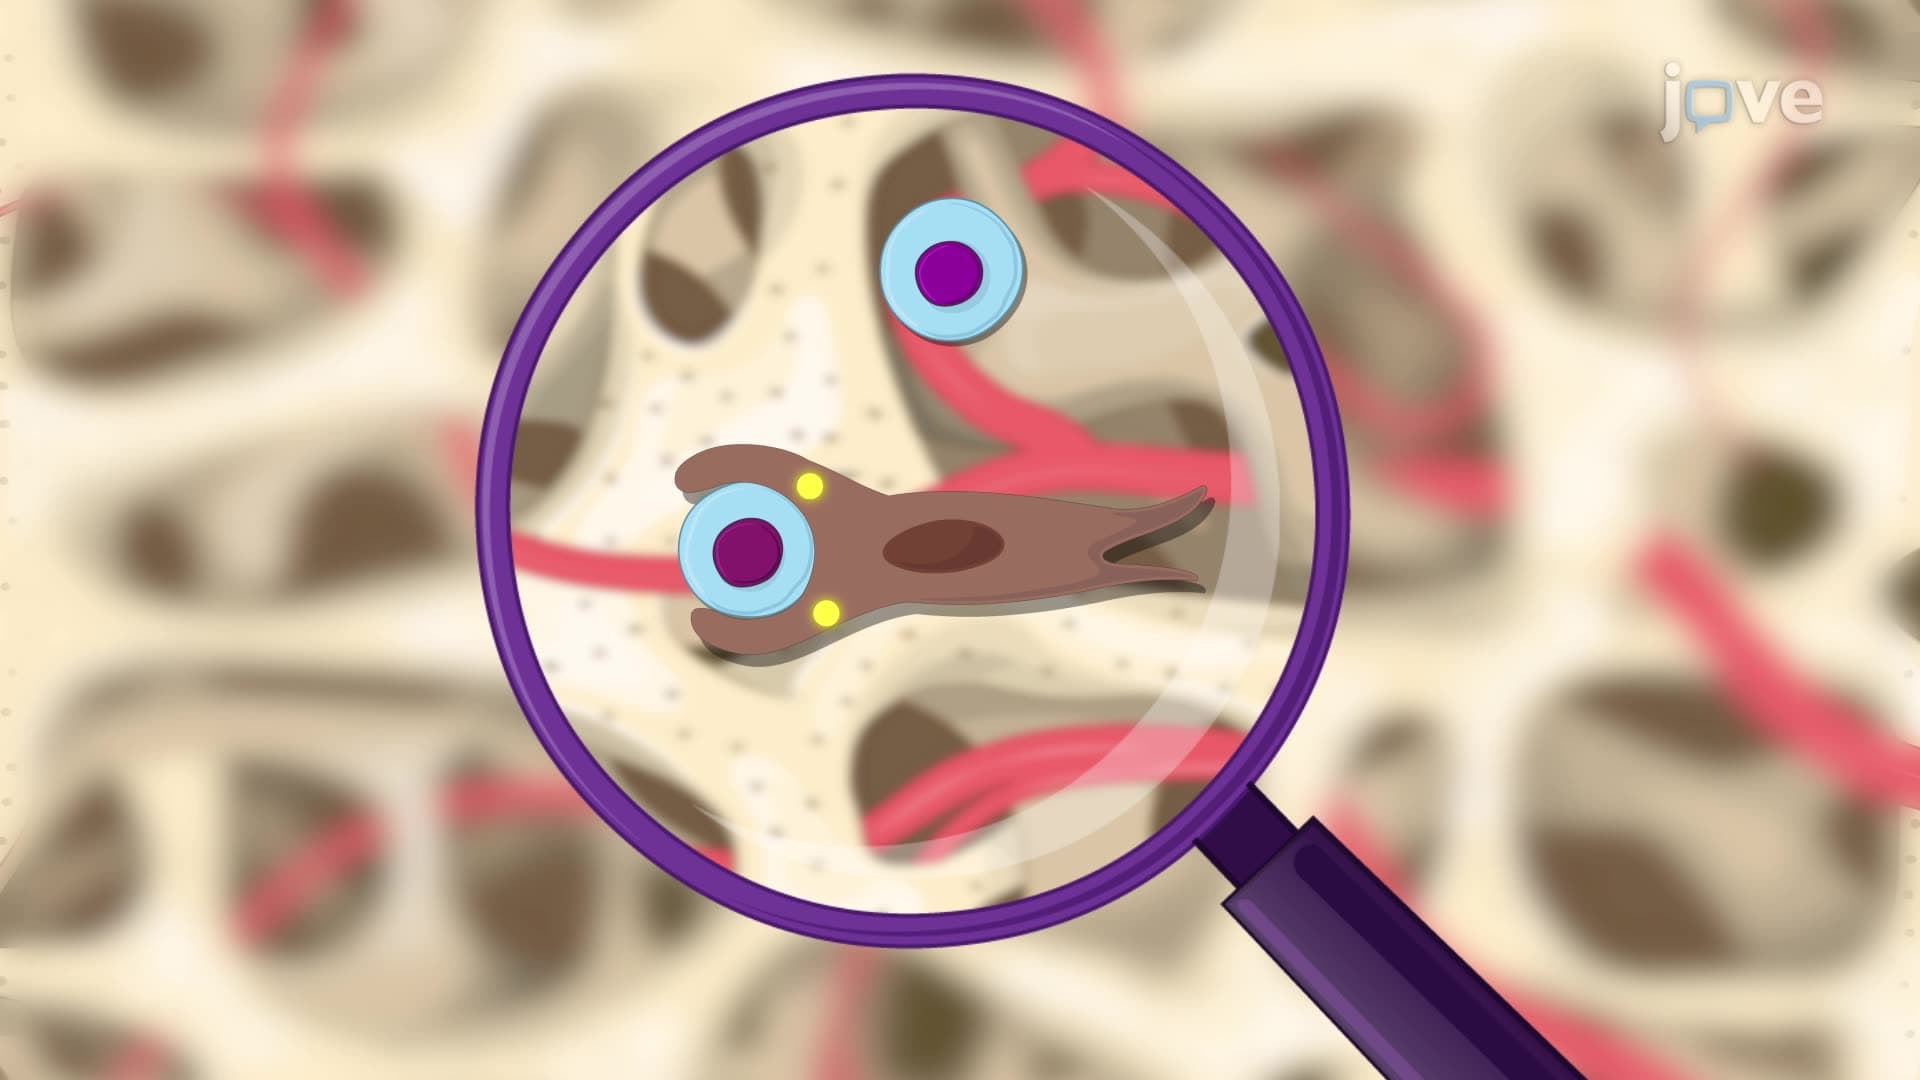
Primary Lymphoid Organs
The red bone marrow is a soft, spongy tissue nestled in the interior of long bones such as the humerus and femur. It is the site...
 01:22
T Cell Activation and Clonal Selection
Naive T cells that have not yet encountered an antigen express two primary CD...
 01:15
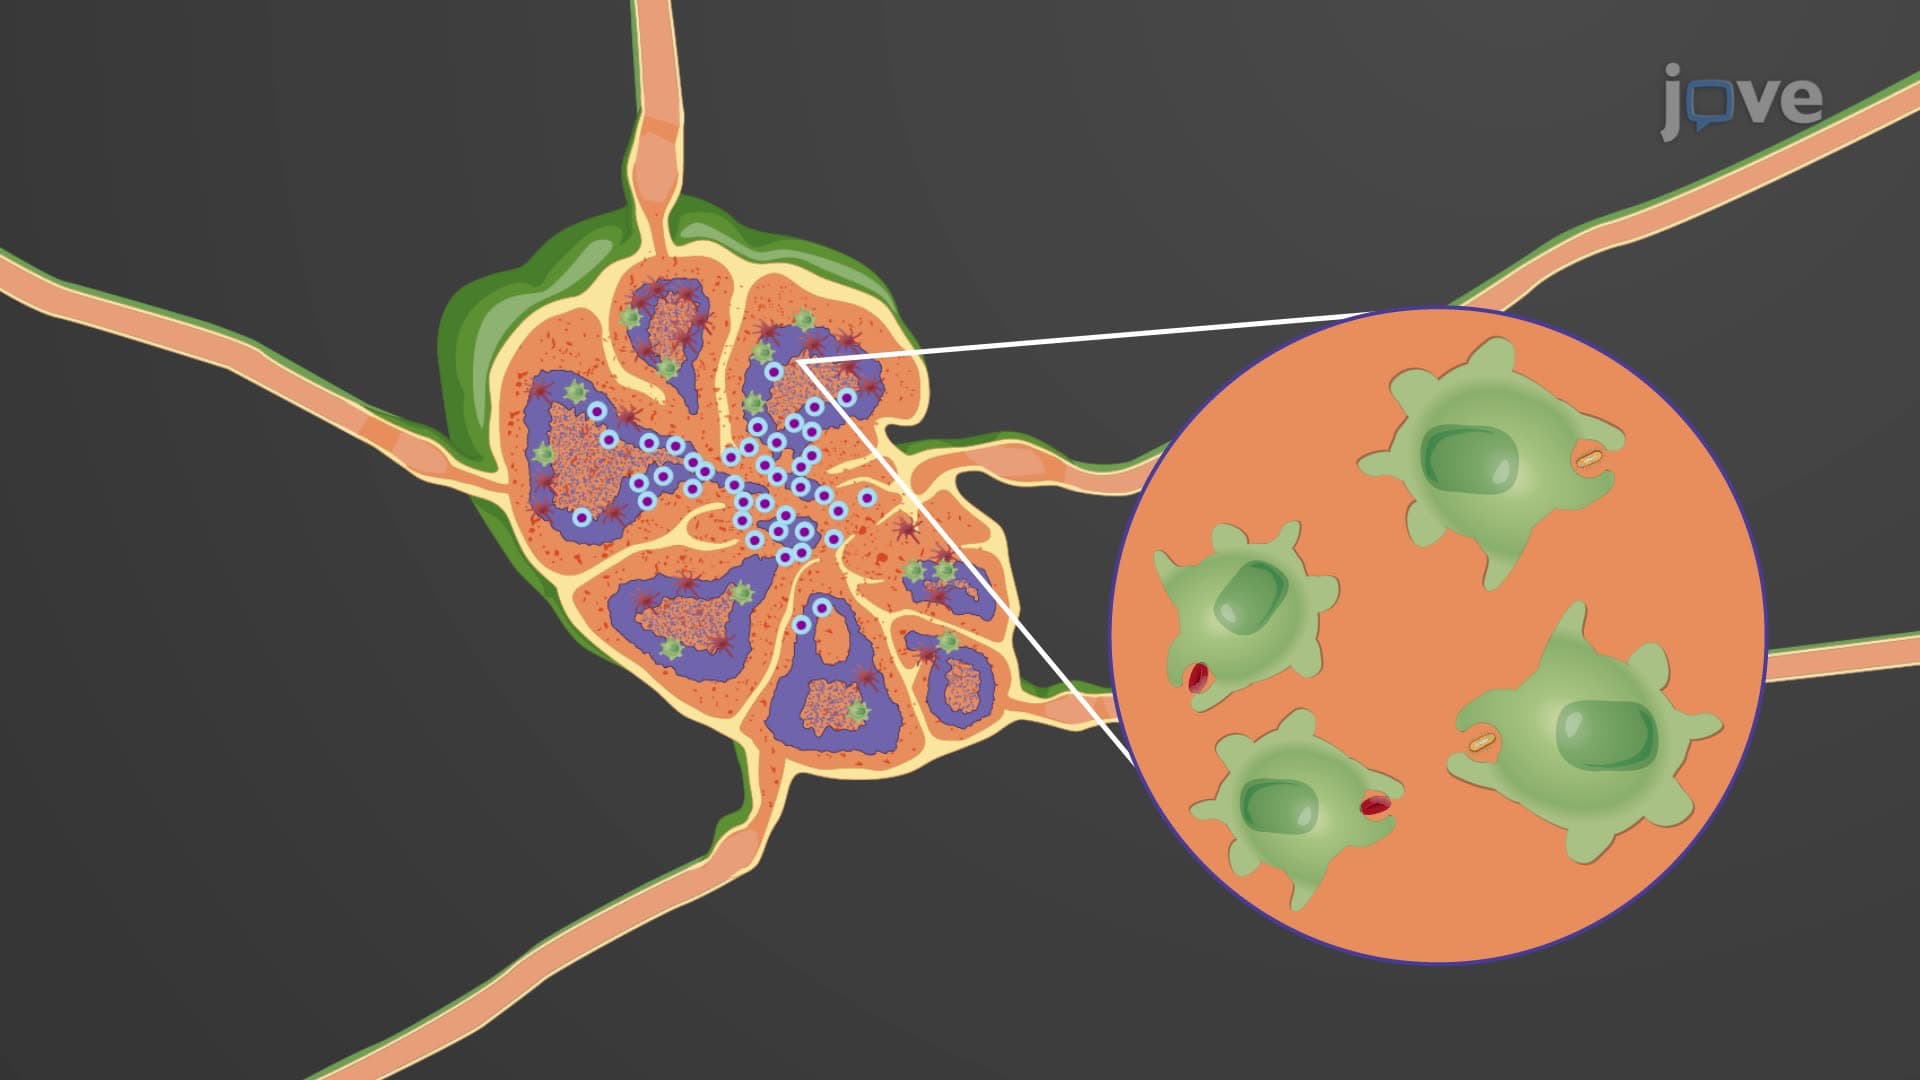
Secondary Lymphoid Organs
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...
 01:18
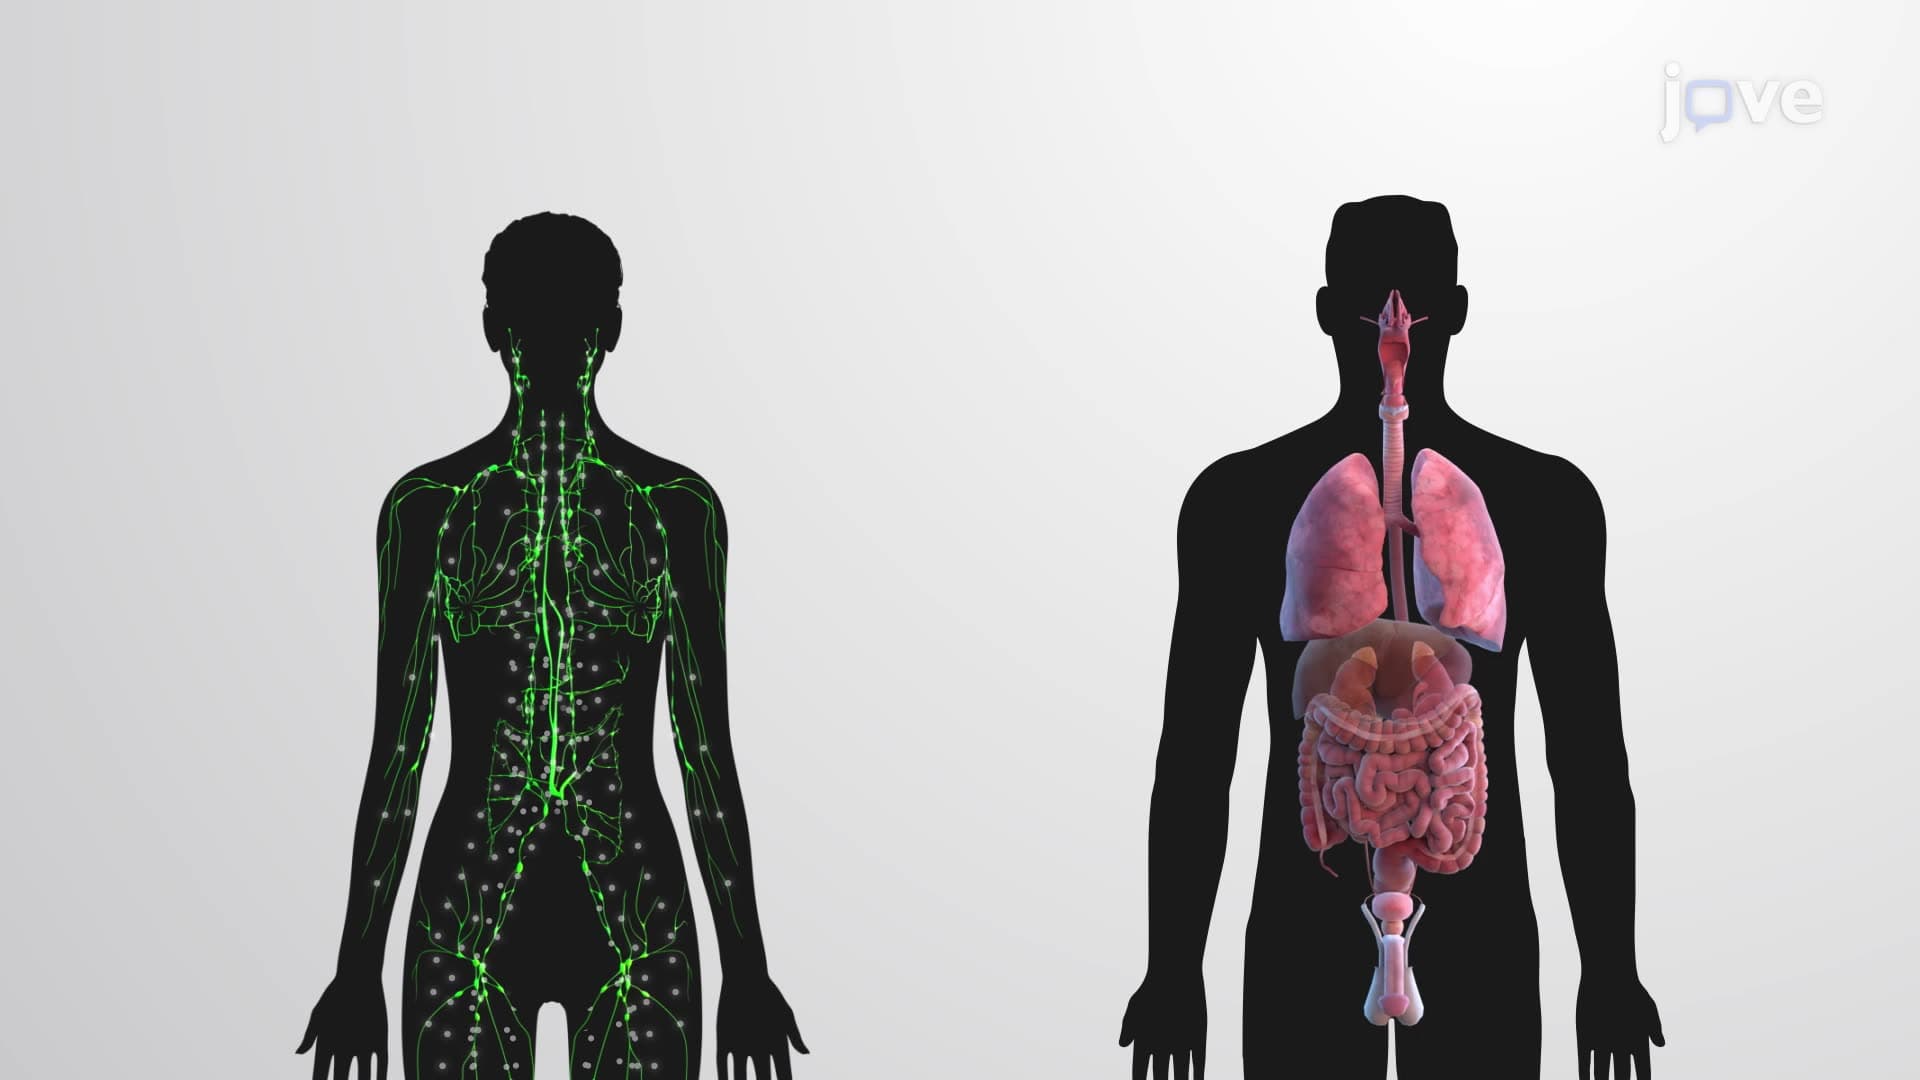
Lymphoid Cells and Tissues
Lymphoid cells consist of various types of immune system cells. These include B and T lymphocytes, which are responsible for producing antibodies and killing infected cells, respectively. Dendritic cells act as messengers between the innate and adaptive...
 01:24
T Cell Types and Functions
Th1 cells stimulate dendritic cells to express necessary co-stimulatory molecules on their surfaces for...