Conduction slowing in diabetic distal polyneuropathy

David N Herrmann1, Michele L Ferguson, Eric L Logigian

  • 1Department of Neurology, University of Rochester, SMH 601 Elmwood Avenue, Box 673, Rochester, New York 14642, USA. David_Herrmann@urmc.rochester.edu

Muscle & Nerve
|September 5, 2002
PubMed

Related Concept Videos

Diabetic Neuropathy01:22

Diabetic Neuropathy

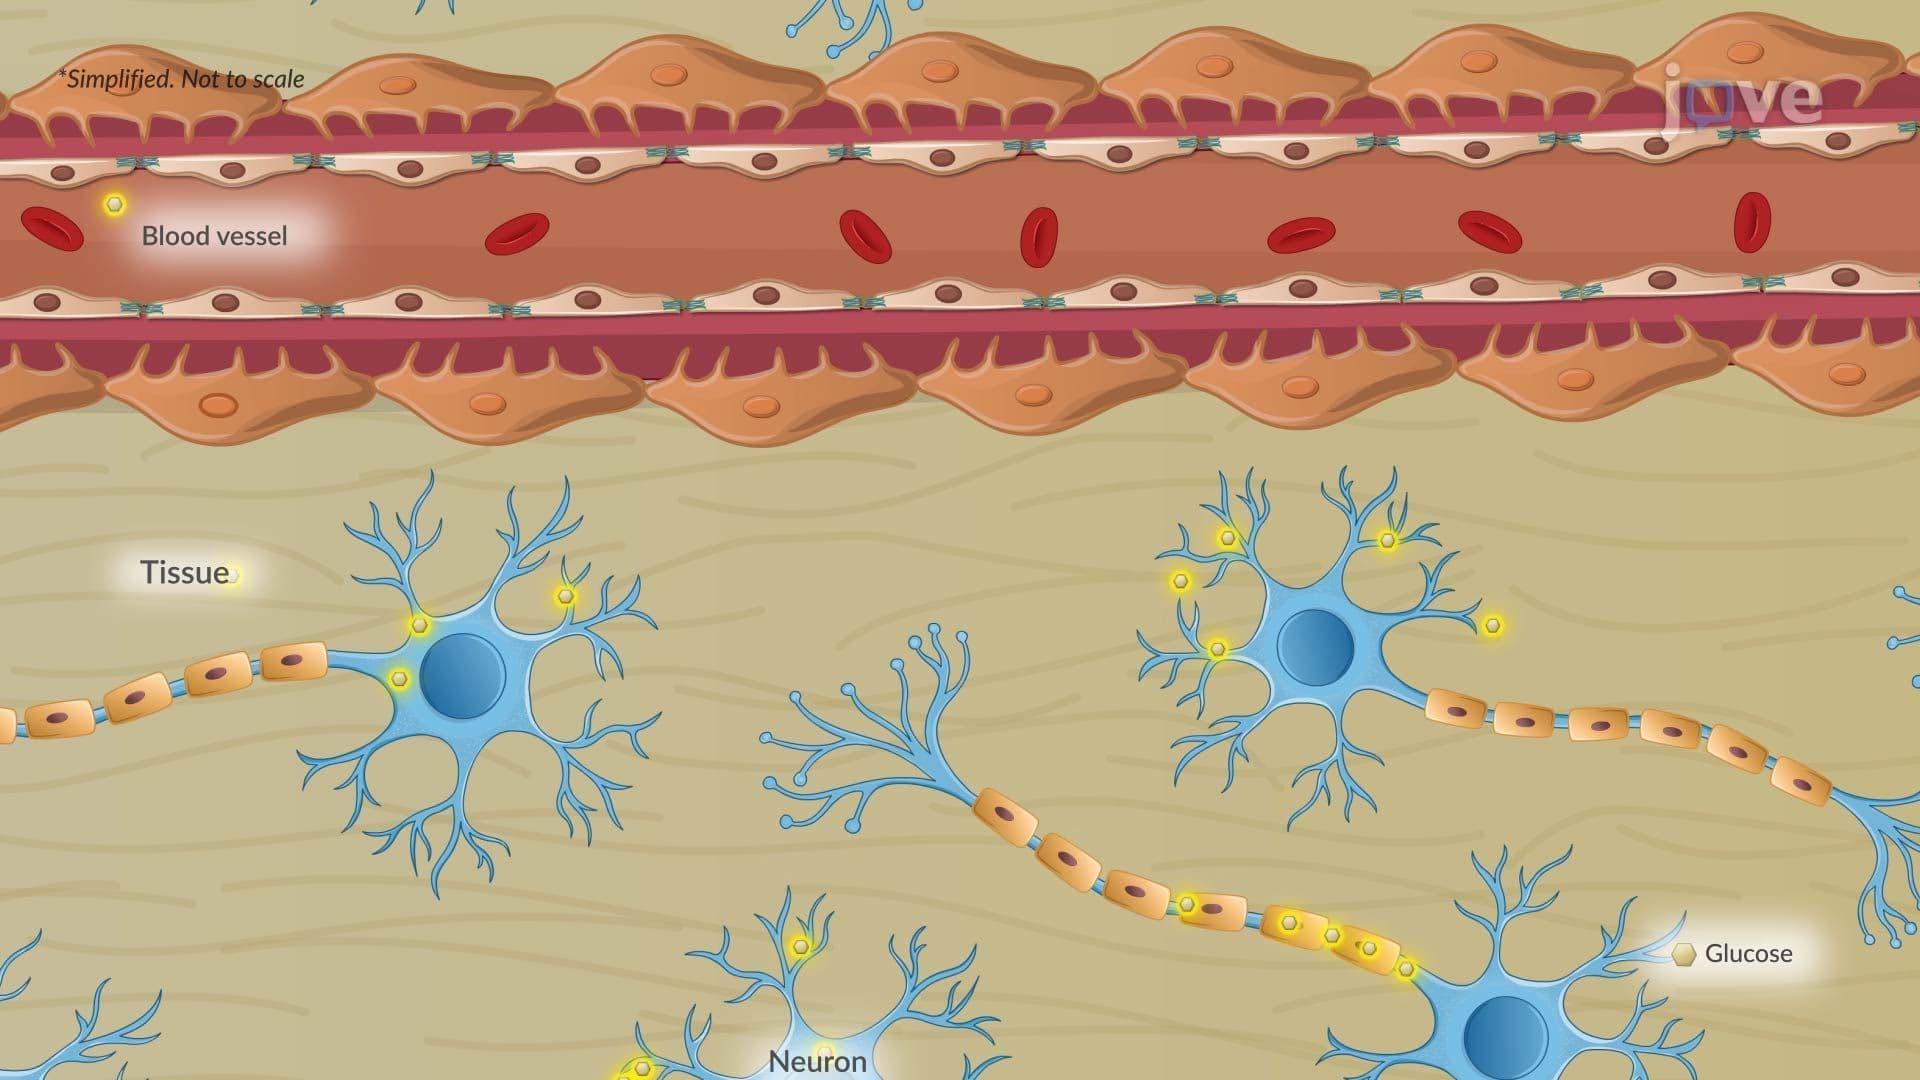
DefinitionDiabetic neuropathy is nerve damage caused by long-standing diabetes mellitus. It results directly from prolonged high blood sugar levels.PathophysiologyThe pathophysiology of diabetic neuropathy involves both metabolic and vascular disturbances triggered by chronic hyperglycemia.Metabolic injury: Elevated glucose levels activate the polyol pathway within nerve cells, leading to the accumulation of sorbitol and fructose. This increases oxidative stress, disrupts normal nerve...
Diabetic Nephropathy01:28

Diabetic Nephropathy

Definition Diabetic nephropathy is a chronic kidney complication that results from prolonged hyperglycemia.Prevalence It is the most common cause of chronic kidney disease (CKD) and end-stage renal disease (ESRD) worldwide, affecting up to half of individuals with diabetes.Pathophysiology • Sustained hyperglycemia triggers multiple hemodynamic and metabolic changes in the kidney. • Early in the disease, increased renal blood flow and glomerular hyperfiltration occur due to afferent arteriolar...
Diabetic Foot Ulcer01:31

Diabetic Foot Ulcer

Definition A diabetic foot ulcer (DFU) is a chronic, non-healing wound that develops in individuals with diabetes. It typically occurs on pressure-bearing areas such as the heel, metatarsal heads, or hallux, and carries a high risk of infection and amputation.Pathophysiology • The development of DFUs can be explained by four interconnected mechanisms: neuropathy, ischemia, infection, and impaired wound healing. • Neuropathy is the most common factor. Sensory neuropathy reduces pain perception,...
Type I Diabetes II: Pathophysiology01:26

Type I Diabetes II: Pathophysiology

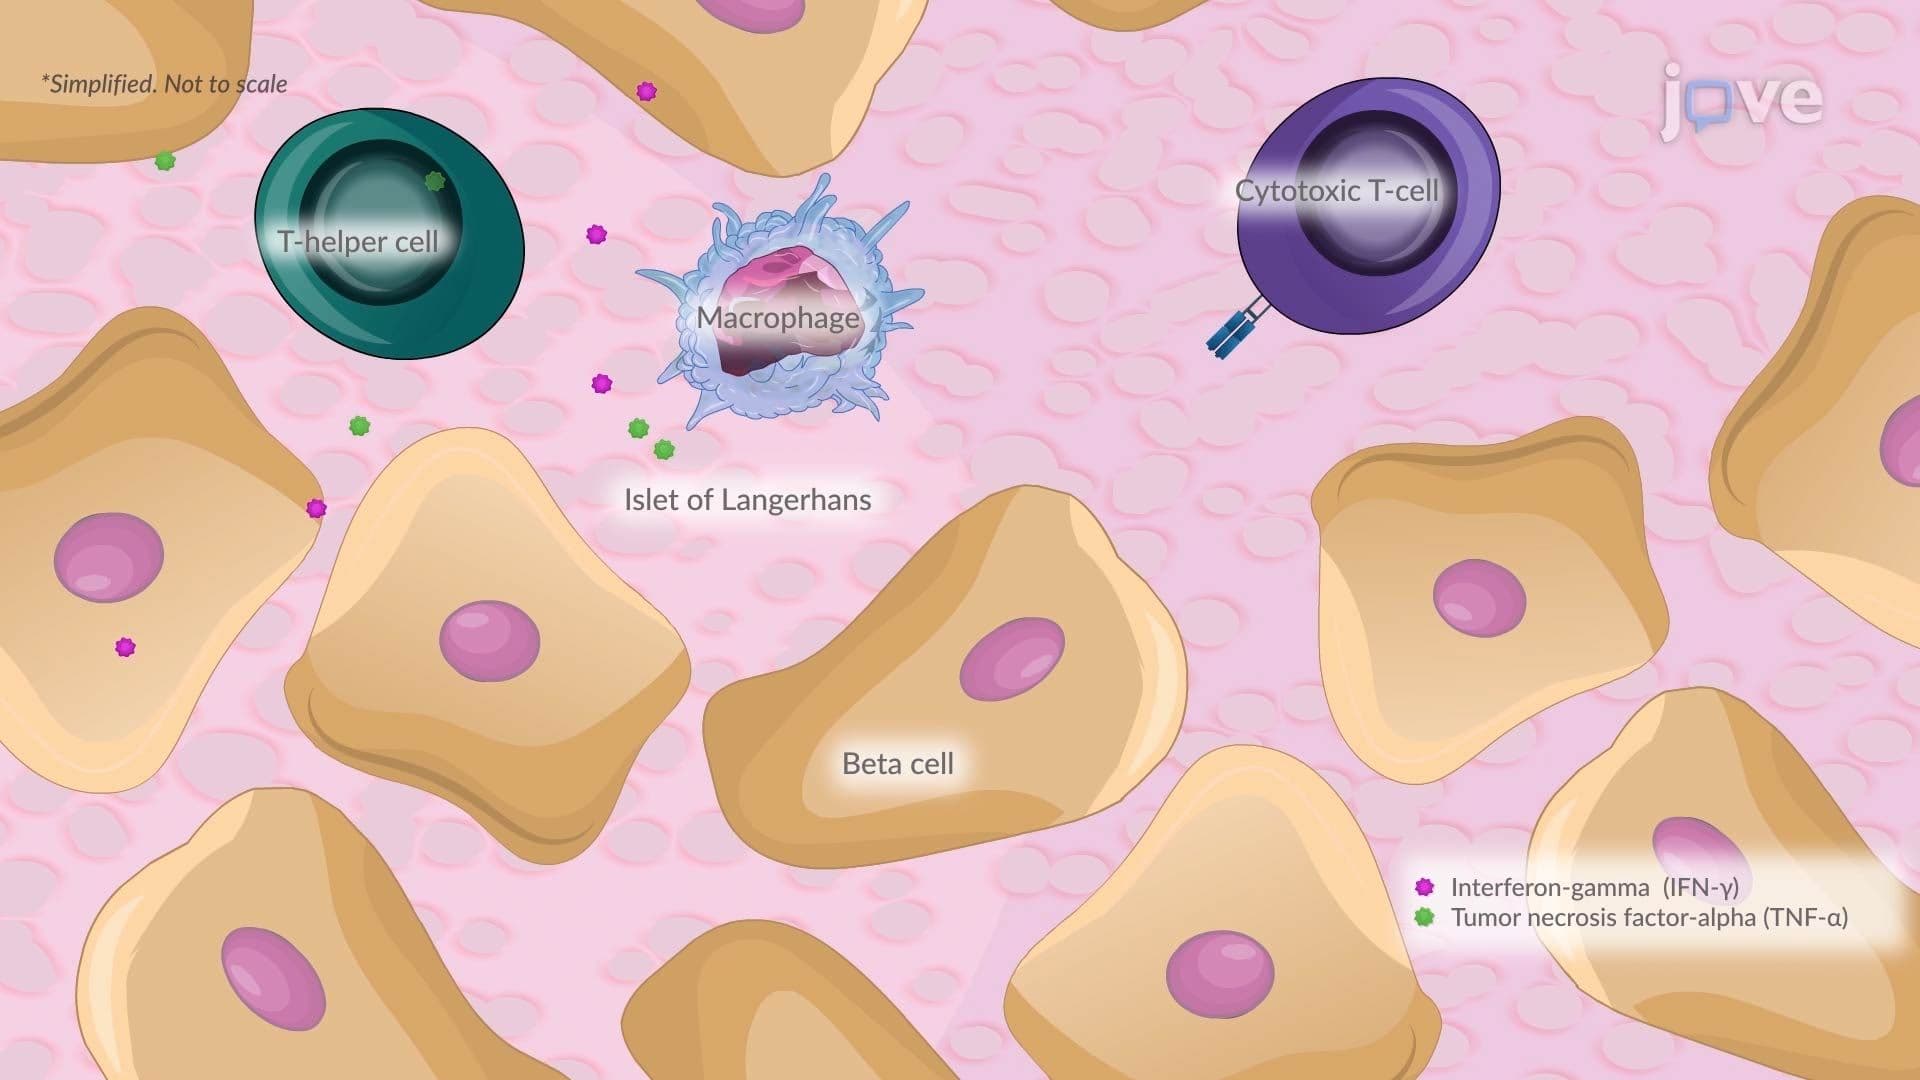
Type 1 diabetes mellitus arises from an immune-mediated destruction of pancreatic β-cells, resulting in an absolute deficiency of insulin. This process develops in genetically susceptible individuals when autoimmunity, environmental exposures, and immunologic dysregulation converge to trigger a targeted attack on the insulin-producing cells of the pancreas. The β-cells are located within the islets of Langerhans and are essential for regulating blood glucose by facilitating cellular uptake of...
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation01:21

Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation

Clinical manifestationsPeripheral Arterial Disease (PAD) manifests through a range of symptoms, from the characteristic intermittent claudication to atypical presentations and severe complications in advanced stages. Intermittent claudication, a hallmark symptom of PAD, presents as exercise-induced muscle pain that typically resolves within minutes of rest. This pain is reproducible and stems from inadequate blood flow, leading to the accumulation of lactic acid produced during anaerobic...
Peripheral Artery Disease IV: Nursing Management01:26

Peripheral Artery Disease IV: Nursing Management

The nursing management of a patient with peripheral artery disease (PAD) begins with a thorough assessment of the patient’s health history and clinical manifestations.AssessmentHealth History: Evaluate the patient’s history of hypertension, hyperlipidemia, family history of cardiovascular issues, and lifestyle factors such as dietary patterns, smoking, and physical activity.Physical Examination:Assess the affected extremity for decreased or absent peripheral pulses, temperature changes,...