Related Experiment Video
Updated: Sep 29, 2026

Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Experience with the use of an iron polymaltose (dextrin) complex given by single total dose infusion to stable
Roal van Zyl-Smit1, Janet A Halkett
1Department of Medicine, Renal Unit E13, Groote Schuur Hospital, University of Cape Town, Observatory 7935, South Africa. vzsmit@curie.uct.ac.za

Background:
Many studies of anaemia in patients on chronic haemodialysis have noted a high prevalence of iron deficiency despite oral iron supplementation. Our study examined the effect of intravenous iron given as bolus replacement. As the majority of these patients were not receiving concurrent recombinant human erythropoietin (rhEPO) it allowed an analysis of the safety and efficacy of intravenous iron as a single agent.
Methods:
All patients with a haemoglobin level of less than 10 g/dl and considered iron deficient by the finding of a percentage transferrin saturation of less than 20% were given intravenous iron in the form of iron polymaltose (dextrin) by total dose infusion (TDI). The dose was calculated from tables supplied by the manufacturers. Patients with serum ferritin levels in excess of 225 ng/ml were excluded.
Results:
In our unit, 62 out of 80 (77%) patients were considered iron deficient and received IV iron. Ten (10%) were considered to be in iron balance and 8 (10%) had biochemistry suggesting iron overload. None of the patients receiving iron experienced any adverse reactions. At three months a rise in haemoglobin level of at least 1 g/dl was noted in 53% of patients. The response was less in the remainder, but only 2 showed no response.
Conclusions:
Low levels of iron deficiency are often unrecognized in chronic haemodialysis patients on conventional therapy including oral iron supplementation. In such patients, the use of total dose infusion of iron polymaltose (dextrin) is a safe and effective method of raising haemoglobin levels. Substantial improvements may be achieved without the concurrent use of rhEPO.

Related Concept Videos
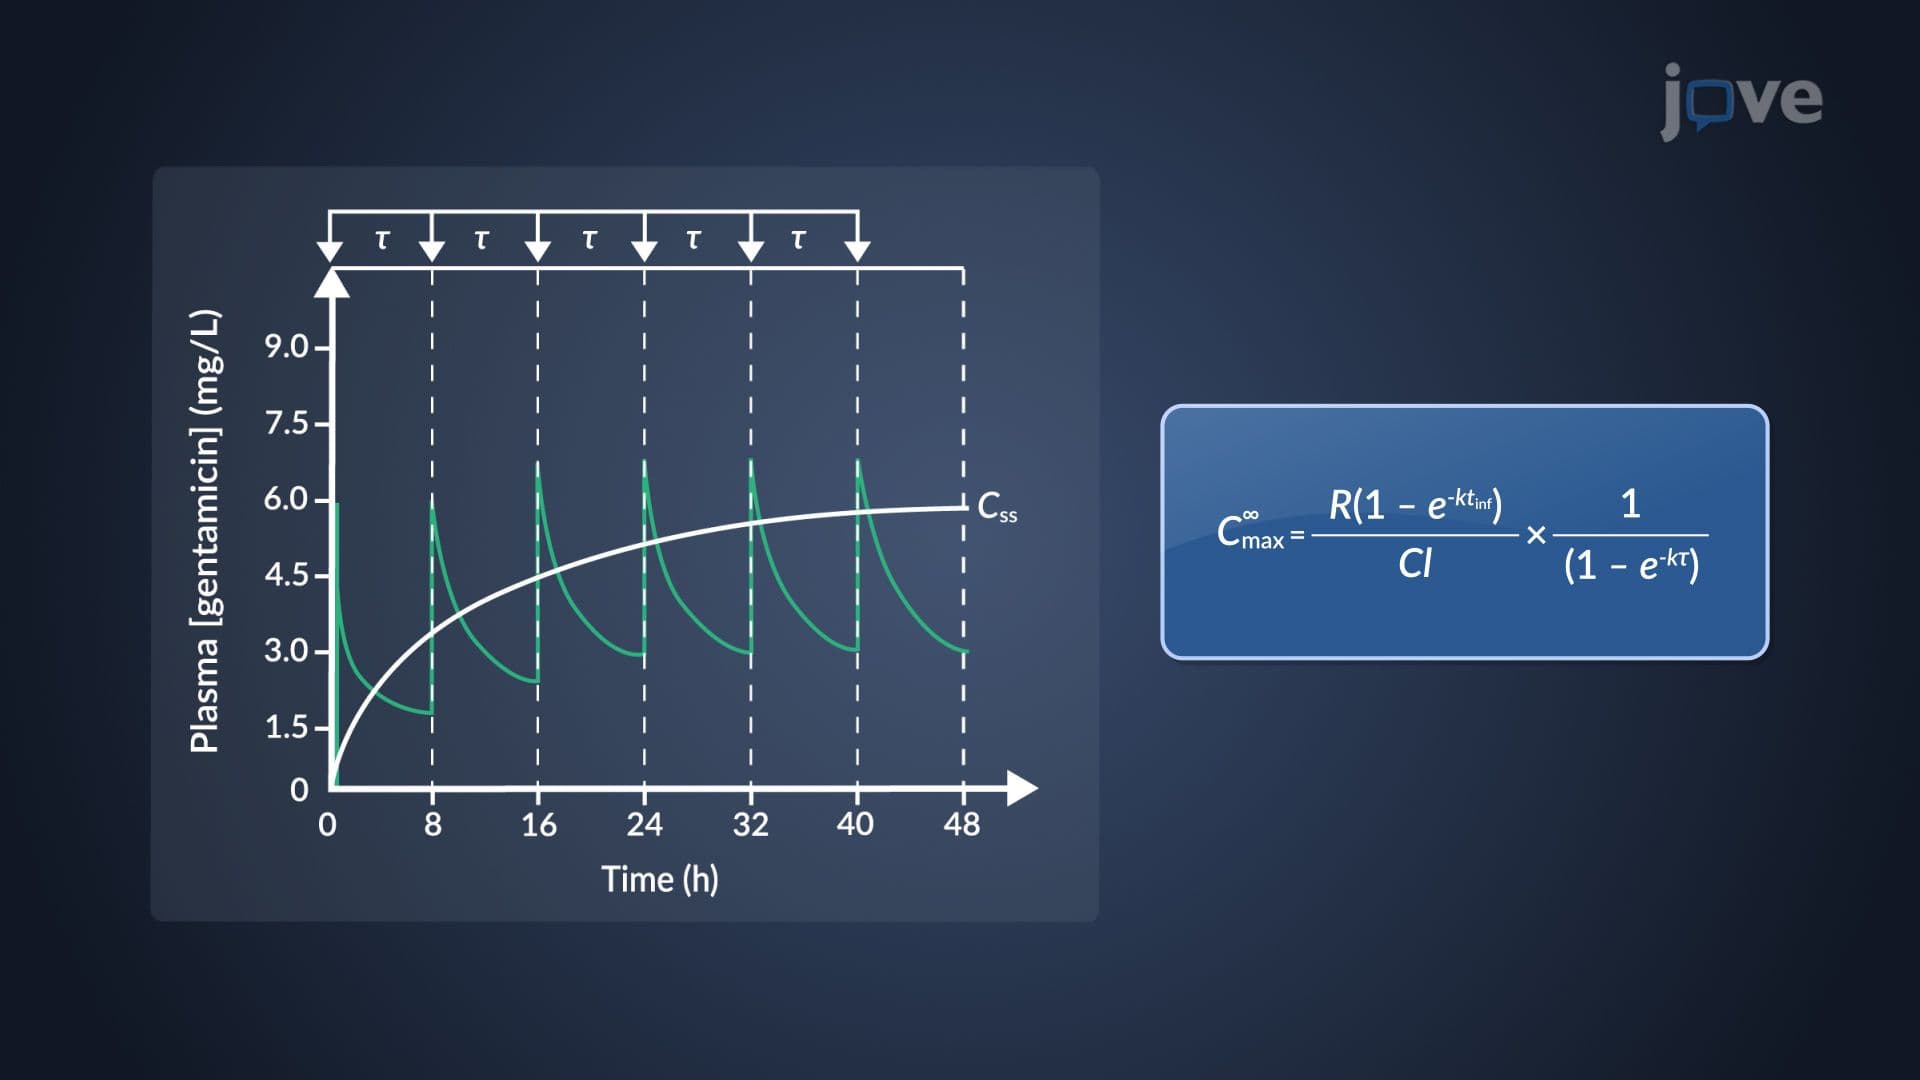 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:30
Peritoneal Dialysis I: Introduction and Procedure
 01:25
Peritoneal Dialysis II: Peritoneal Dialysis Systems and Complications
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:30
Continuous Renal Replacement Therapy
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...