Related Experiment Video
Updated: Jul 6, 2026
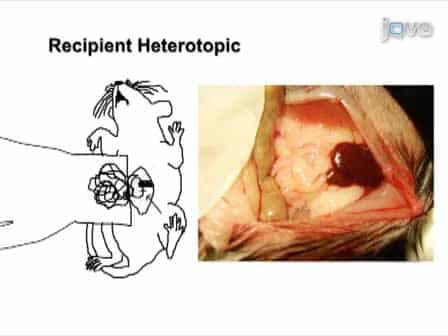
Heterotopic and Orthotopic Tracheal Transplantation in Mice used as Models to Study the Development of Obliterative Airway Disease
Published on: January 20, 2010
Differing pathways of lower airway colonization and infection according to mode of ventilation (endotracheal vs
Pradeep Morar1, Vivian Singh, Zvoru Makura
1Department of Otorhinolaryngology, Royal Liverpool Children's NHS Trust of Alder Hey, Liverpool, England. paddy@morarp.freeserve.co.uk

Objectives:
To determine whether the pathogenesis of lower airway colonization and infection was endogenous (via the oropharynx) or exogenous (via the endotracheal tube or tracheotomy) during the 2 modes of ventilation in the same subset of children requiring long-term ventilation.
Design:
Prospective, observational cohort study.
Setting:
A pediatric intensive care unit and a respiratory ward.
Patients:
Consecutive admissions between September 1, 1993, and August 30, 1998.
Measurements And Main Results:
Cultures were obtained simultaneously from the oropharynx and tracheobronchial tree on admission to the pediatric intensive care unit, at placement of the tracheotomy, and afterward twice weekly. Forty-five patients were studied. Lower airways were always sterile in 6 children, 39 children (87%) developed a total of 82 episodes of colonization, and 17 (38%) progressed to 25 episodes of infection. The number of infected children was halved once they had a tracheotomy (7 children [16%]). Of the 107 episodes of colonization and infection, 41 and 66 occurred during endotracheal ventilation and via a tracheotomy, respectively. Primary endogenous episodes of colonization and infection due to bacteria present in the admission flora in the pediatric intensive care unit were significantly more common with endotracheal ventilation than during ventilation via a tracheotomy (31/41 [76%] vs 36/66 [55%]; P =.03). Secondary endogenous and exogenous episodes of colonization and infection due to bacteria associated with the respiratory ward were significantly more frequent when ventilation was continued through a tracheotomy than during endotracheal ventilation (30/66 [45%] vs 10/41 [24%]; P =.02).
Conclusions:
Surveillance samples allow the distinction between primary endogenous ("imported" bacteria) from secondary endogenous and exogenous ("nosocomial" microorganisms) colonization and infection. This classification permits the development of preventive strategies to control both endogenous and exogenous pathways.


Related Concept Videos
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:29
Microbiota of the Respiratory Tract