Related Experiment Video
Updated: Aug 11, 2026
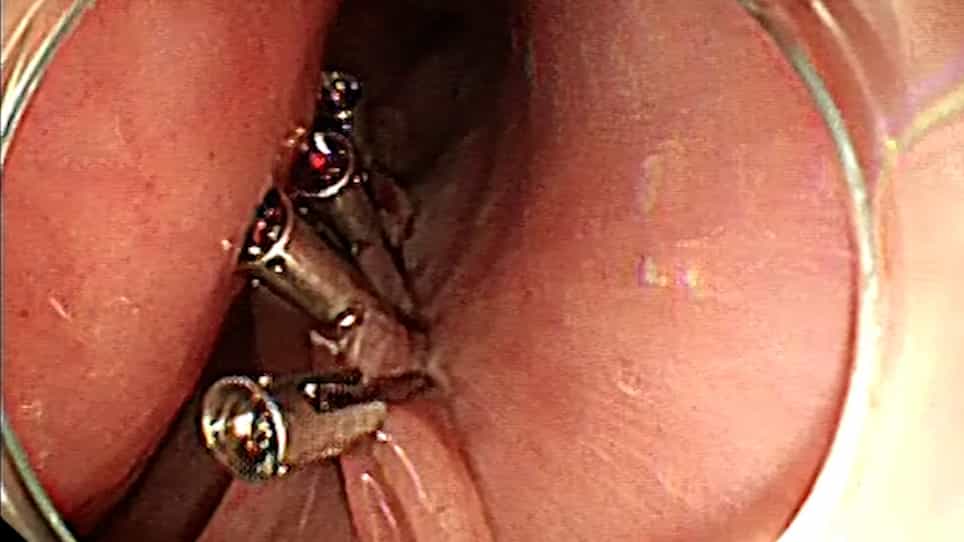

Use of the Scissor-Type Knife During the Peroral Endoscopy Myotomy Procedure for the Treatment of Achalasia
Published on: March 3, 2023
Long-term effects of myotomy and partial fundoplication for esophageal achalasia
L-Q Chen1, T Chughtai, L Sideris
1Department of Surgery, Centre Hospitalier de l'Université de Montréal, Quebec, Canada.

Abstract:
Controversy persists in the surgical approach to treat esophageal achalasia. This investigation reports the long-term effects of esophageal myotomy and partial fundoplication in treating this disorder. From 1984 to 1998, 32 patients with achalasia underwent myotomy and partial fundoplication (Belsey Mark IV) using a left thoracotomy. The median follow up is 7.2 years. Assessments include clinical evaluation, esophagogram, radionuclide transit, manometry, 24-h pH, and endoscopy. There is no complication and no mortality. Preoperative assessment was compared with that in 0-3, 3-7, and 7-16 postoperative years. Clinically, the prevalence of dysphagia was decreased from 100% to 6%, 12%, and 13%, respectively (P < 0.001). Heartburn remains unchanged (P > 0.25). On radiology, the prevalence of barium stasis was decreased from 97% to 44%, 48%, and 47%, respectively (P=0.001), whereas a pseudo-diverticulum was observed in two-thirds of patients after operation (P=0.001). Percent radionuclide stasis at 2 min was measured as 70%, 17%, 20%, and 20%, respectively (P=0.001). Manometrically, lower esophageal sphincter (LES) gradient was decreased from 29 to 10, 9, and 9 mmHg, respectively (P=0.001). LES relaxation was improved from 41% preoperatively to 100% postoperatively at each postoperative period (P < 0.001). An abnormal acid exposure was observed in four patients after the operation. Endoscopy documented mucosal damage in three patients (P > 0.25). In conclusion, on long-term follow up, myotomy and partial fundoplication for achalasia relieve obstructive symptoms and improve esophageal emptying, and reduce LES gradient and improve LES relaxation. Acid reflux is recorded in 13% of patients and esophageal mucosal damage is identified in 11% of the patient population. A longer myotomy not covered by the fundoplication results in pseudodiverticulum formation and increased esophageal retention.


Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:27
Esophageal Achalasia