Related Experiment Video
Updated: Sep 21, 2026
Standardized Hemorrhagic Shock Induction Guided by Cerebral Oximetry and Extended Hemodynamic Monitoring in Pigs
Published on: May 21, 2019
Lack of agreement between thermodilution and fick cardiac output in critically ill patients
Vinay K Dhingra1, John C Fenwick, Keith R Walley
1Division of Critical Care Medicine, Vancouver Hospital and Health Sciences Center, University of British Columbia, Vancouver, BC, Canada. vdhingra@vanhosp.bc.ca

Study Objective:
s: Individual comparison of cardiac output via intermittent thermodilution and Fick technique over a wide range of cardiac outputs.
Design:
Prospective clinical investigation.
Setting:
Multidisciplinary ICUs of two teaching hospitals in Vancouver, British Columbia.
Participants:
Eighteen critically ill patients who had pulmonary and systemic arterial catheters and in whom active support was being withdrawn.
Interventions:
Measurement of thermodilution cardiac output and calculation of Fick cardiac output while support was withdrawn. Active support was withdrawn in a three-step process: removal of vasopressors followed by decrease in fraction of inspired oxygen to 0.21, and finally removal of mechanical ventilation.
Measurements And Results:
Simultaneous Fick and thermodilution cardiac outputs were obtained over a wide range. Fick calculated cardiac outputs were obtained using the Fick equation with oxygen uptake (O(2)) being measured with indirect calorimetry. O(2) determinations were made using five measurements over 5 min, with the mean being used for subsequent analysis. Thermodilution cardiac outputs were determined by the mean of five measurements, with the first being discarded. Coefficient of variation was calculated for the O(2) and thermodilution cardiac outputs. One hundred thirty-six simultaneous cardiac outputs were obtained in 18 patients with a mean APACHE (acute physiology and chronic health evaluation) II score of 25.5. The range of cardiac outputs was 1.39 to 16.95 L/min. Linear regression analysis found a good correlation of the data sets, with an R of 0.85. Bias and precision calculations found a bias of - 0.17 L/min with the upper and lower limits of agreement being 2.96 L/min and - 3.30 L/min, respectively. In patients with high cardiac outputs (> 7 L/min), the bias was - 1.90 with the limits of agreement being 1.87 L/min and - 5.67 L/min. The coefficient of variation for O(2) was 4.6% and for thermodilution cardiac output was 7.75%.
Conclusions:
There was good consistency of each of the measurements with a low coefficient of variation. The bias for the whole group was small, but the limits of agreement extended into a clinically relevant area, resulting in a lack of agreement. In patients with high cardiac outputs, the Fick tended to consistently produce higher cardiac outputs compared to thermodilution, suggesting a systematic error.

Related Concept Videos
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:19
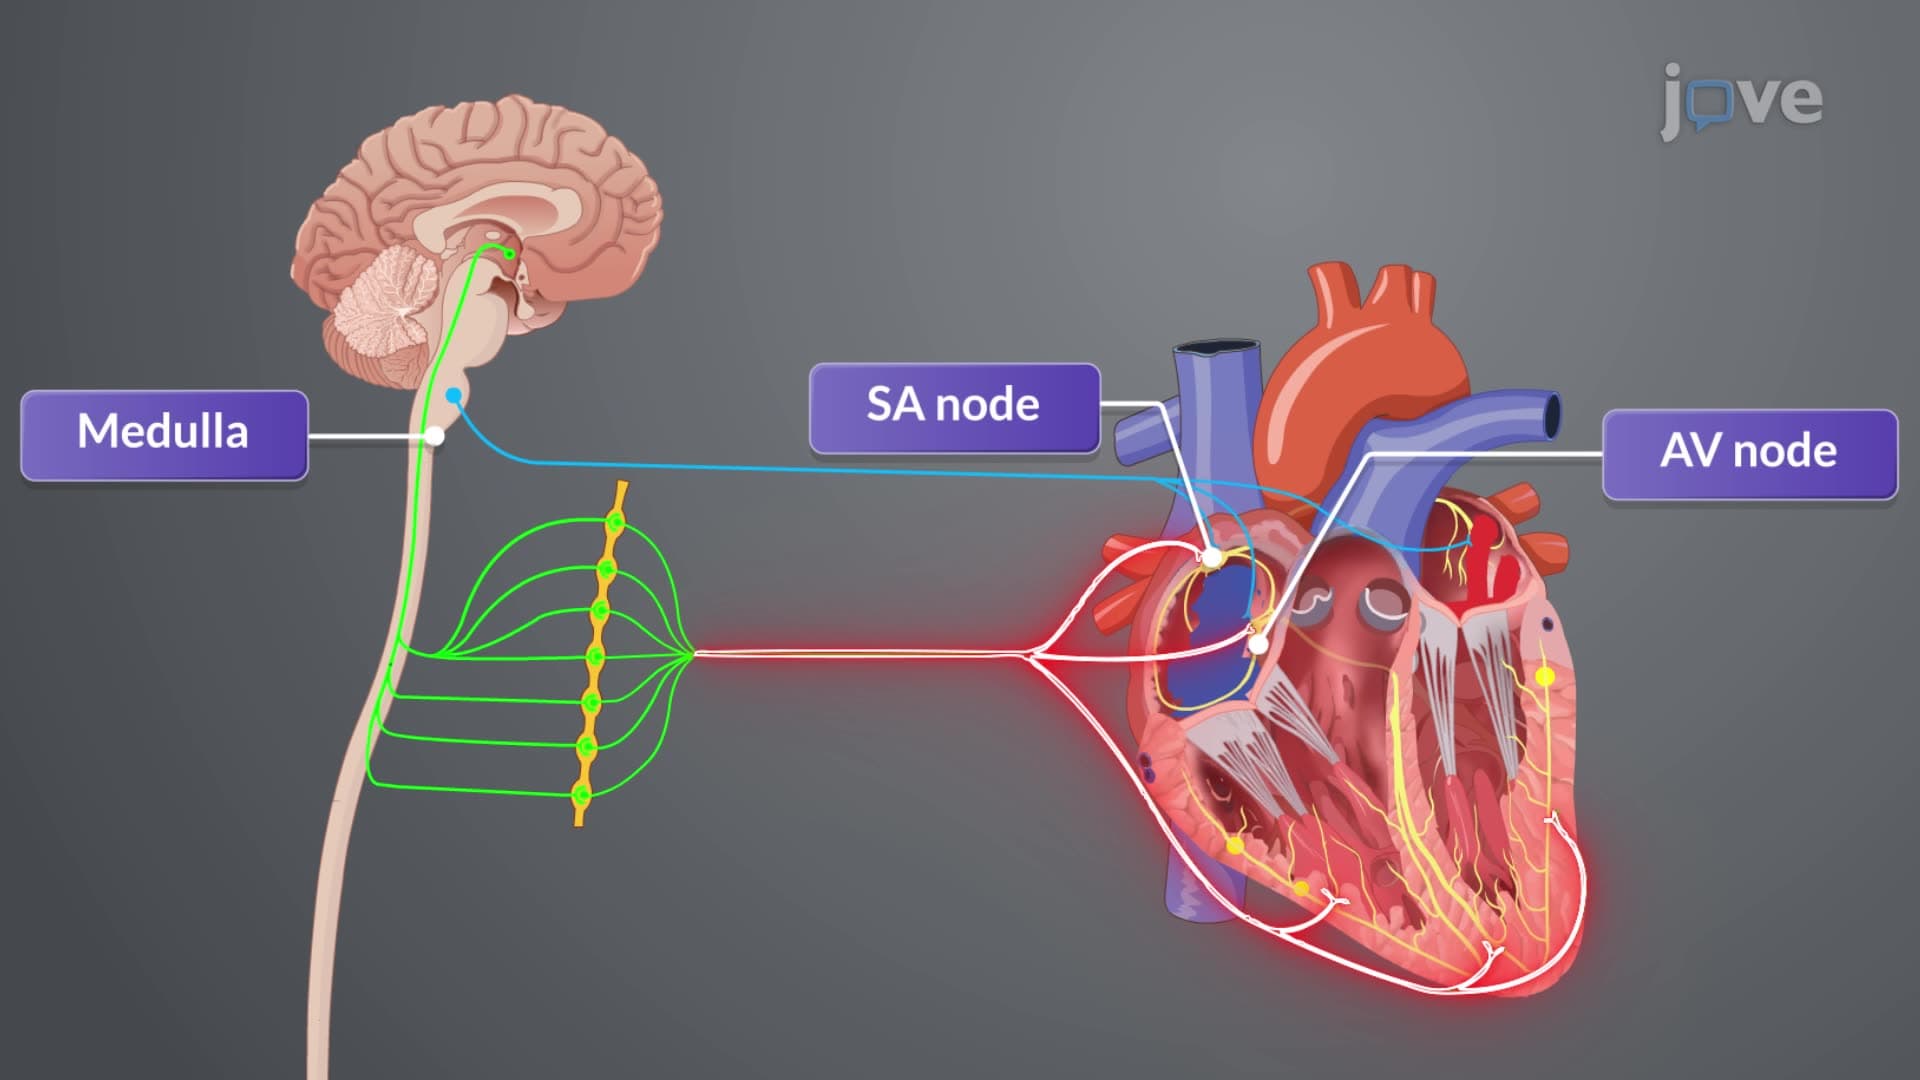
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...