Related Experiment Video
Updated: Sep 29, 2026

Rapid Screening of HIV Reverse Transcriptase and Integrase Inhibitors
Published on: April 9, 2014
Immunologic and virologic consequences of temporary antiretroviral treatment interruption in clinical practice
Ray Y Chen1, Andrew O Westfall, James L Raper
1Department of Medicine, University of Alabama at Birmingham, Birmingham, Alabama 35294, USA.

To determine the long-term immunologic and virologic effects of antiretroviral treatment interruptions, a retrospective analysis of an ongoing observational database was performed at a university HIV clinic. All patients who began highly active antiretroviral therapy (HAART) after January 1, 1996 and (1) were HAART experienced for >/=90 days, (2) had a treatment interruption (TI) for >/=30 days, (3) resumed HAART for >/=30 days, and (4) had CD4(+) cell counts performed pre- and post-TI were included. Main outcome measures included the following: Immunologic success was defined as a post-TI CD4(+) cell count >90% of the pre-TI CD4(+) cell count (post-TI/pre-TI, >90%). Virologic success was defined as a post-TI viral load (VL) less or equal to twice the pre-TI VL (post-TI/pre-TI,
To determine the long-term immunologic and virologic effects of antiretroviral treatment interruptions, a retrospective analysis of an ongoing observational database was performed at a university HIV clinic. All patients who began highly active antiretroviral therapy (HAART) after January 1, 1996 and (1) were HAART experienced for >/=90 days, (2) had a treatment interruption (TI) for >/=30 days, (3) resumed HAART for >/=30 days, and (4) had CD4(+) cell counts performed pre- and post-TI were included. Main outcome measures included the following: Immunologic success was defined as a post-TI CD4(+) cell count >90% of the pre-TI CD4(+) cell count (post-TI/pre-TI, >90%). Virologic success was defined as a post-TI viral load (VL) less or equal to twice the pre-TI VL (post-TI/pre-TI,
Related Concept Videos
 01:30
Inhibitors of Viral Protein Synthesis
 01:10
Retrovirus Life Cycles
 01:22
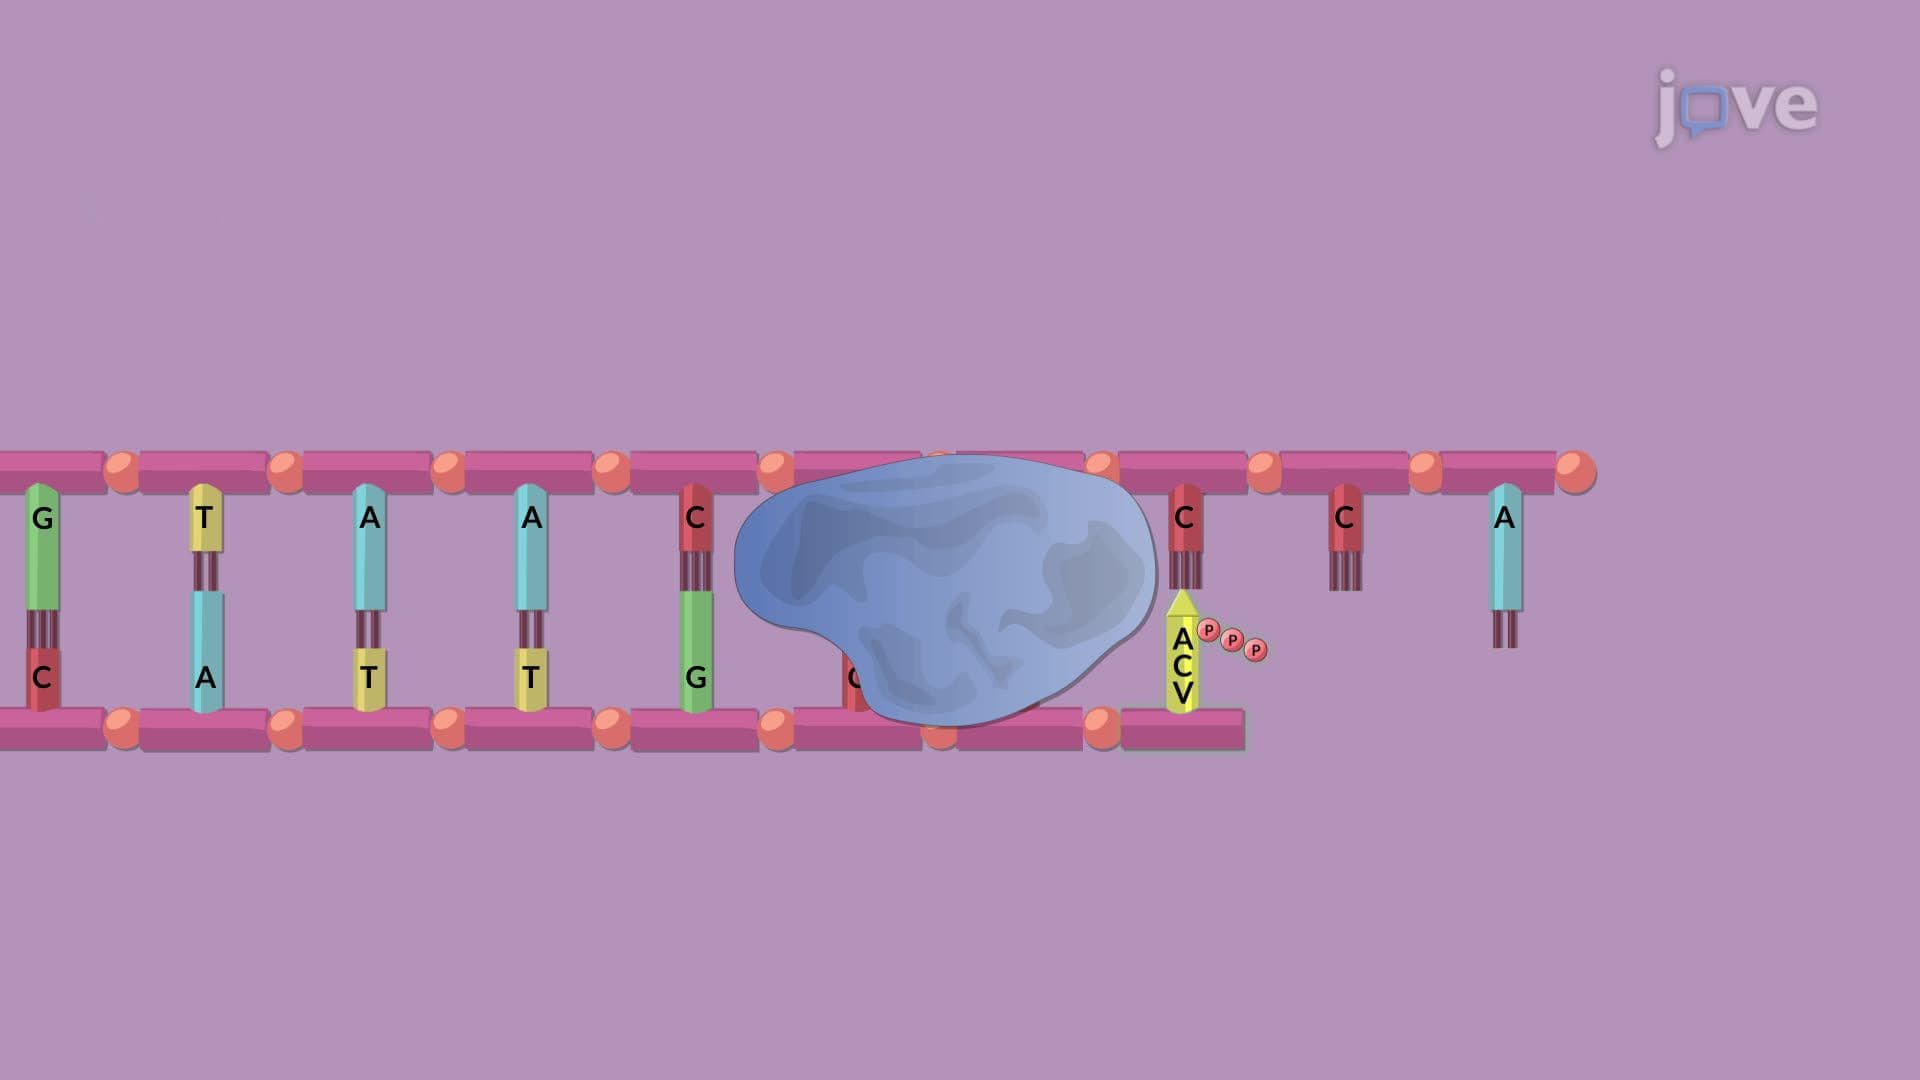
Antiviral Nucleoside Inhibitors
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency disorders...
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...