Related Experiment Video
Updated: Sep 29, 2026

A Multicenter MRI Protocol for the Evaluation and Quantification of Deep Vein Thrombosis
Published on: June 2, 2015
The incidence of venous thromboembolism in thrombophilic children: a prospective cohort study
Daniela Tormene1, Paolo Simioni, Paolo Prandoni
1Department of Medical and Surgical Sciences, 2nd Chair of Internal Medicine, University of Padua Medical School, Padua, Italy.

Insights
Children with inherited thrombophilia defects have a very low risk of venous thromboembolism (VTE). Standard VTE risk factors in adults do not increase this risk in children, suggesting screening is unwarranted.
Area of Science:
- Pediatric Hematology
- Thrombophilia Genetics
- Venous Thromboembolism (VTE) Research
Background:
- Inherited thrombophilias (e.g., Factor V Leiden, prothrombin gene mutation) are known VTE risk factors in adults.
- The role of these inherited defects in predisposing children to VTE remains unclear.
Purpose of the Study:
- To assess the incidence of spontaneous and risk period-related VTE in asymptomatic children (1-14 years) with inherited thrombophilic defects.
- To determine if common VTE triggers in adults elevate risk in pediatric carriers.
Main Methods:
- Prospective cohort study of 143 children from 63 families with a proband diagnosed with VTE and a documented thrombophilic abnormality.
- Children were categorized as carriers (n=81) or non-carriers (n=62) of inherited defects.
- Follow-up occurred over a mean of 5 years (range 1-8 years) to monitor VTE events.
Main Results:
- No spontaneous or risk period-related VTE events occurred in either carriers or non-carriers during 395 and 296 observation years, respectively.
- Key pediatric thrombosis circumstances (central venous lines, cancer, cardiovascular surgery) were not observed in the study cohort.
- The thrombotic risk in healthy children with a single inherited thrombophilic defect was found to be very low.
Conclusions:
- The study suggests that inherited thrombophilic defects pose a minimal VTE risk in otherwise healthy children.
- Common VTE triggering conditions in adults do not appear to significantly increase thrombotic risk in pediatric carriers.
- Routine screening for thrombophilia in asymptomatic children under 15 from families with inherited defects is likely unjustified.
Abstract:
Antithrombin and protein C and S defects, factor V Leiden mutation, and G20210A prothrombin gene mutation are well-recognized risk factors for venous thromboembolism (VTE) in adults, especially during circumstantial situations such as trauma, immobilization, surgery, or oral contraceptive treatment. The relevance of these defects in predisposing children to VTE is still undefined. In a prospective cohort study we assessed the incidence of spontaneous and risk period-related VTE in asymptomatic children (aged 1-14 years), who were family members of a proband with an objectively diagnosed venous thromboembolic event and a documented single thrombophilic abnormality. We enrolled 143 children from 63 families. Of them, 81 (56.6%) were carriers of an inherited defect, whereas the remaining 62 were free from known genetic or acquired causes of thrombophilia. The mean observation period was 5 years (range, 1-8 years) in each group. Thirty-one risk periods occurred in the carriers group and 20 in noncarriers. Neither spontaneous nor risk period-related VTE occurred in either group during 395 and 296 observation years, respectively. However, circumstances where most of the pediatric thromboses occur (insertion of central venous lines, cancer, and cardiovascular surgery) were not encountered. In conclusion, the thrombotic risk in otherwise healthy children with a single identified thrombophilic defect appears to be very low. Common triggering conditions for VTE in thrombophilic adults do not seem to increase the thrombotic risk in children carrying the same inherited defect. Accordingly, screening for thrombophilia in otherwise healthy children younger than 15 years who belong to families with inherited defects predisposing to thrombosis seems unjustified.
Related Concept Videos
 01:30
Venous Thrombosis I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:30
Venous Thrombosis IV: Nursing Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:19
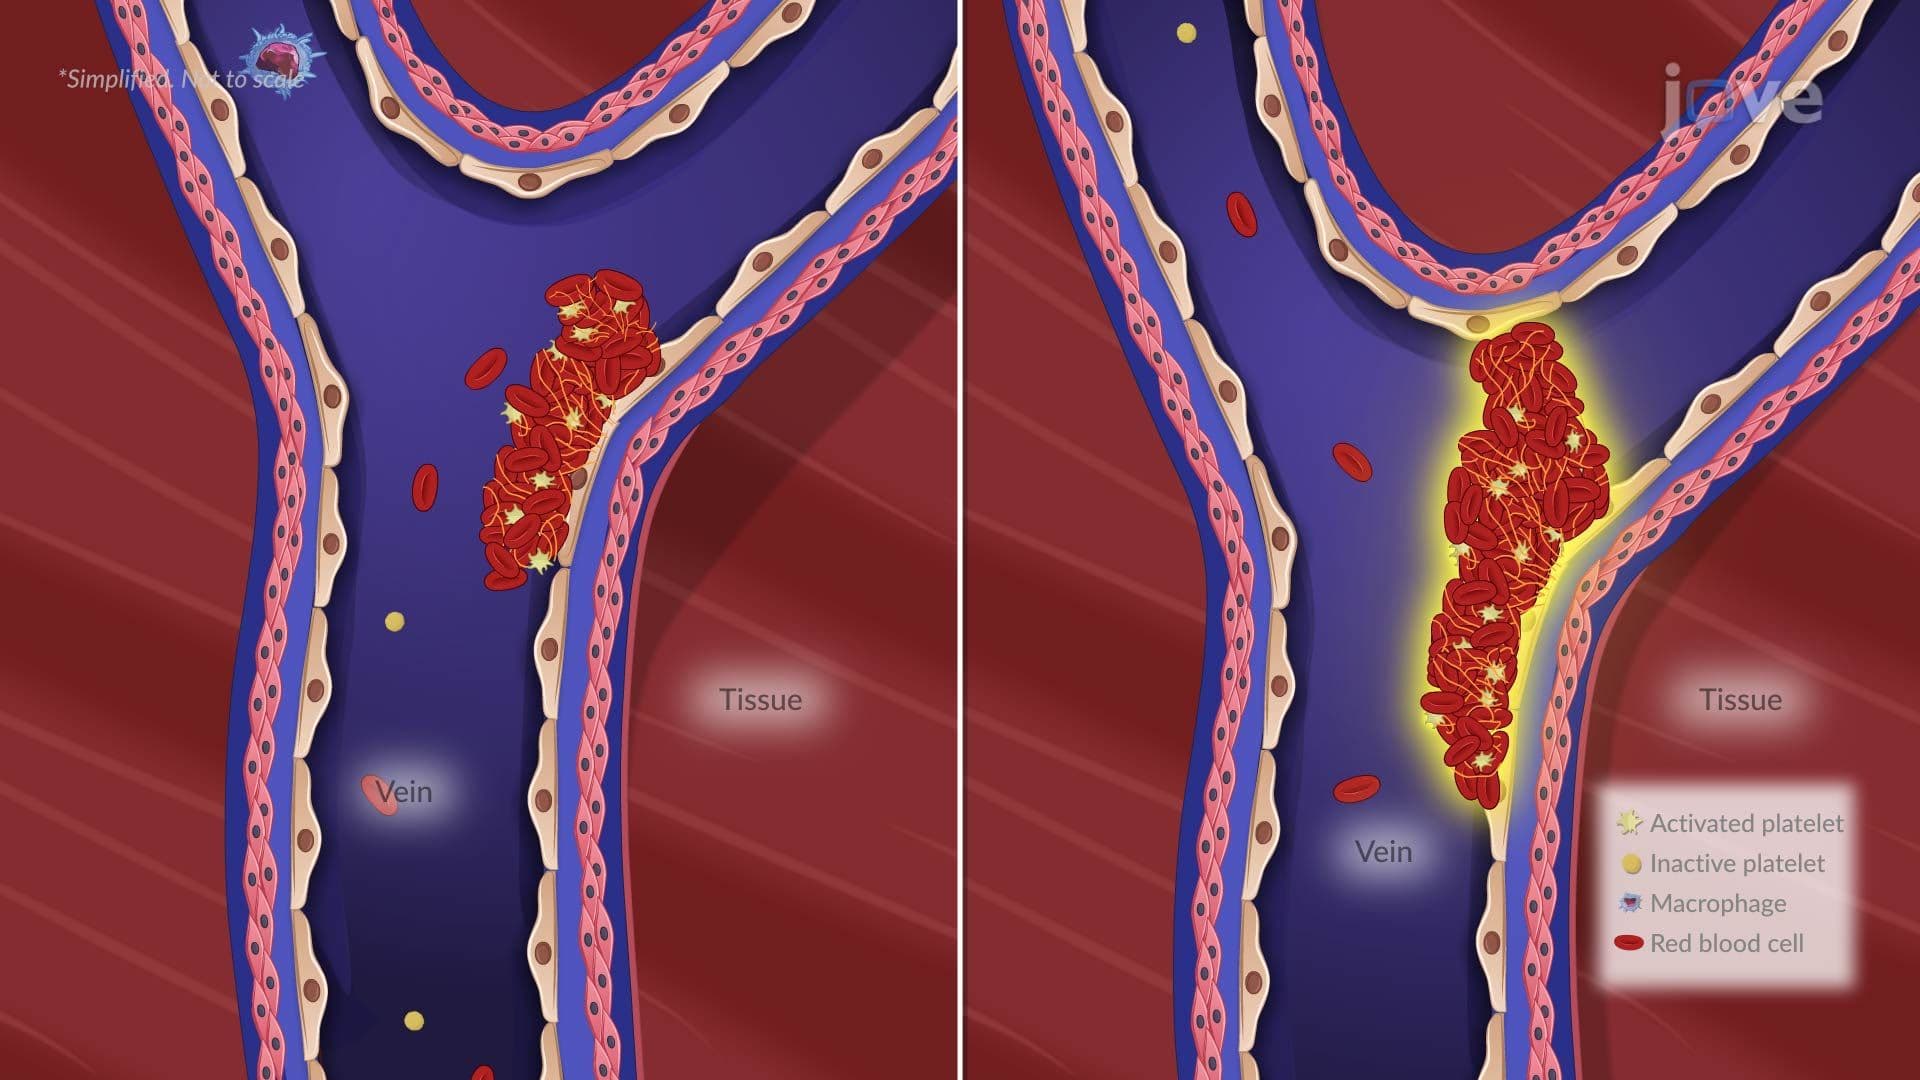
Pulmonary Embolism I: Introduction