Hypopituitarism following cerebral oedema with diabetic ketoacidosis

K A Dunlop1, D Woodman, D J Carson

  • 1Royal Belfast Hospital for Sick Children, Northern Ireland, UK.

Related Concept Videos

Hypoglycemia and Glucagon01:15

Hypoglycemia and Glucagon

Without prolonged fasting, healthy individuals maintain blood glucose levels above 3.5 mM due to a well-adapted neuroendocrine counterregulatory system that effectively prevents acute hypoglycemia, a potentially life-threatening condition. The primary clinical scenarios for hypoglycemia encompass diabetes treatment, inappropriate production of endogenous insulin or insulin-like substances by tumors, and the use of glucose-lowering agents in non-diabetic individuals. Notably, hypoglycemia in the...
Diabetes Insipidus II: Pathophysiology01:22

Diabetes Insipidus II: Pathophysiology

Normally, water balance is maintained through three interconnected mechanisms: the hypothalamic thirst center, the synthesis and release of antidiuretic hormone (ADH, or vasopressin), and the kidneys' responsiveness to this hormone. ADH is synthesized in the hypothalamus, released from the posterior pituitary, and acts on the distal nephron, allowing water reabsorption and concentrated urine production.Diabetes Insipidus and Its TypesIn diabetes insipidus (DI), this regulatory system is...
Cushing Syndrome II: Pathophysiology01:19

Cushing Syndrome II: Pathophysiology

Cortisol production is normally governed by the hypothalamic–pituitary–adrenal (HPA) axis, which maintains hormonal balance through tightly regulated feedback mechanisms. Disruption of this regulatory system is central to the development of Cushing syndrome, whether the excess cortisol originates from external medications or internal pathology. Persistent cortisol elevation alters metabolism, immune function, and endocrine signaling, producing the characteristic clinical features of the...
Type I Diabetes III: Clinical Manifestations01:19

Type I Diabetes III: Clinical Manifestations

Type 1 diabetes mellitus typically presents with rapid-onset symptoms due to the body’s inability to utilize glucose in the absence of insulin. Since insulin is required for glucose uptake into cells, its deficiency leads to hyperglycemia and cellular energy deprivation, resulting in characteristic clinical features.Polyuria and PolydipsiaOne of the earliest, most prominent symptoms is polyuria (excessive urination). When blood glucose concentrations rise above the renal threshold, the kidneys...
Diabetic Ketoacidosis l: Introduction01:25

Diabetic Ketoacidosis l: Introduction
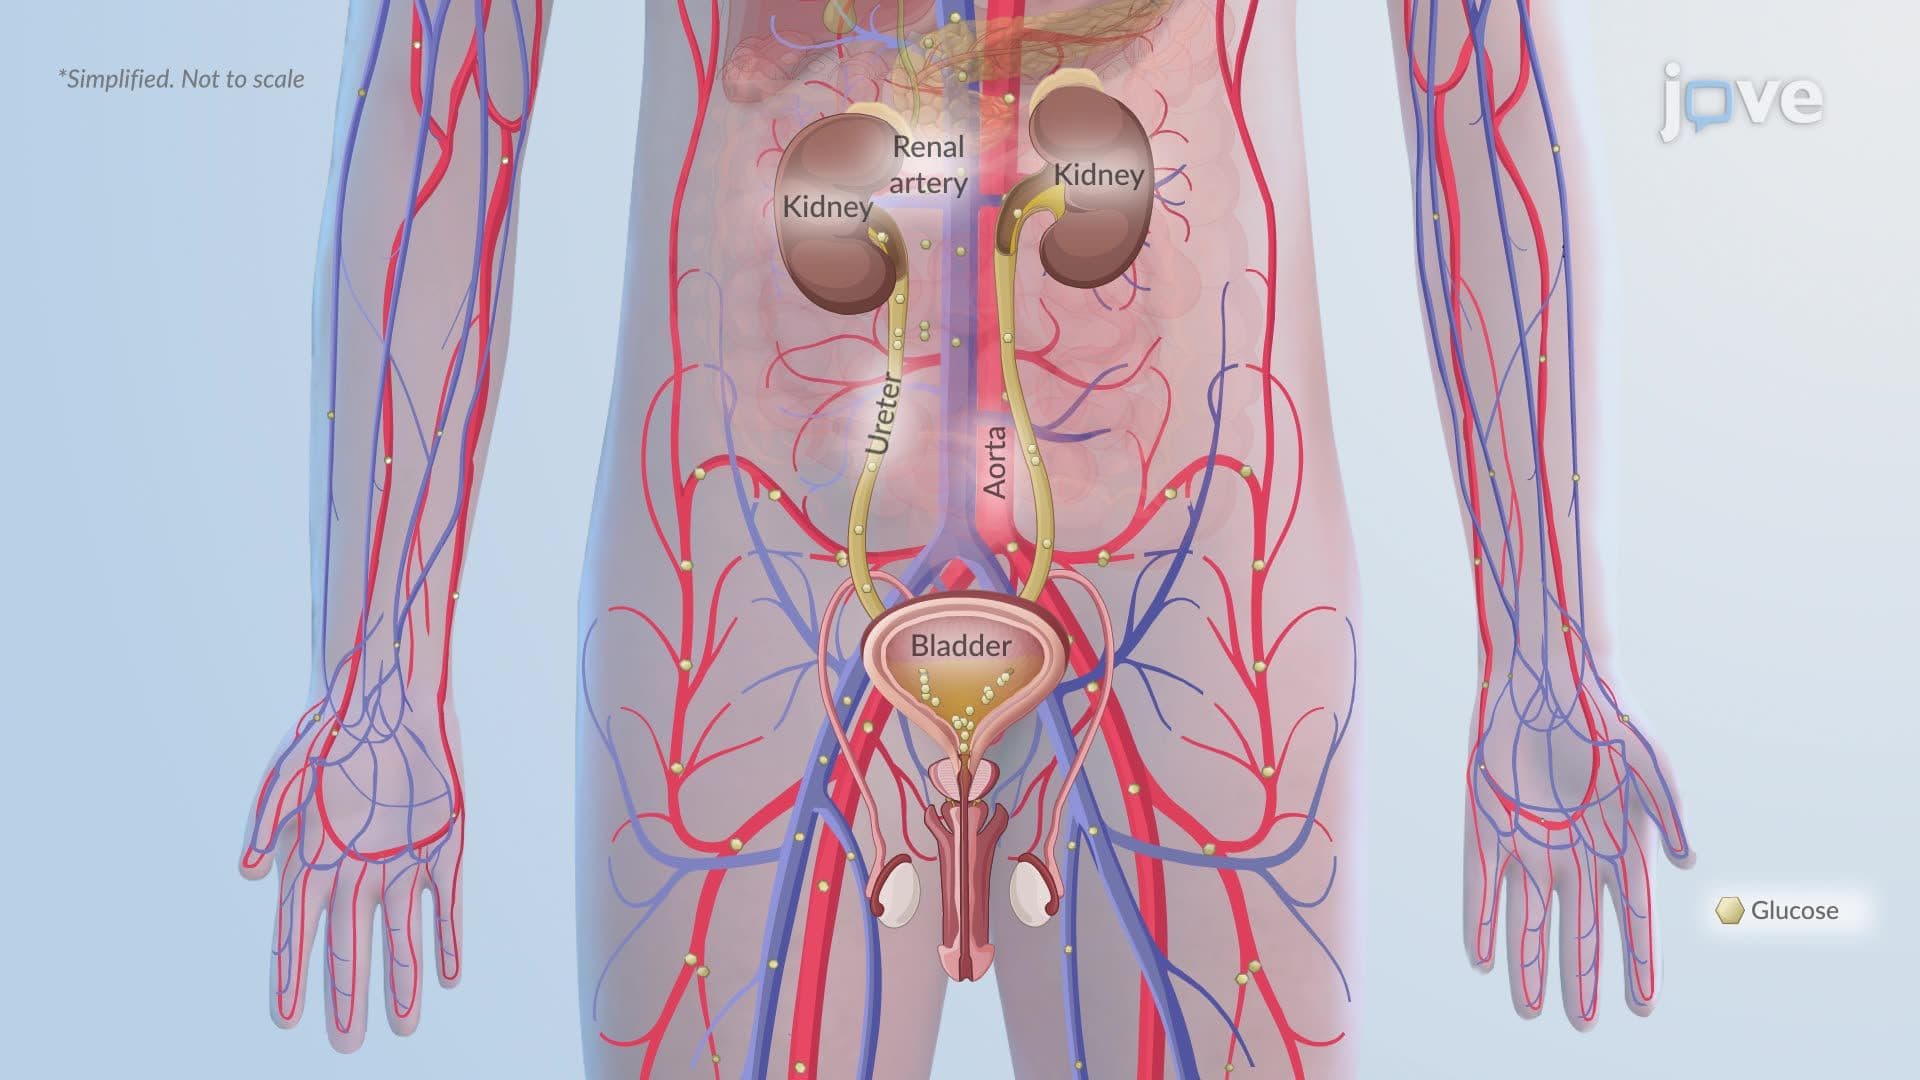
DefinitionDiabetic ketoacidosis (DKA) is an acute, life-threatening complication of diabetes mellitus, characterized by a triad of hyperglycemia (blood glucose >250 mg/dL), ketonemia or ketonuria, and metabolic acidosis (arterial pH <7.30 and serum bicarbonate <18 mEq/L). It results from insulin deficiency combined with elevated levels of counterregulatory hormones—glucagon, catecholamines, cortisol, and growth hormone—leading to increased lipolysis, hepatic ketone production, and...
Diabetic Ketoacidosis ll: Pathophysiology01:22

Diabetic Ketoacidosis ll: Pathophysiology

Diabetic ketoacidosis (DKA) is a metabolic emergency characterized by hyperglycemia, ketonemia, and metabolic acidosis. It results from severe insulin deficiency and an excess of counterregulatory hormones, leading to uncontrolled lipolysis, ketogenesis, and widespread electrolyte and fluid disturbances.Pathophysiology The central event in DKA is a profound loss of insulin action. Without insulin, glucose uptake in insulin-dependent tissues is impaired, while hepatic glucose production...