Related Experiment Video
Updated: Jul 30, 2026


Echocardiographic Evaluation of Atrial Communications before Transcatheter Closure
Published on: February 8, 2022
Clinical and electrophysiologic characteristics of left septal atrial tachycardia
Nassir F Marrouche1, Arne SippensGroenewegen, Yanfei Yang
1Section of Cardiac Electrophysiology, Department of Cardiology, University of California, San Francisco, California 94143, USA.

Objectives:
It was the purpose of this study to define the electrophysiologic (EP) identity of left septal atrial tachycardia (AT).
Background:
The clinical and EP characteristics of this particular type of arrhythmia have not been fully described.
Methods:
A total of 120 patients with AT underwent invasive EP evaluation. Five patients (two men and three women; mean age 49 +/- 15 years) with left septal AT were identified. Mapping of the right and left atrium was performed using conventional electrode catheters (five patients) and a three-dimensional electroanatomic mapping system (three patients) followed by radiofrequency (RF) ablation at the earliest site of local endocardial activation.
Results:
Five tachycardias with a mean cycle length of 320 +/- 94 ms were mapped, and the earliest endocardial electrogram occurred 22 +/- 10 ms before the onset of the surface P-wave. Three left septal ATs were found to be originating from the left inferoposterior atrial septum and two from the left midseptum. During tachycardia, positive (three patients), biphasic negative-positive deflection (one patient), or isoelectric (one patient) P waves were recorded in lead V(1). The inferior leads demonstrated a positive or biphasic P-wave morphology in four of five patients (80%). Four patients were given both adenosine and verapamil during AT. In three of four patients, verapamil successfully terminated AT after adenosine had failed. Adenosine successfully terminated AT in one of four patients. Successful RF ablation was performed in all patients (mean 2.2 +/- 1.7 RF applications) without affecting atrioventricular conduction properties. No recurrence of AT was observed after a mean follow-up of 14 +/- 8 months.
Conclusion:
Left septal AT ablation is safe and effective. There was no consistent P-wave morphology associated with this particular type of AT. This arrhythmia appears to be resistant to adenosine and moderately responsive to calcium antagonists.


Related Concept Videos
 01:16
ECG Interpretation of Arrhythmias I: Sinus Arrhythmias
Types of Arrhythmias
Sinus Node Arrhythmias
Sinus Bradycardia: Originating from the sinoatrial (SA) node, sinus bradycardia involves slower impulses, resulting in a heart rate of less than 60 beats per minute (bpm). Causes include sleep, vagal stimulation, beta-blockers, hypothyroidism, and...
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:28
Dysrhythmias II: Classification of Tachyarrhythmias
 01:29
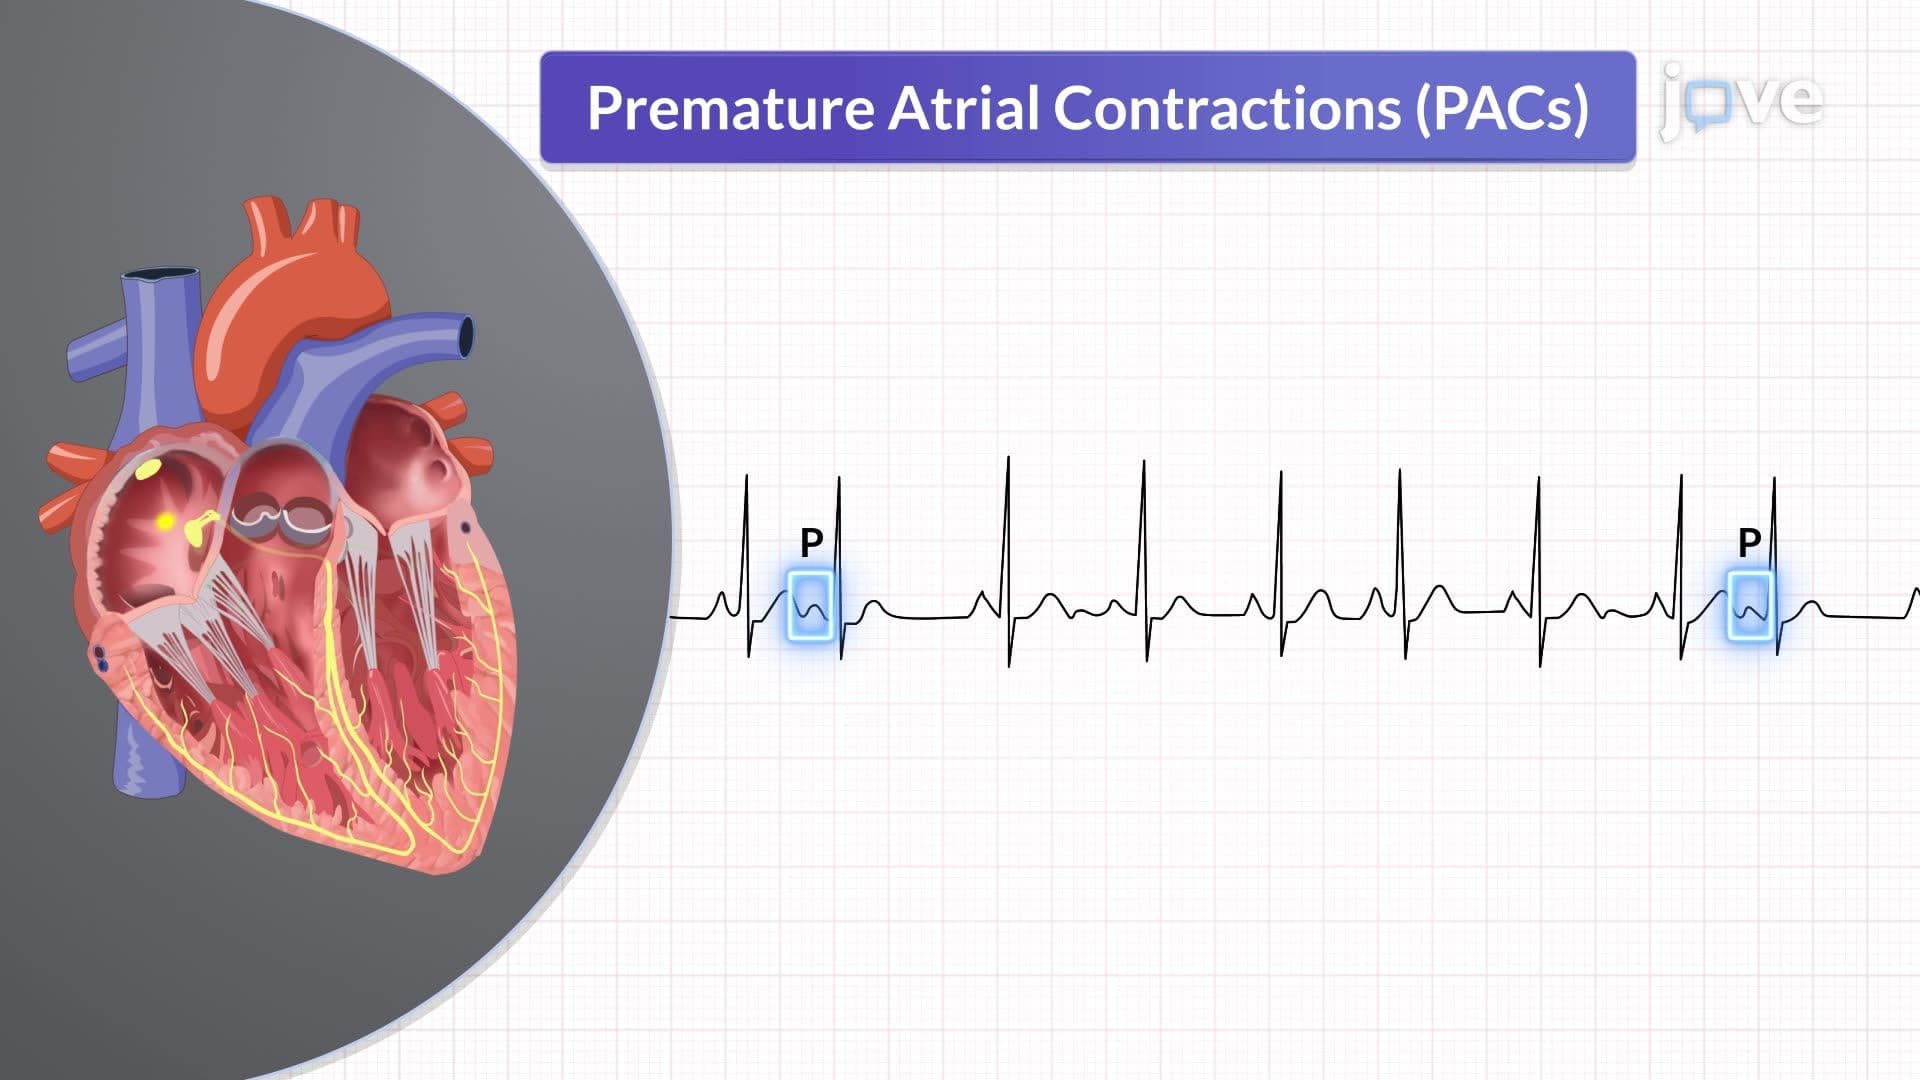
Dysrhythmias III: Characteristics of Dysrhythmias
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias