Related Experiment Video
Updated: Sep 29, 2026


Gastric Mucosa Quantitative Polymerase Chain Reaction Analysis for Detecting Helicobacter pylori and Antibiotic Resistance
Published on: March 7, 2025
Prevalence of resistant Helicobacter pylori isolates in Bulgarian children
Lyudmila Boyanova, Radka Koumanova1, Galina Gergova
1Department of Microbiology, Medical University of Sofia, *Department of Gastroenterology, University Paediatric Hospital, Sofia, †Executive Drug Agency, Sofia, ‡Department of Gastroenterology, University Hospital ''St. Ivan Rilski'', Sofia and §Second Surgery Department of Alexander Hospital, Sofia, Bulgaria.

Insights
Helicobacter pylori resistance to common antibiotics like metronidazole and clarithromycin was low in Bulgarian children. However, resistance to other agents and multi-drug resistance were observed, potentially linked to antimicrobial consumption.
Area of Science:
- Medical Microbiology
- Infectious Diseases
- Antimicrobial Resistance
Background:
- Helicobacter pylori (H. pylori) infection is a significant global health concern, particularly in pediatric populations.
- Understanding antimicrobial resistance patterns is crucial for effective H. pylori eradication therapies.
Purpose of the Study:
- To determine the primary and combined antimicrobial resistance of H. pylori isolates from Bulgarian children.
- To assess resistance to metronidazole, clarithromycin, azithromycin, clindamycin, amoxicillin, tetracycline, and ciprofloxacin.
Main Methods:
- Investigated pre-treatment H. pylori isolates from 115 pediatric patients (2000-2001).
- Utilized the limited agar dilution method and E-test to determine resistance.
- Defined specific cut-off concentrations for resistance to seven antimicrobial agents.
Main Results:
- Low primary resistance rates were observed for metronidazole (15.8%), clarithromycin (12.4%), and azithromycin (14.6%).
- Amoxicillin showed 0% resistance, while clindamycin resistance was 20.0%.
- Prevalence of macrolide resistance was 21.9% for azithromycin and 15.9% for clarithromycin. Multi-drug resistance was detected in one strain.
Conclusions:
- H. pylori resistance to metronidazole and clarithromycin was relatively low in Bulgarian children.
- Resistance to other tested drugs, including macrolides and fluoroquinolones, was present.
- Antimicrobial consumption may influence resistance patterns; further monitoring is recommended.
Abstract:
The aim of this study was to assess the primary and combined resistances of Helicobacter pylori isolates obtained from paediatric patients in 2000-2001 to seven antimicrobial agents. Resistance rates of pre-treatment isolates from 115 children were investigated by the limited agar dilution method alone and by the E-test. The cut-off concentrations for resistance were: metronidazole >8 mg/L, clarithromycin and azithromycin >1 mg/L, clindamycin >4 mg/L, amoxicillin >0.5 mg/L, tetracycline >4 mg/L and ciprofloxacin >1 mg/L. Primary resistance rates were: metronidazole 15.8%, clarithromycin 12.4%, azithromycin 14.6%, clindamycin 20.0%, amoxicillin 0%, metronidazole + clarithromycin 4.5%, ciprofloxacin 6.0%, metronidazole + clarithromycin + ciprofloxacin 1.2%, tetracycline 3.1% and metronidazole + ciprofloxacin 1.2%. There were no significant age (1-9 years versus 10-18 years) or gender differences. Prevalence of both macrolide-resistant and intermediately susceptible strains was 21.9% for azithromycin and 15.9% for clarithromycin. Of 18 metronidazole-resistant isolates, 77.8% exhibited a metronidazole MIC > or = 32 mg/L. H. pylori resistance rates to metronidazole, clarithromycin and both agents were relatively low in Bulgarian children. However, resistance was found to all drugs tested except for amoxicillin. The consumption of newer macrolides and tetracyclines could be related to the prevalence of resistance to the corresponding agents. There were no significant differences in primary resistance rates of H. pylori to antimicrobial agents between children and adults except for metronidazole. Multi-drug resistance to newer macrolides, metronidazole and ciprofloxacin in association with a slightly elevated amoxicillin MIC (0.38 mg/L) was detected in one strain.
More Related Videos
 04:56
Detection of Helicobacter pylori Infection and Antibiotic Resistance via Stool Quantitative Polymerase Chain Reaction Analysis
Published on: May 16, 2025
 06:40
Quantitative Polymerase Chain Reaction (qPCR)-Based Rapid Diagnosis of Helicobacter pylori Infection and Antibiotic Resistance
Published on: July 28, 2023
Related Concept Videos
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy
 01:27
Peptic Ulcer
 01:26
Gastritis II: Pathophysiology
 01:27
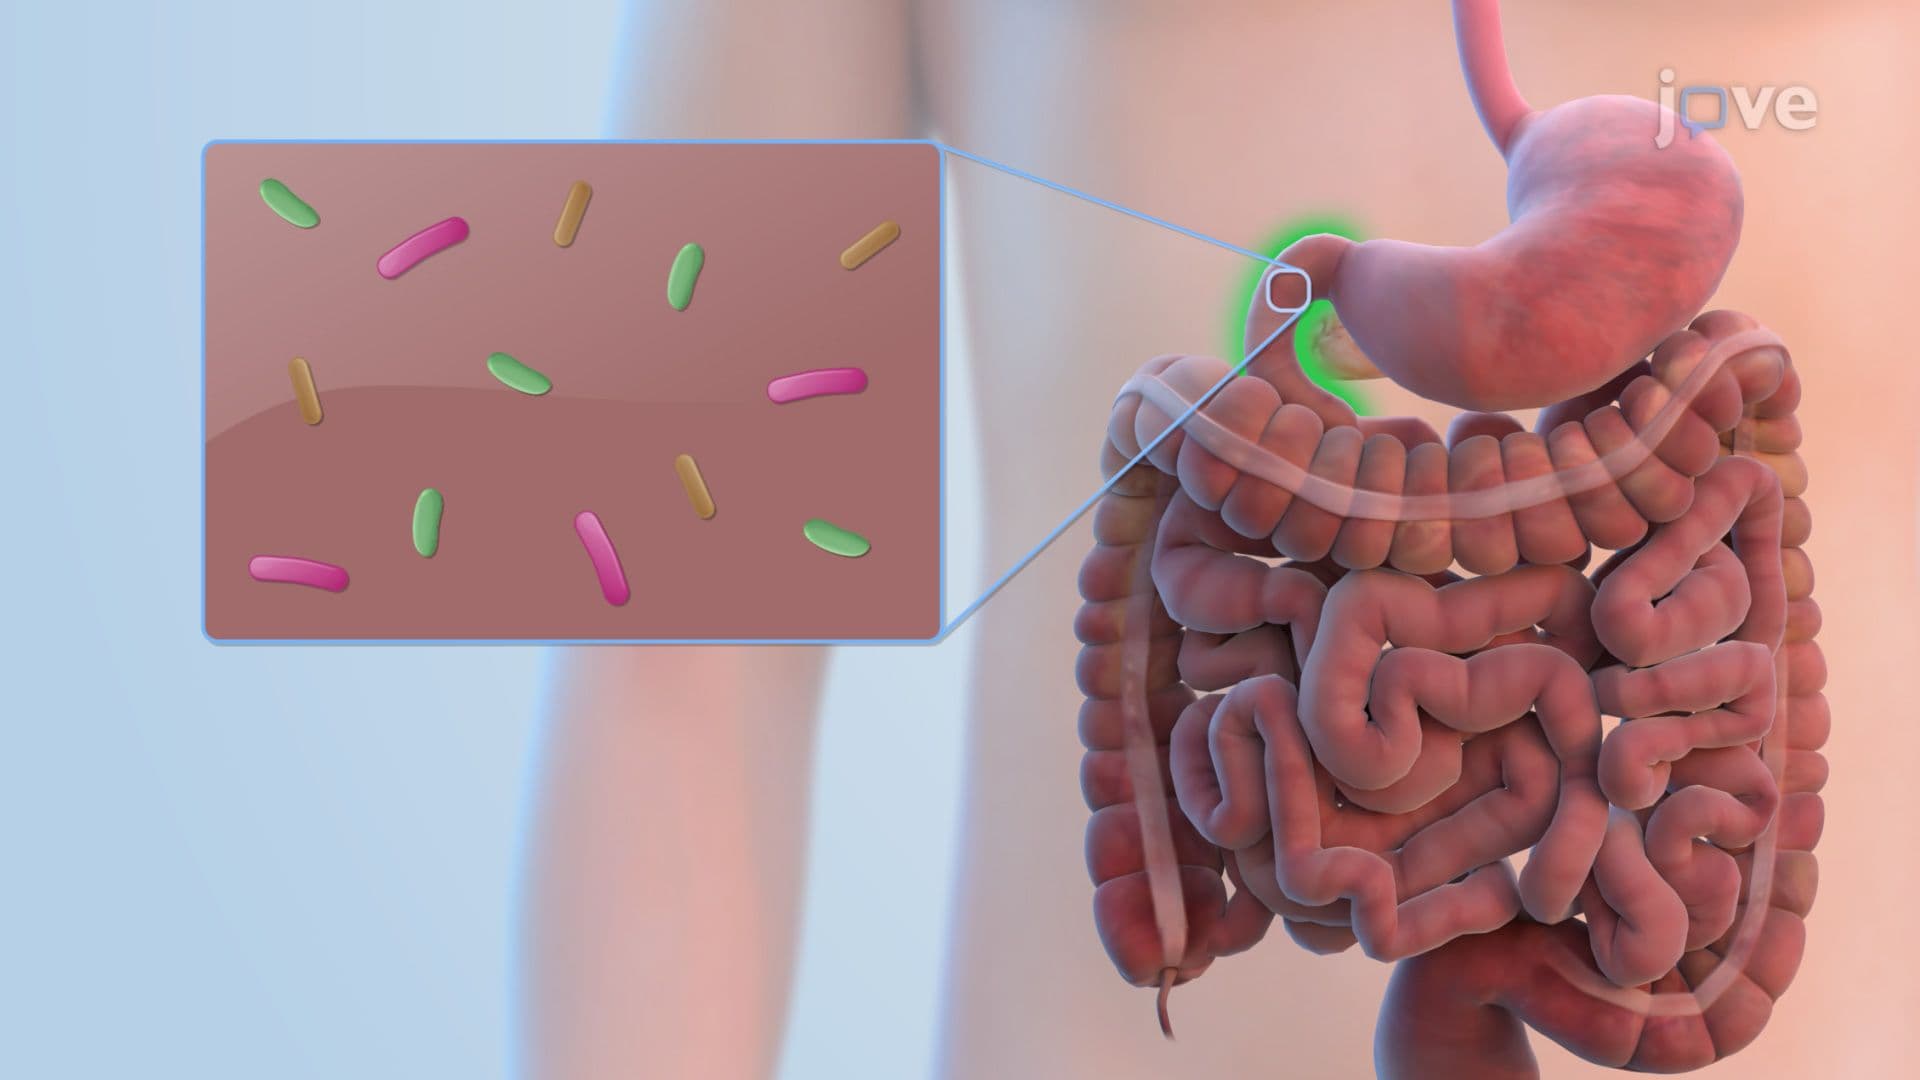
Microbiota of the Stomach and Small Intestine
 01:24
Peptic Ulcer Disease II: Pathophysiology
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...