Related Experiment Video
Updated: Sep 29, 2026
Receptor Autoradiography Protocol for the Localized Visualization of Angiotensin II Receptors
Published on: June 7, 2016
Autoantibodies against AT1-receptor and alpha1-adrenergic receptor in patients with hypertension
Yu-Hua Liao1, Yu-Miao Wei, Min Wang
1Institute of Cardiology, Union Hospital, Tongji Medical College, Huazhong University of Science and Technology, Wuhan, PR China. lyh123@public.wuhan.cngb.com

Insights
Autoantibodies against the angiotensin II type 1 receptor (AT1-receptor) and alpha1-adrenergic receptor are more prevalent in patients with hypertension, especially refractory hypertension. These autoantibodies may contribute to the development of hypertension.
Area of Science:
- Cardiology
- Immunology
- Nephrology
Background:
- Hypertension affects millions globally, with refractory cases posing significant challenges.
- Autoantibodies targeting key regulatory receptors are implicated in various cardiovascular diseases.
Purpose of the Study:
- To investigate the prevalence of autoantibodies against the angiotensin II type 1 receptor (AT1-receptor) and alpha1-adrenergic receptor in hypertensive patients.
- To compare autoantibody frequencies between refractory and non-refractory hypertension groups.
Main Methods:
- Enzyme-linked immunosorbent assay (ELISA) was used to screen for autoantibodies against synthesized AT1-receptor and alpha1-adrenergic receptor epitopes.
- Patients were categorized into refractory and non-refractory hypertension groups based on treatment response.
- Plasma renin activity, angiotensin II, and catecholamine levels were measured.
Main Results:
- Autoantibody positivity rates for AT1-receptor and alpha1-adrenergic receptor were significantly higher in hypertensive patients (26.8%, 25.3%) compared to normotensives (7.5%, 5%).
- Frequencies were markedly elevated in refractory hypertension (42.9%, 36.7%) versus non-refractory hypertension (10.4%, 13.5%).
- Refractory hypertension group showed higher levels of angiotensin II, catecholamine, proteinuria, and serum creatinine.
Conclusions:
- Autoantibodies against AT1-receptor and alpha1-adrenergic receptor are more frequent in hypertensive individuals, particularly those with treatment-resistant hypertension.
- These autoantibodies may play a role in the pathogenesis of hypertension, especially in refractory cases.
Abstract:
This study will explore the autoantibodies against AT1-receptor and alpha1-adrenergic receptor in patients with hypertension. Forty normotensives and 194 patients with hypertension were recruited for participation in this study. All patients accepted systemic combination drug treatment for antihypertension. According to the treatment results and the definition of refractory hypertension, the patients were divided into two groups: a refractory hypertension group and a non-refractory hypertension group. The epitope of the 2nd extracellular loop of type 1 angiotensin (AT1) receptor and alpha1-adrenergic receptor were synthesized and used as antigens to screen the autoantibodies against AT1-receptor and alpha1-adrenergic receptor by ELISA. The plasma renin activity and concentration of angiotensin II and catecholamine were also examined. The positive rates of the autoantibodies against AT1-receptor and alpha1-adrenergic receptor in patients with hypertension, 26.8% (52/194) and 25.3% (49/194), respectively, were higher than those in normotensives (7.5% and 5%)(p < 0.01). Further investigation showed that the frequencies of the autoantibodies against AT1-receptor and alpha1-adrenergic receptor in patients with refractory hypertension, 42.9% (42/98) and 36.7% (36/98), respectively, were higher than those in patients with non-refractory hypertension under systematic treatment (10.4% and 13.5%)(p < 0.01). The levels of circulating angiotensin II, catecholamine, proteinuria and serum creatine were also higher in the refractory hypertension group than in the non-refractory hypertension group. The findings showed that the frequencies of autoantibodies against AT1-receptor and alpha1-adrenergic receptor were higher in patients with hypertension, particularly in those with refractory hypertension, and that these autoantibodies might play a role in the pathogenesis of hypertension.

Related Concept Videos
 01:30
Antihypertensive Drugs: Angiotensin II Receptor Blockers
 01:17
Antihypertensive Drugs: Action of β1 Blockers
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:31
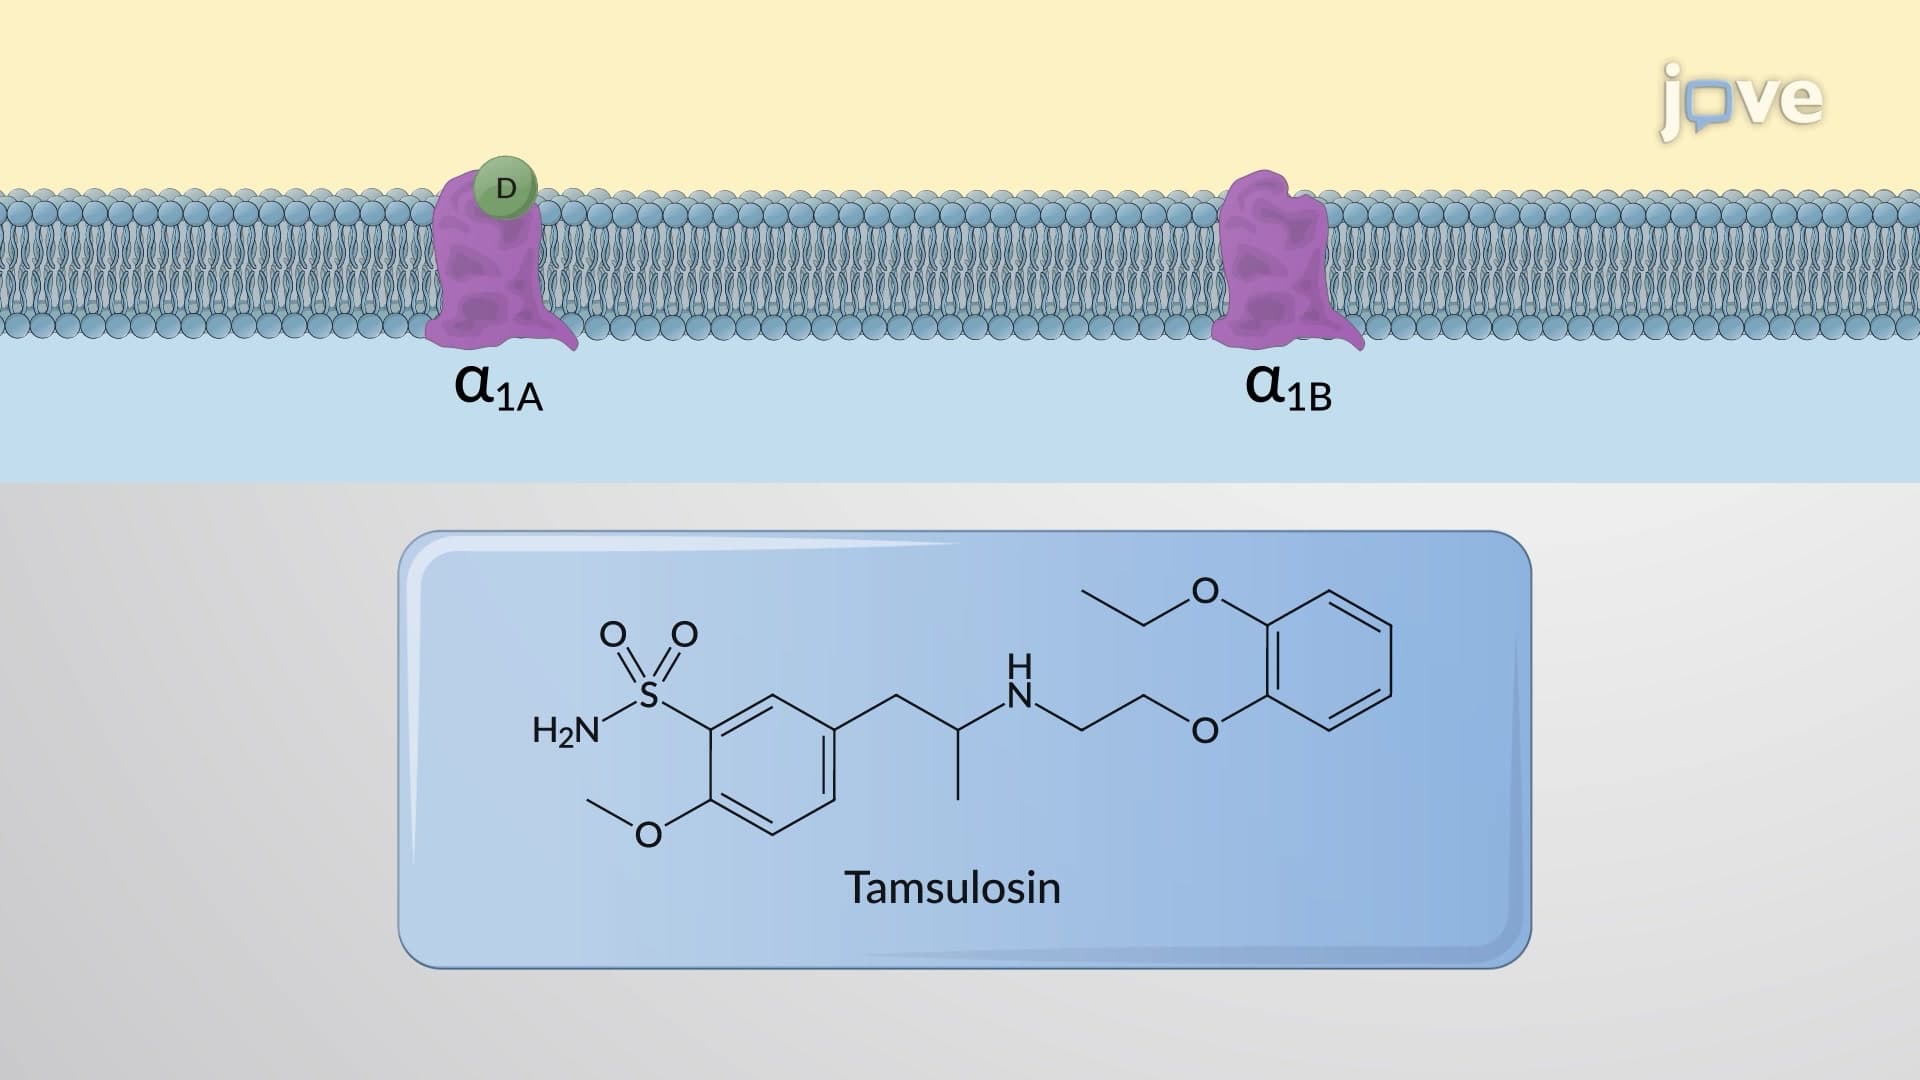
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors