Related Experiment Video
Updated: Sep 6, 2026
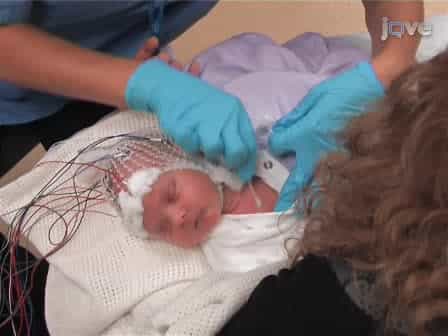
Electrophysiological Measurements and Analysis of Nociception in Human Infants
Published on: December 20, 2011
Methodological considerations for the use of heart rate variability as a measure of pain reactivity in vulnerable
Tim Oberlander1, J Philip Saul
1Division of Developmental Pediatrics, University of British Columbia, Centre for Community Child Health Research, Children's and Women's Health Centre of B.C., 4480 Oak Street, Vancouver, B.C. V6N 2H4, Canada. toberlander@cw.bc.ca

Insights
Heart rate (HR) and heart rate variability (HRV) can indicate pain in preterm infants, but NICU factors can complicate interpretation. Flexible analysis is key to understanding these cardiovascular responses to pain.
Area of Science:
- Neonatal physiology
- Pain assessment
- Cardiovascular monitoring
Background:
- Heart rate (HR) and heart rate variability (HRV) provide indices of pain reactivity, especially in preterm and ill infants with ambiguous distress signals.
- Pain perception mechanisms are present even in preterm infants, leading to generally consistent HR and HRV responses across settings.
- Preterm birth and NICU environments introduce factors that can influence and alter the specificity of HR and HRV as pain measures.
Purpose of the Study:
- To explore the utility and challenges of using HR and HRV to assess pain reactivity in vulnerable infants within the NICU setting.
- To highlight the impact of developmental and contextual factors on cardiovascular responses to pain in neonates.
Main Methods:
- Review of existing literature and methodologies for measuring and analyzing HR and HRV in infants.
- Discussion of factors influencing cardiovascular responses, including infant health, developmental stage, behavioral state, medication, and setting.
- Emphasis on the need for flexible analytical approaches, including various HRV techniques and careful selection of HR data epochs.
Main Results:
- HR and HRV responses can be influenced by NICU contextual factors, potentially masking or altering the apparent pain reactivity.
- Cardiovascular reactivity may reflect biologic capacity rather than actual pain response in some cases.
- Discordance between biologic and behavioral measures, medication effects, and developmental changes are critical considerations.
Conclusions:
- Assessing pain reactivity using cardiovascular measures in vulnerable infants requires careful consideration of multiple influencing factors.
- Flexible and comprehensive analytical strategies are necessary to accurately interpret HR and HRV responses to painful events.
- Further research is needed to refine the understanding of cardiovascular reactivity as a measure of pain in NICU populations.
Abstract:
Measures of HR and HRV offer multiple indices of reactivity to painful events. These measures are particularly helpful in preterm and ill infants where distress signals are often nonspecific and ambiguous. HR is easy to acquire, and a variety of widely used techniques are available for processing it. In general, the neuroanatomic and neurophysiologic bases for pain perception are in place even in the most preterm infant and produce patterns of HR and HRV responses that are similar across multiple settings. Developmental and experiential factors related to preterm birth, however, may affect these HR responses. Furthermore, evaluation of ill infants in an NICU setting adds multiple contextual factors that potentially influence HR and HRV and alter their specificity as measures of pain. In some cases, it may appear that pain reactivity is reduced when, in fact, HR reactivity is only an expression of the biologic capacity to produce a response, not the presence of a response itself. The nature of the setting and the infant's health, developmental stage, and behavioral state all contribute to potentially altering HR responses to painful events in this setting. Thus, the methodology used and its application must be flexible. A variety of HRV analysis techniques may be needed to identify a variety of response patterns and mechanisms that influence pain reactivity. Furthermore, careful selection of HR epochs for stationarity, an understanding of the potential discordance between biologic and behavioral measures, the effects of medication, and an accounting for developmental differences that occur during a typical NICU course are all critical factors for investigators to be aware of. Understanding cardiovascular reactivity as a measure of response to painful events in vulnerable infants requires ongoing work.
More Related Videos


Related Concept Videos
 01:14
Temperature Measurement Sites
Oral: When assessing oral temperature, the thermometer tip should be placed under the tongue in the posterior sublingual pocket. It offers accurate readings and can be...
 01:13
Special considerations while measuring pulse
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: