Related Experiment Video
Updated: Sep 28, 2026
Modeling Posthemorrhagic Hydrocephalus of Prematurity in Rats
Published on: March 28, 2025
Managing subdural fluid collection in infants
Hiroji Miyake1, Yoshinaga Kajimoto, Tomio Ohta
1Nishinomiya Kyoritsu Neurosurgical Hospital, Imazuyamanakacho 12-1, Nishinomiya city, Hyogo 663-8211, Japan. miyake@nk-hospital.or.jp

Insights
This study classifies infantile subdural fluid collection (SFC) into four stages and recommends treatments. Fontanel tapping is useful for all stages, especially stage II, while continuous drainage suits stages II and III, and burr hole irrigation is for stage IV.
Area of Science:
- Pediatric Neurosurgery
- Neurology
- Medical Imaging
Background:
- Infantile subdural fluid collection (SFC) is classified into four chronological stages.
- Stages include: I (arachnoid tear), II (inner membrane), III (inner and outer membrane), and IV (subdural hematoma).
Observation:
- Treatment strategies vary based on the SFC stage.
- Fontanel tapping is applicable to all stages, particularly stage II, with minimal bleeding risk using small needles.
- Continuous external drainage is suitable for stages II and III, carrying a risk of infection.
- Burr hole irrigation is the primary treatment for stage IV.
Findings:
- Ommaya reservoir implantation and endoscopic observation are effective for SFC cavities.
- Subduralperitoneal shunts are generally not recommended for SFC treatment.
Implications:
- This staging and treatment approach provides a framework for managing infantile subdural fluid collections.
- Tailored interventions can optimize outcomes for pediatric patients with SFC.
Introduction:
The authors classify infantile subdural fluid collection (SFC) into four chronological stages: (I) SFC with arachnoid tear, (II) SFC with inner membrane, (III) SFC with inner and outer membrane, and (IV) subdural hematoma, and discuss the appropriate treatment for each stage.
Conclusions:
Fontanel tapping can be used for every stage of SFC, but it is best indicated for stage II. Massive bleeding seldom occurs with punctures made with a small needle. Continuous external drainage is indicated for stages II and III. Although the risk of bleeding decreases even in stage III, this method involves a risk of infection. Burr hole irrigation is usually indicated for stage IV. Implantation of an Ommaya reservoir and endoscopic observation of the SFC cavity along with burr hole irrigation are very useful. A subduroperitoneal shunt cannot be recommended for the treatment of SFC in most cases.
Related Concept Videos
 01:14
Increased Intracranial Pressure l: Introduction
 01:19
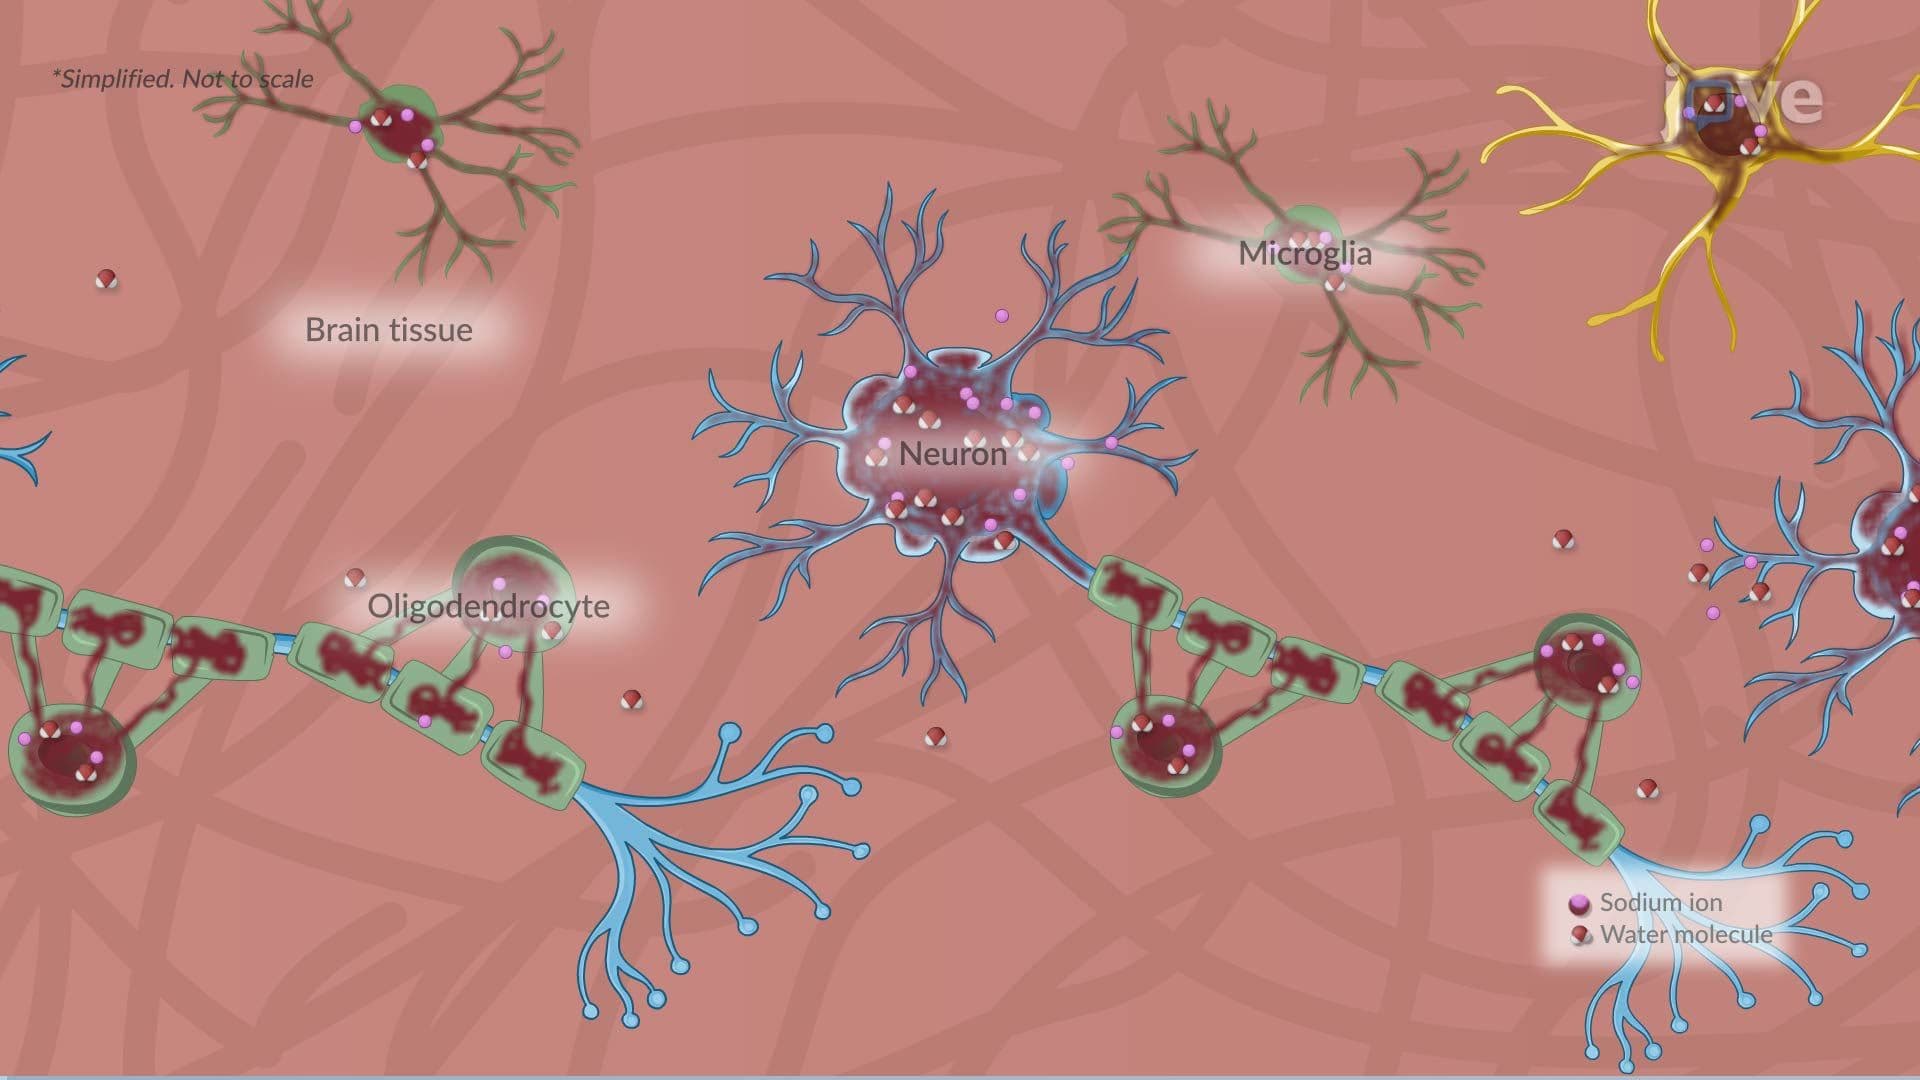
Cerebral Edema l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:26
Brain Abscess l: Introduction
 01:21
Cerebrospinal Fluid
CSF Production
CSF is produced mainly in the choroid plexus, a network of capillaries and ependymal cells located within the ventricular system of the brain.
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...