Related Experiment Video
Updated: Sep 28, 2026


Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
Identification of extremely slow conduction in the cavotricuspid isthmus during common atrial flutter ablation
Jian Chen1, Christian de Chillou, Per Ivar Hoff
1Department of Heart Disease, Haukeland University Hospital, Bergen, Norway. jian.chen@med.uib.no

Introduction:
Complete isthmus block has been used as an endpoint for radiofrequency ablation for common atrial flutter (AF). We sought to systematically evaluate extremely slow conduction (ESC), which is easily misinterpreted as complete block.
Methods And Results:
We studied 107 consecutive patients (92 men, 15 women, 58 +/- 11 years) who had undergone a successful AF ablation procedure. A 24-pole catheter was positioned along the tricuspid annulus spanning the isthmus. Complete isthmus block was defined as the presence of a complete corridor of double potentials along the ablation line. Activation delay time (AT), activation difference (deltaA) between two adjacent dipoles, maximum activation difference (deltaA(max)), change in polarity (CP) and change in amplitude (CA) of the bipolar atrial electrogram were recorded and P-wave morphology in the surface electrocardiogram was analyzed. ESC was observed in 16 patients. Between ESC and complete block, differences were found on the two lateral dipoles adjacent to the ablation line (AT: 148 +/- 17 vs. 183 +/- 27 ms and 155 +/- 18 vs. 170 +/- 28 ms, P < 0.01; deltaA: -91 +/- 22 vs. -126 +/- 28 ms and -7 +/- 13 vs. 13 +/- 6 ms, P < 0.01). Statistically significant differences in CP were detected on the relevant dipoles (7/16 vs. 14/16 and 6/16 vs.13/16, P < 0.05). No significant difference was found either in CA or in terminal P wave positivity. Mean deltaA(max) were 13.8 +/- 5.0 and 27.8 +/- 9.5 ms (P < 0.001) respectively in ESC and complete block. Two types of ESC, regular and irregular, were demonstrated during the ablation procedure.
Conclusions:
(1) ESC was observed in 15% of the patients during the AF ablation procedure. (2) The parameters of AT, deltaA, and CP may help to differentiate ESC from complete block. DeltaA(max) might be the most powerful indicator. (3) To verify complete block, it is essential to position the mapping catheter across the CTI in order to demonstrate the activation sequence up to the ablation line.
More Related Videos
 10:46
Non-fluoroscopic Catheter Tracking for Fluoroscopy Reduction in Interventional Electrophysiology
Published on: May 26, 2015
 06:57
Ablation of Ischemic Ventricular Tachycardia Using a Multipolar Catheter and 3-dimensional Mapping System for High-density Electro-anatomical Reconstruction
Published on: January 31, 2019
Related Concept Videos
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:29
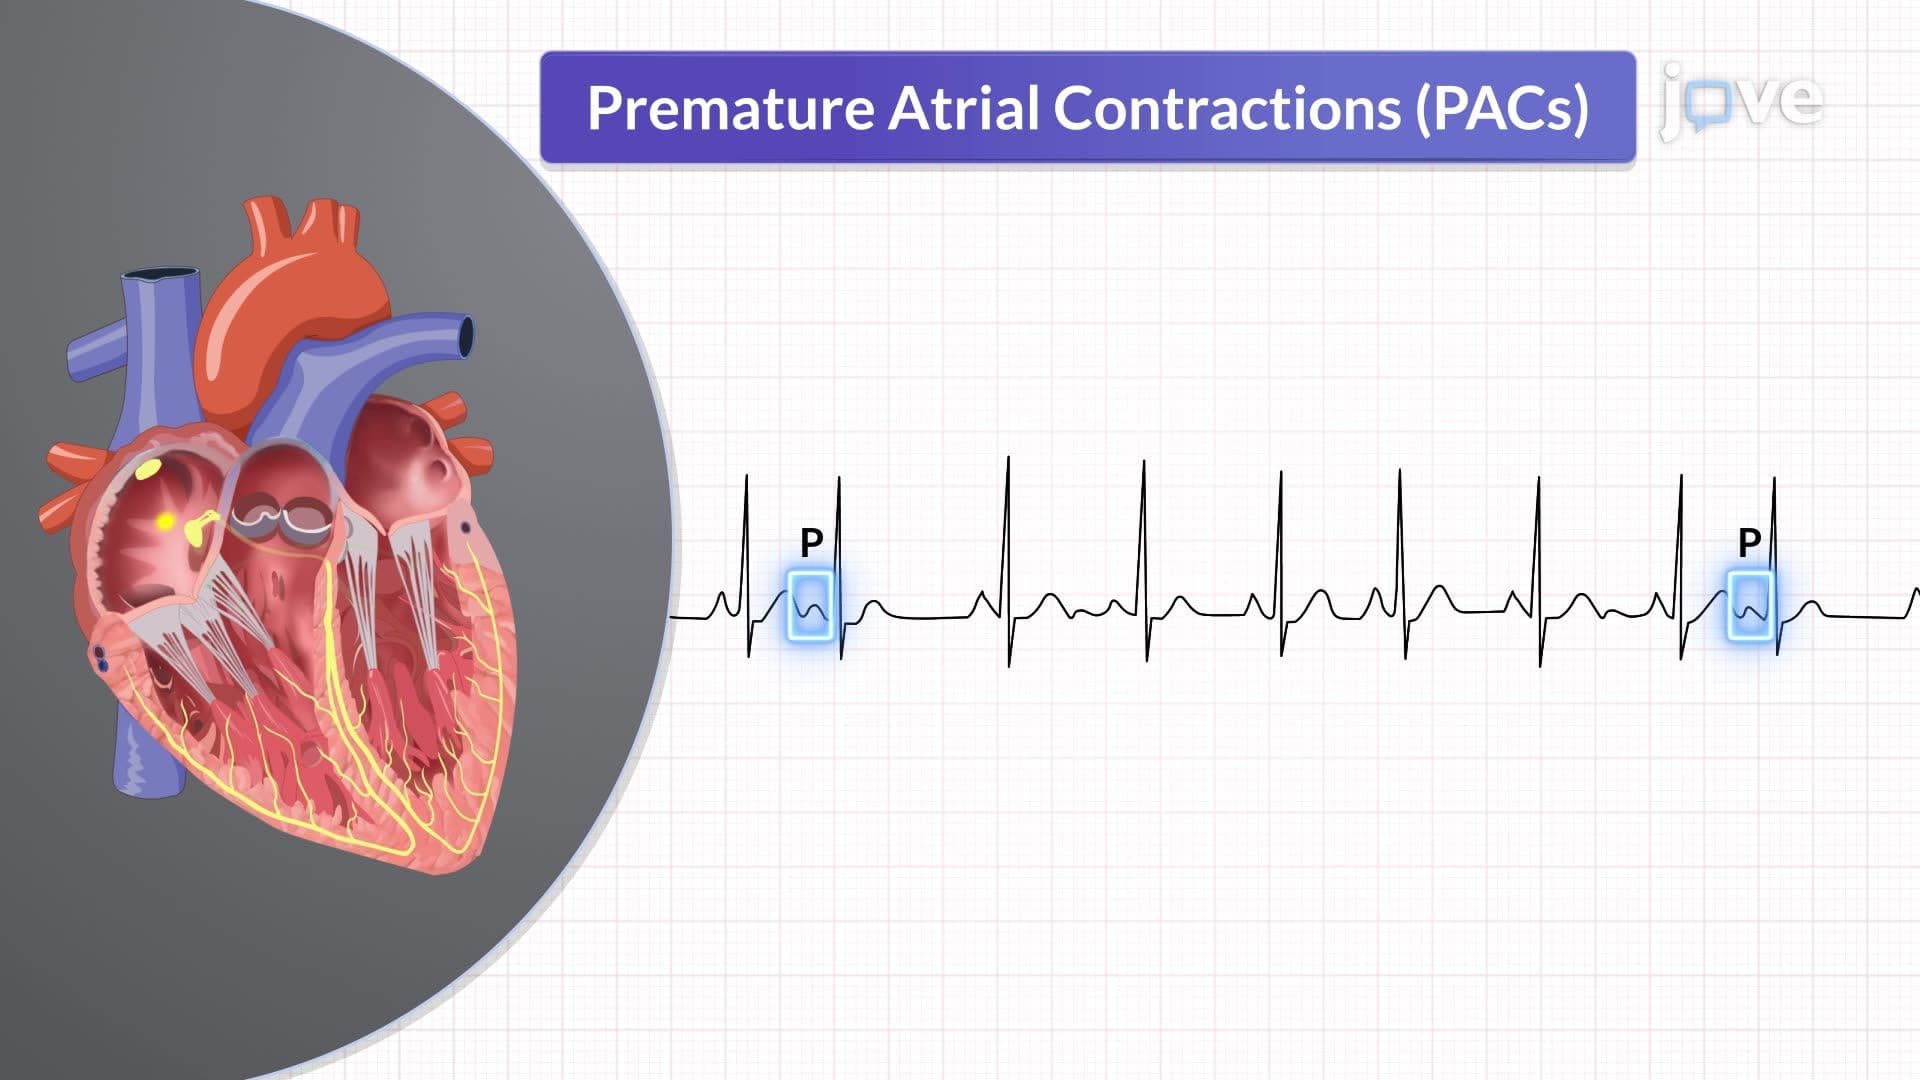
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias