Related Experiment Video
Updated: Aug 14, 2026


Implantation of Total Artificial Heart in Congenital Heart Disease
Published on: July 17, 2014
Mid-term outcome after partial left ventriculectomy in pediatric patients
H Sugiyama1, T Komai, M Hoshiai
1Department of Pediatric, Yamanashi Medical University, 1,110, Shimokato, Tamaho, Nakakoma, Yamanashi, 409-3898, Japan.

Insights
Partial left ventriculectomy (PLV) offers a viable option for pediatric patients with severe dilated cardiomyopathy (DCM). While one patient required a heart transplant, all three showed improved cardiac function and survived the mid-term after PLV.
Area of Science:
- Pediatric Cardiology
- Cardiac Surgery
- Cardiomyopathy Research
Background:
- Dilated cardiomyopathy (DCM) in pediatric patients presents significant therapeutic challenges.
- Current treatment options for severe pediatric DCM are limited, necessitating exploration of surgical interventions.
Observation:
- Partial left ventriculectomy (PLV) was performed on three pediatric patients diagnosed with DCM.
- Patient ages at surgery ranged from eight months to three years.
- Two patients experienced improved left ventricular function and clinical status post-PLV.
Findings:
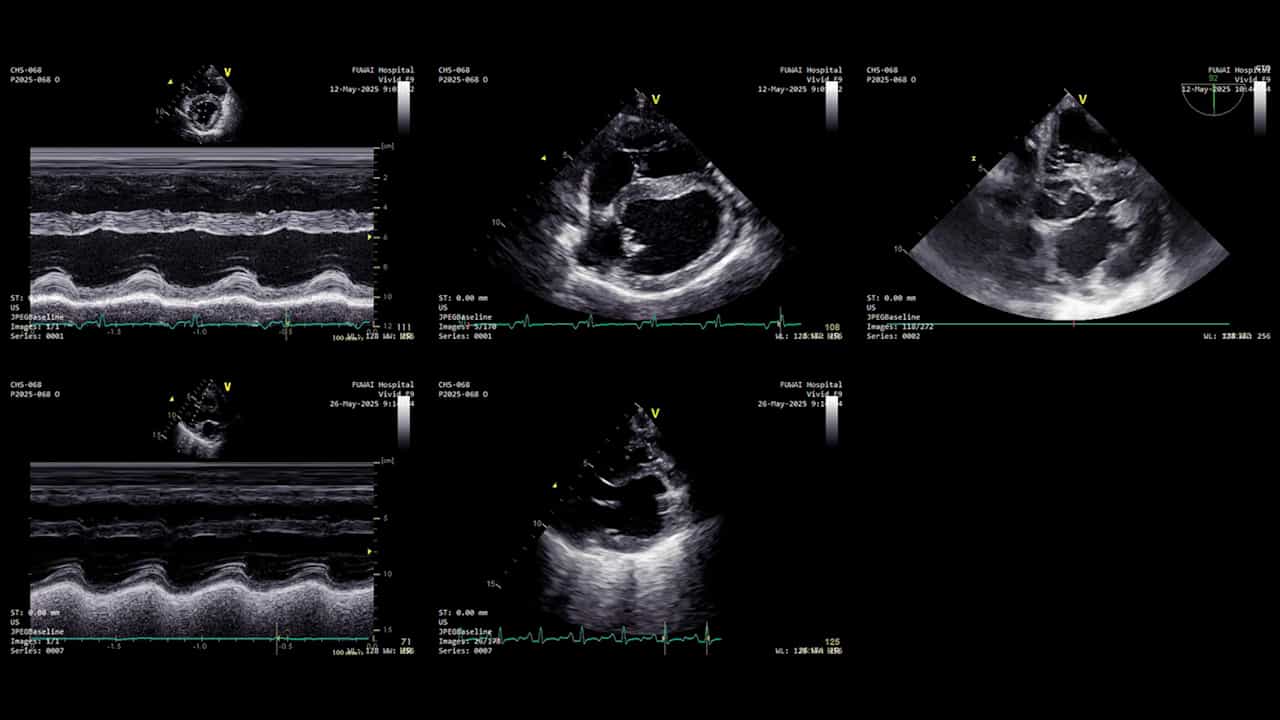
- Postoperative echocardiography demonstrated increased left ventricular fraction shortening (FS) in all patients following PLV.
- Patient #1, despite requiring a heart transplant, is alive; Patients #2 and #3 showed sustained improvement.
- Optimal timing for PLV appears to be when mechanical ventilation or aggressive catecholamine support is necessary.
Implications:
- PLV is a potentially effective surgical option for select pediatric patients with severe DCM.
- Further research into the long-term outcomes and optimal patient selection for PLV is warranted.
- This approach may improve cardiac function and survival rates in pediatric DCM cases refractory to medical management.
Abstract:
From May 1998 to April 2000, we performed partial left ventriculectomy (PLV) in 3 pediatric patients with dilated cardiomyopathy (DCM). At the time of the surgery, their age ranged from eight months to three years. The first patient eventually had to receive a heart transplant, but all patients treated with PLV are alive to this day. Patient #1 was diagnosed with DCM at the age of five months, PLV was done on a semi-urgent basis at the age of eight months, when medium dose IV catecholamine therapy and mechanical ventilation were required. Fraction shortening (FS) as shown by echocardiography increased postoperatively from 8% to 15% along with marked clinical improvement. Her heart failure deteriorated three months after the surgery, and received a heart transplant in the United States when she was one year and two months old. Patient #2 developed severe heart failure two months after correction of a ventricular septal defect. Aggressive medical therapy failed to improve his condition, therefore PLV was done on an elective basis at the age of three years and five months. [The patient was initially hospitalized and underwent low dose catecholamine.] Postoperative course was well. The ventriculography one year after surgery showed an improvement of the left ventricular FS from 12% to 27% after PLV. He was still doing well at his most recent check up. Patient #3 was diagnosed with DCM as a neonate. PLV was done on an elective basis at the age of two years and five months. Her postoperative course was generally well. FS on echocardiography increased postoperatively from 10% to 25% along with marked clinical improvement. The timing of performing PLV is the most essential factor for postoperative course in our experiences. We consider that the best timing is when aggressive catecholamine infusion or mechanical ventilation is required. The mid-term outcome of PLV of pediatric patients is considered to be acceptable. We believe that PLV should be considered as a viable option for severe DCM patients.
More Related Videos

Related Concept Videos
 01:22
Mitral Stenosis I: Introduction
 01:29
Cardiomyopathy V: Interprofessional Care