Related Experiment Video
Updated: Jul 23, 2026
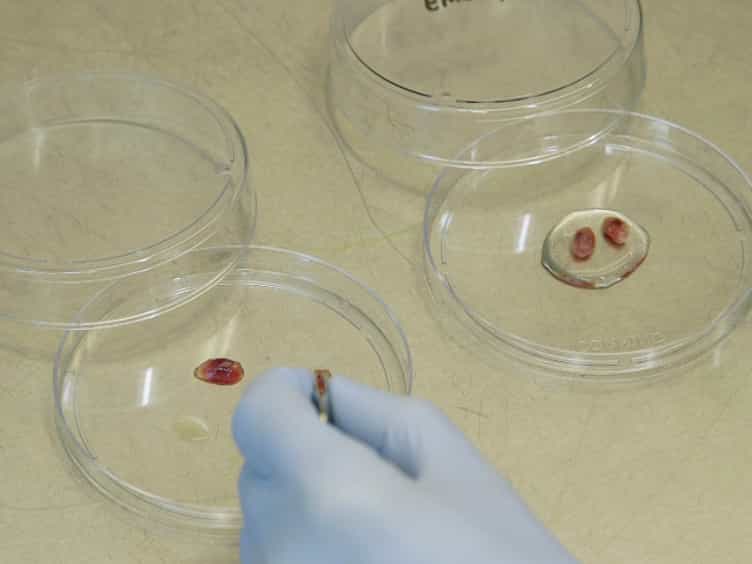
Culture of Murine Embryonic Metatarsals: A Physiological Model of Endochondral Ossification
Published on: December 3, 2016
Bone growth oscillation: longitudinal metabolic process of bone growth in congenital adrenal hyperplasia and
O Arisaka1, H Kanno, M Negishi
1Department of Pediatrics, Dokkyo University School of Medicine, Mibu, Tochigi, Japan.

Insights
Serum osteocalcin (OC) levels in children with congenital adrenal hyperplasia (CAH) showed variable bone growth, unlike those with nonendocrine short stature (NESS) who had stable bone growth. Further research is needed to understand these metabolic differences.
Area of Science:
- Pediatric Endocrinology
- Bone Metabolism Research
- Biochemical Markers in Growth
Background:
- Understanding bone growth in children is crucial for identifying growth disorders.
- Serum osteocalcin (OC) is a key marker for bone metabolism.
- Congenital adrenal hyperplasia (CAH) and nonendocrine short stature (NESS) present distinct growth patterns.
Purpose of the Study:
- To investigate the longitudinal relationship between serum osteocalcin (OC) levels and growth velocity in prepubertal children.
- To compare the metabolic bone growth processes in children with CAH versus NESS.
- To explore potential differences in bone metabolism variability.
Main Methods:
- Longitudinal observation of 10 prepubertal CAH patients and 9 prepubertal NESS patients over 7 years.
- Bi-annual measurements of serum osteocalcin (OC) levels.
- Monitoring of growth velocity throughout the study period.
Main Results:
- Patients with CAH displayed wide fluctuations in both growth velocity and serum OC levels, indicating variable bone metabolism.
- Patients with NESS showed stable growth velocity and consistently narrow-range serum OC levels, suggesting stable bone metabolism.
- A clear divergence in bone metabolic processes was observed between the two groups.
Conclusions:
- Children with CAH exhibit metabolically variable bone growth, contrasting with the stable bone growth seen in NESS patients.
- The observed differences in bone metabolism between CAH and NESS warrant further investigation.
- Future research should explore the relationship between these metabolic processes and bone structure or density.
Abstract:
To clarify the longitudinal metabolic process of bone growth in children, we observed the relationship between the level of serum osteocalcin (OC), a marker of bone metabolism, and growth velocity in 10 prepubertal patients with congenital adrenal hyperplasia (CAH) due to 21-hydroxylase deficiency and 9 prepubertal patients with nonendocrine short stature (NESS), but no major hormonal abnormalities influencing bone metabolism. Observations were made every 6 months over a 7-year period. In patients with CAH who exhibited a wide variation in growth velocity during the course of the investigation, the levels of OC fluctuated over a wide range, suggesting metabolically variable bone growth. In contrast, in patients with NESS who exhibited a relatively stable growth velocity, the OC level remained within a narrow range, suggesting metabolically stable bone growth. The meaning of such divergent metabolic processes of bone growth observed in CAH and NESS and its relationship to actual bone structure or bone intensity should be further investigated.


Related Concept Videos
 01:40
Bone Remodeling
 01:29
Bone Formation by Intramembranous Ossification
The process begins when mesenchymal cells in the embryonic skeleton gather together and differentiate into osteogenic cells, which then develop into...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:24
Bone Formation by Endochondral Ossification