Related Experiment Video
Updated: Sep 28, 2026

Using a Murine Model of Psychosocial Stress in Pregnancy as a Translationally Relevant Paradigm for Psychiatric Disorders in Mothers and Infants
Published on: June 13, 2021
Women with schizophrenia: pregnancy outcome and infant death among their offspring
Emma Nilsson1, Paul Lichtenstein, Sven Cnattingius
1Department of Medical Epidemiology, Karolinska Institutet, SE-171 77, Stockholm, Sweden.

Schizophrenia in the mother may imply an increased risk of adverse pregnancy outcome. However, inconclusive findings, unknown pathological mechanisms and possible confounding by social factors and smoking requests further explorations. The aim of this study were to (1) examine non-optimal pregnancy outcome using data from a population-based cohort, controlling for covariates known to influence fetal growth; and (2) perform separate analyses of women diagnosed before childbirth and women hospitalized for schizophrenia during pregnancy. The study sample comprised 2096 births by 1438 mothers diagnosed with schizophrenia (of whom 696 mothers were antenatal diagnosed and 188 admitted during pregnancy) and 1,555,975 births in the general population. We found significantly increased risks for stillbirth, infant death, preterm delivery, low birth weight, and small-for-gestational-age among the offspring of women with schizophrenia. Women with an episode of schizophrenia during pregnancy had the highest risks (e.g., low birth weight; OR 4.3, 95% CI 2.9-6.6 and stillbirth; OR 4.4, 95% CI 1.4-13.8). Controlling for a high incidence of smoking during pregnancy among schizophrenic women (51% vs. 24% in the normal population) and other maternal factors (single motherhood, maternal age, parity, maternal education, mothers' country of birth and pregnancy-induced hypertensive diseases) in a multiple regression model, reduced the risk estimates markedly. However, the risks for adverse pregnancy outcomes were even after adjustments generally doubled for women with an episode of schizophrenia during pregnancy compared to women in the control group (e.g., low birth weight; OR 2.3, 95% CI 1.5-3.5, preterm delivery; OR 2.4, 95% CI 1.5-3.8 and stillbirth; OR 2.5, 95% CI 0.8-7.9). The risks for preterm delivery and low birth weight were significantly elevated throughout the analyses. We conclude that schizophrenia in the mother implies an increased risk for poor perinatal outcome, not fully explained by maternal factors, and a need to consider a common familial (probably genetic) vulnerability for pre- and perinatal stress and schizophrenia.
Schizophrenia in the mother may imply an increased risk of adverse pregnancy outcome. However, inconclusive findings, unknown pathological mechanisms and possible confounding by social factors and smoking requests further explorations. The aim of this study were to (1) examine non-optimal pregnancy outcome using data from a population-based cohort, controlling for covariates known to influence fetal growth; and (2) perform separate analyses of women diagnosed before childbirth and women hospitalized for schizophrenia during pregnancy. The study sample comprised 2096 births by 1438 mothers diagnosed with schizophrenia (of whom 696 mothers were antenatal diagnosed and 188 admitted during pregnancy) and 1,555,975 births in the general population. We found significantly increased risks for stillbirth, infant death, preterm delivery, low birth weight, and small-for-gestational-age among the offspring of women with schizophrenia. Women with an episode of schizophrenia during pregnancy had the highest risks (e.g., low birth weight; OR 4.3, 95% CI 2.9-6.6 and stillbirth; OR 4.4, 95% CI 1.4-13.8). Controlling for a high incidence of smoking during pregnancy among schizophrenic women (51% vs. 24% in the normal population) and other maternal factors (single motherhood, maternal age, parity, maternal education, mothers' country of birth and pregnancy-induced hypertensive diseases) in a multiple regression model, reduced the risk estimates markedly. However, the risks for adverse pregnancy outcomes were even after adjustments generally doubled for women with an episode of schizophrenia during pregnancy compared to women in the control group (e.g., low birth weight; OR 2.3, 95% CI 1.5-3.5, preterm delivery; OR 2.4, 95% CI 1.5-3.8 and stillbirth; OR 2.5, 95% CI 0.8-7.9). The risks for preterm delivery and low birth weight were significantly elevated throughout the analyses. We conclude that schizophrenia in the mother implies an increased risk for poor perinatal outcome, not fully explained by maternal factors, and a need to consider a common familial (probably genetic) vulnerability for pre- and perinatal stress and schizophrenia.
More Related Videos
 07:13
Induction of Maternal Immune Activation in Mice at Mid-gestation Stage with Viral Mimic Poly(I:C)
Published on: March 25, 2016
 09:09
Generating a Reproducible Model of Mid-Gestational Maternal Immune Activation using Poly(I:C) to Study Susceptibility and Resilience in Offspring
Published on: August 17, 2022
Related Concept Videos
 01:29
Biological Causes of Schizophrenia
Genetic Factors in Schizophrenia
The genetic basis of schizophrenia is strongly supported by family and twin studies.
 02:57
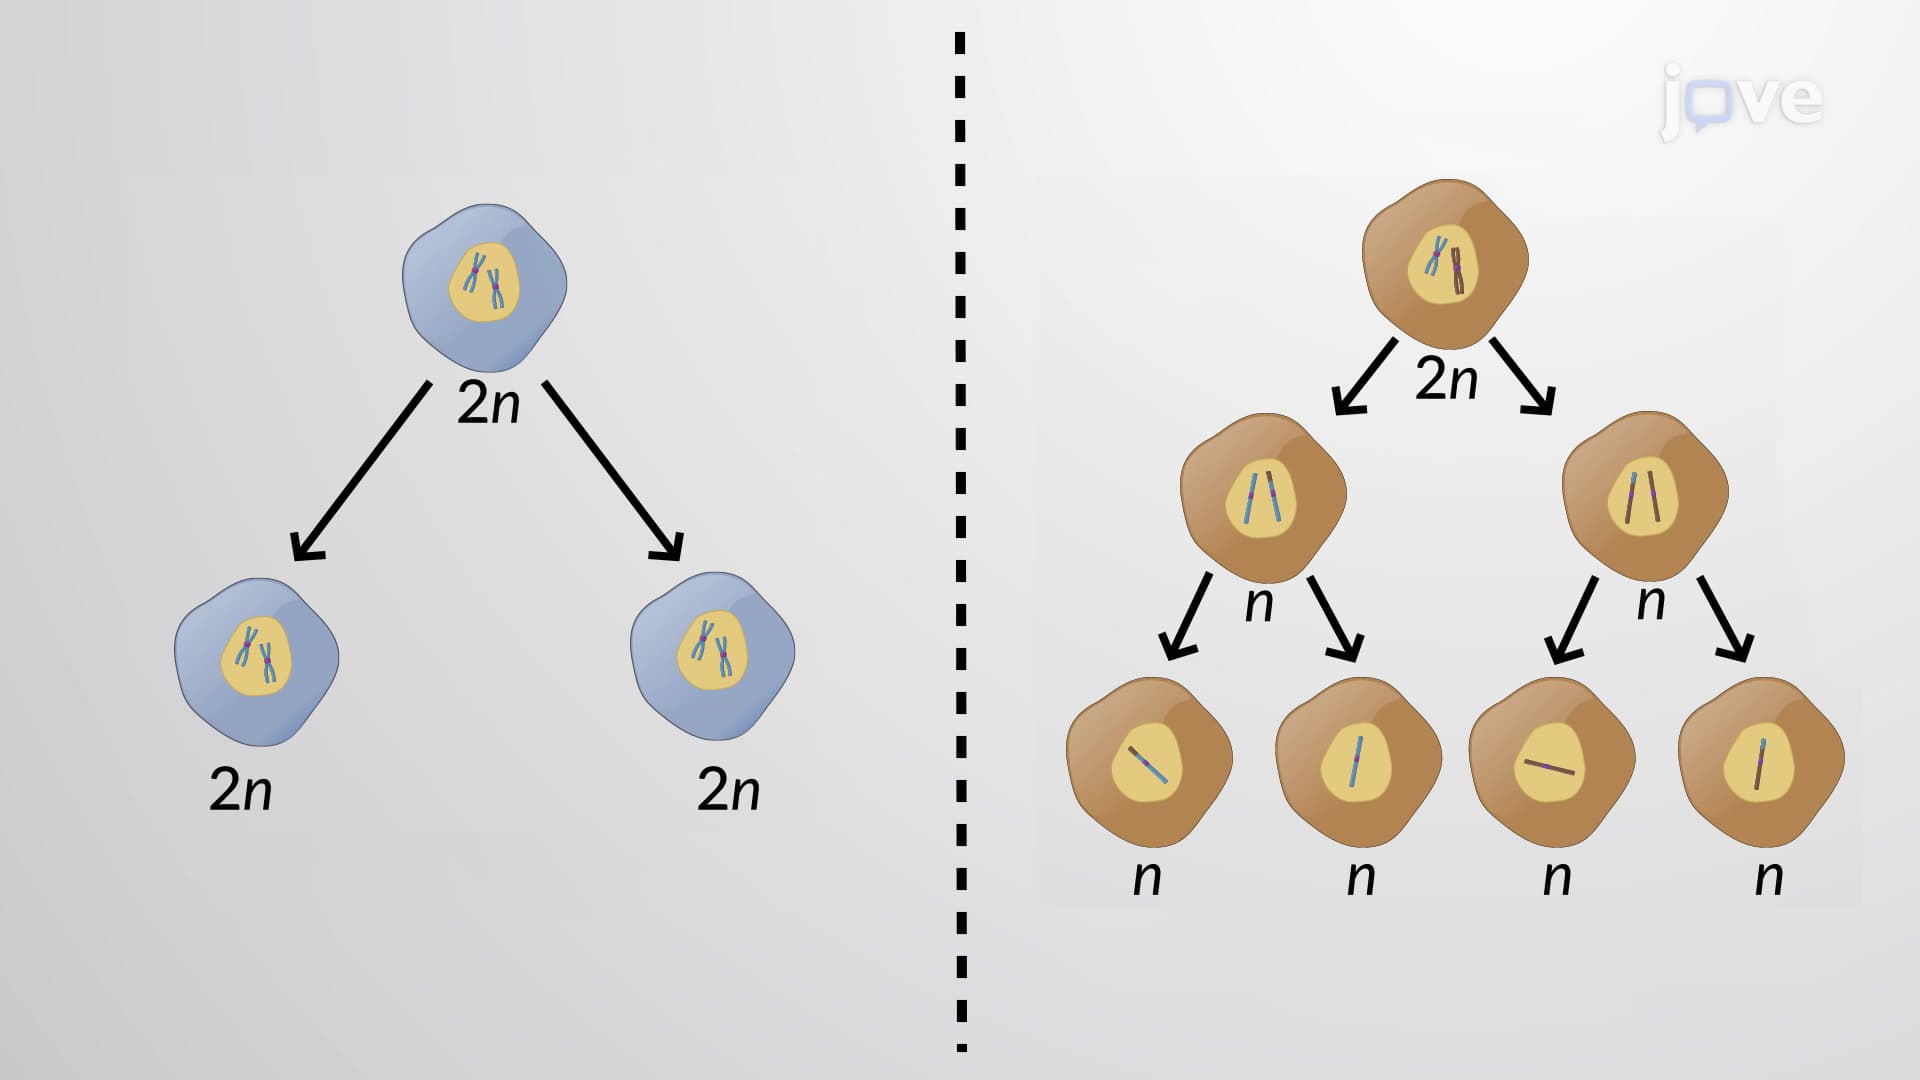
Meiosis vs. Mitosis
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...
 01:30
Negative and Cognitive Symptoms of Schizophrenia
Negative Symptoms
Negative symptoms of schizophrenia manifest as deficits in normal emotional and behavioral functioning, profoundly impacting daily life. Individuals with schizophrenia often display a flat affect, characterized by a near-total absence of emotional expression,...