Related Experiment Video
Updated: Sep 28, 2026

Creating Matched In vivo/In vitro Patient-Derived Model Pairs of PDX and PDX-Derived Organoids for Cancer Pharmacology Research
Published on: May 5, 2021
Dosage adjustment and pharmacokinetic profile of irinotecan in cancer patients with hepatic dysfunction
Eric Raymond1, Valérie Boige, Sandrine Faivre
1Department of Medicine, Gustave Roussy Institute, Villejuif, France. raymond@igr.fr

Purpose:
To determine the recommended dose (RD) and the pharmacokinetic profile of irinotecan and its metabolites in cancer patients with hyperbilirubinemia.
Patients And Methods:
Patients were assigned to four treatment groups according to their baseline total bilirubin level. Patients in group I (bilirubin within normal range) and group II (bilirubin 1.0 to 1.5 times upper limit of normal [ULN]) received a dose of 350 mg/m(2) every 3 weeks. Patients in groups III (bilirubin 1.51 to 3.0 times ULN) and IV (bilirubin > 3.1 times ULN) received starting doses of 175 and 100 mg/m(2), respectively. RDs were defined according to the dose-limiting toxicity (DLT) experienced at cycle 1.
Results:
Thirty-three patients including 21 gastrointestinal cancers were included. Grade 4 febrile neutropenia and diarrhea were common DLTs in patients with hyperbilirubinemia. At a dose of irinotecan 350 mg/m(2), DLTs were observed in two of seven and one of five patients in groups I and II, respectively. In group III, escalated doses of irinotecan 175, 200, and 240 mg/m(2) were associated with DLTs in one of seven, one of five, and three of six patients, respectively. No DLT was observed in group IV. High bilirubin and alkaline phosphatase levels were associated with an exponential decrease in the clearance of irinotecan. Pharmacokinetic analysis showed that the relative increase in exposure was likely caused by reduced biliary excretion.
Conclusion:
We showed that baseline total bilirubin level could be used to determine the appropriate dose of irinotecan in cancer patients with hepatic dysfunction. Doses of 350 mg/m(2) and 200 mg/m(2) were considered RDs in patients with bilirubin values
Related Concept Videos
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:14
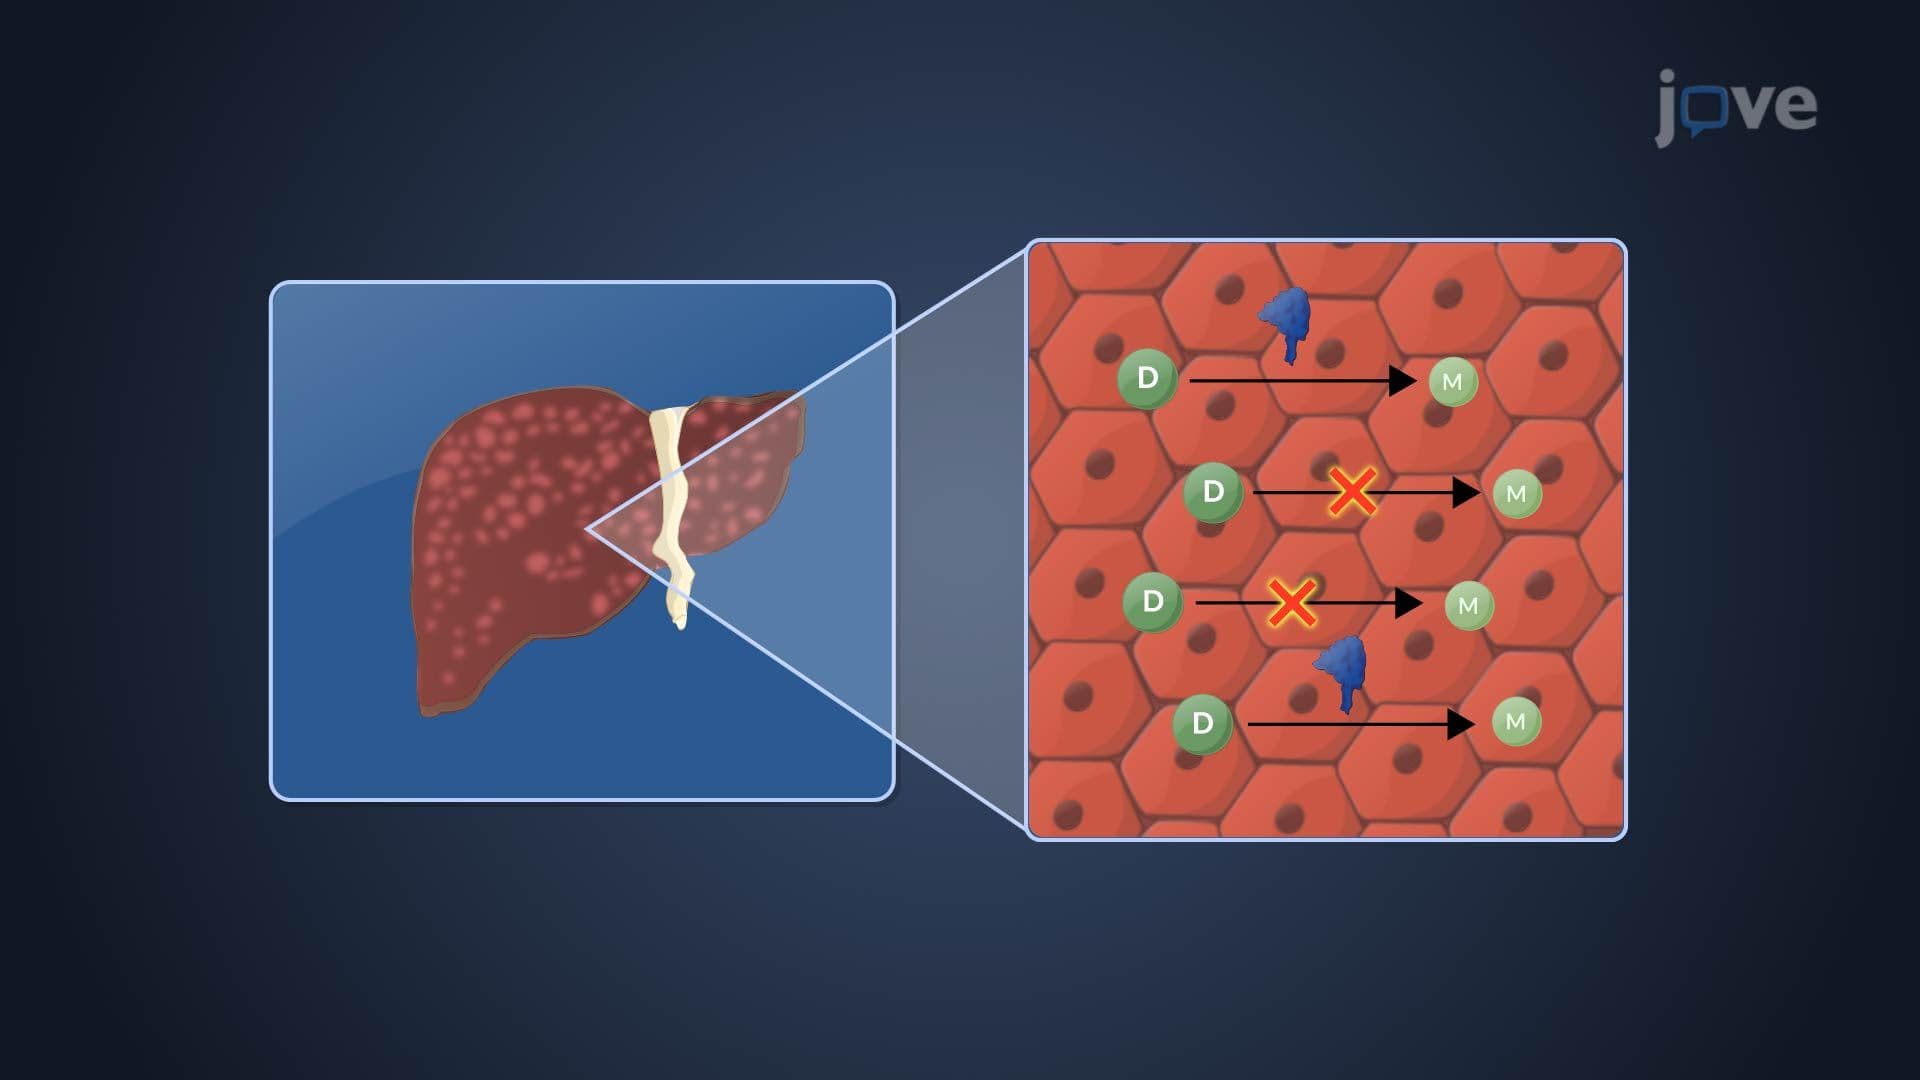
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test