Related Experiment Video
Updated: Sep 28, 2026


An Ivor Lewis Esophagectomy Designed to Minimize Anastomotic Complications and Optimize Conduit Function
Published on: April 17, 2020
Long-term dilatation of caustic strictures of the oesophagus
1Department of Surgery, Starship Hospital, Auckland, New Zealand.

Insights
Long-term esophageal dilatation effectively treats most caustic strictures of the esophagus (CSO) in children. This minimally invasive approach offers successful outcomes with a low complication rate, avoiding surgery for many young patients.
Area of Science:
- Pediatric Gastroenterology
- Otolaryngology
- Surgical Innovation
Background:
- Caustic strictures of the esophagus (CSO) present a significant management challenge in pediatric care.
- Current treatment strategies for CSO vary, necessitating research into effective long-term solutions.
Purpose of the Study:
- To evaluate the efficacy and safety of long-term dilatation for managing pediatric caustic strictures of the esophagus.
- To assess the success rates and complication profiles of dilatation therapy in this patient population.
Main Methods:
- Retrospective analysis of 109 children admitted for caustic ingestion.
- Focus on 10 children who developed esophageal strictures and underwent long-term dilatation therapy.
- Data collection on duration of dilatation, need for surgery, and incidence of complications such as perforation.
Main Results:
- Seven out of ten pediatric patients with CSO achieved successful outcomes with long-term dilatation.
- Only three patients required surgical intervention, indicating the effectiveness of non-operative management.
- A low esophageal perforation rate of 0.47% (2 perforations in 424 dilatations) was observed.
Conclusions:
- Long-term esophageal dilatation is a successful and safe primary treatment modality for the majority of pediatric caustic strictures of the esophagus.
- This approach offers a favorable alternative to surgery, associated with minimal complications.
Abstract:
Caustic strictures of the oesophagus (CSO) in children are managed in different ways. Our study looks into the results of long-term dilatation of such strictures. Of 109 children admitted to our hospital with caustic ingestion, 10 developed strictures. The dilatations were carried out for periods varying from 9 months to 4 years. While 3 patients needed surgical treatment, 7 did not and did well. The oesophageal perforation rate with dilatations was only 0.47% (2 perforations from a total of 424 dilatations). Long-term dilatations are successful in managing a majority of CSO in children and are associated with minimal complications.


Related Concept Videos
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:27
Esophageal Achalasia
 01:25
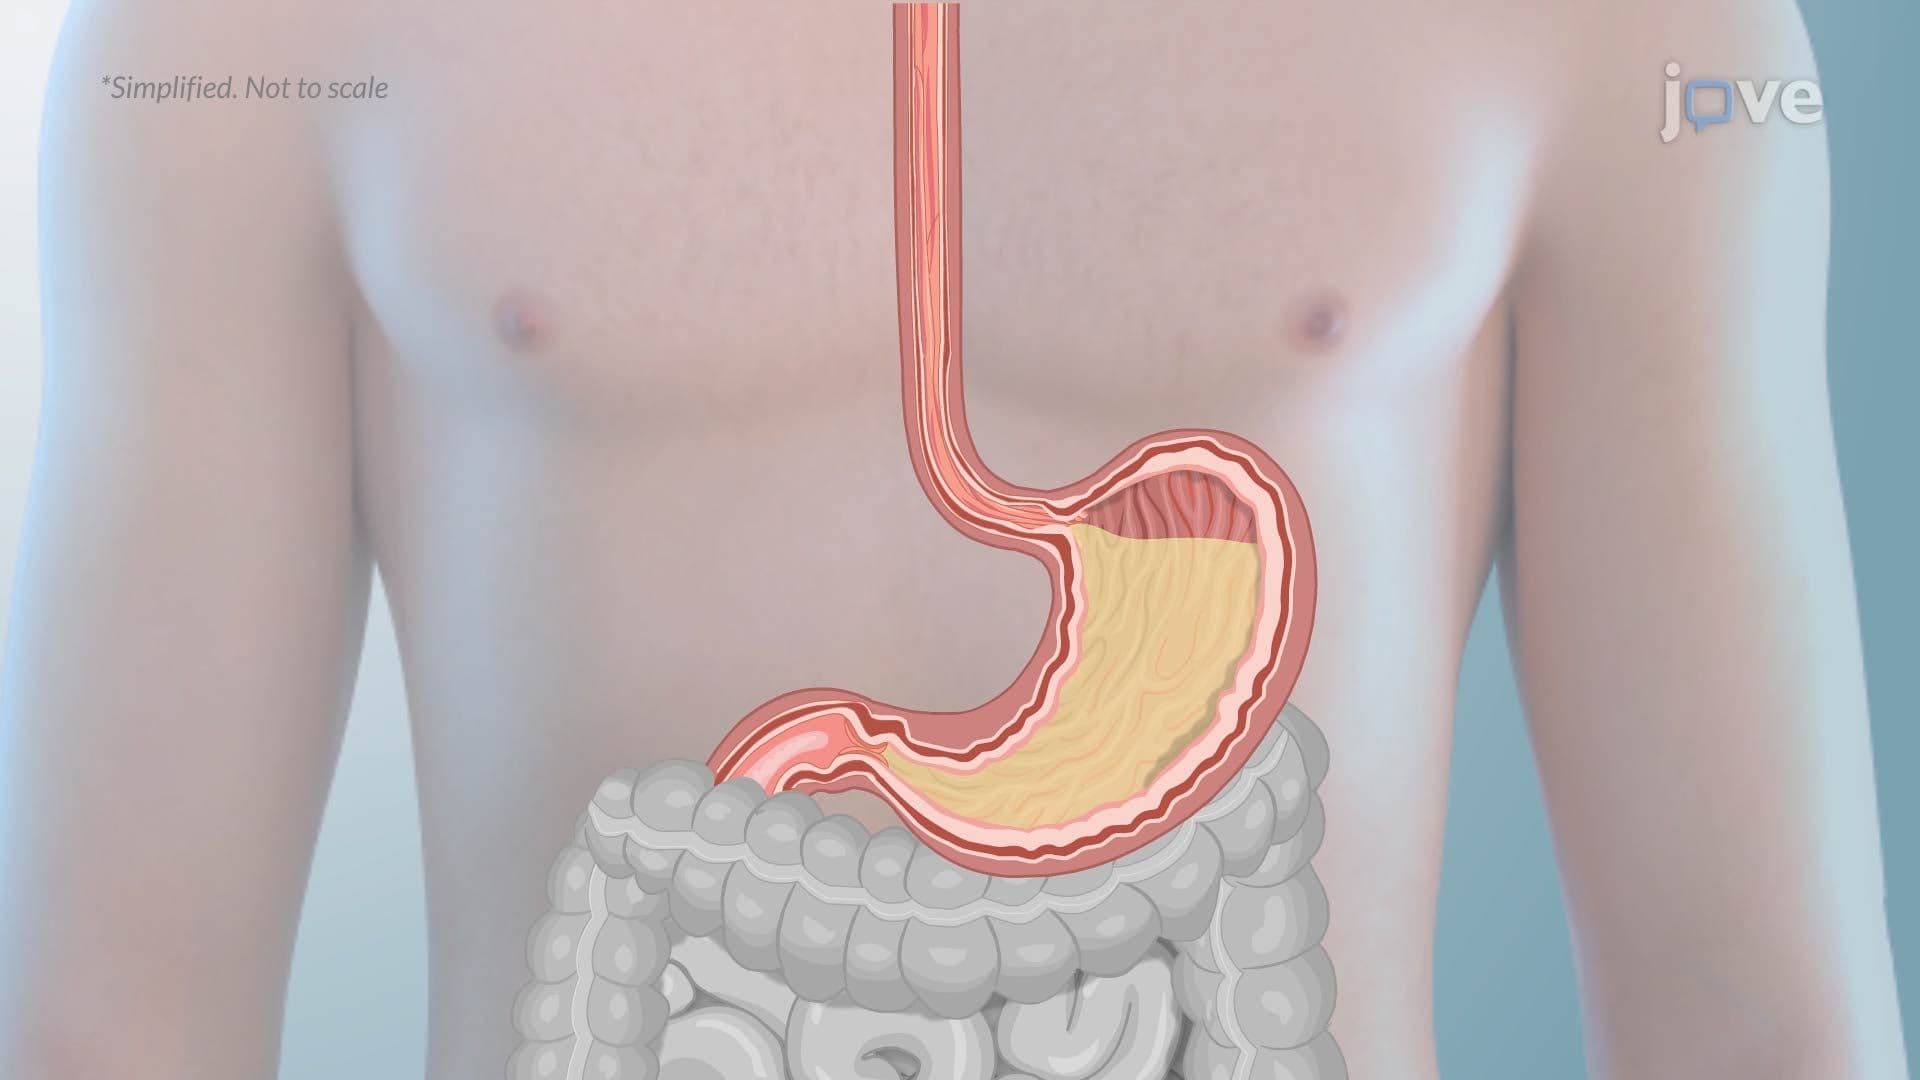
Gastroesophageal Reflux Disease
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...