Alpha-1-antitrypsin deficiency: smoking, decline in lung function and implications for therapeutic trials
Related Experiment Video
Updated: Sep 28, 2026
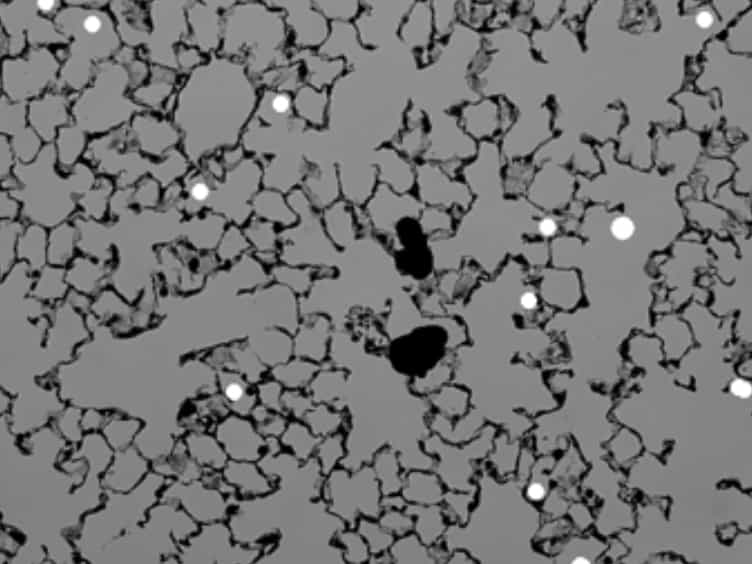
Automated Measurement of Pulmonary Emphysema and Small Airway Remodeling in Cigarette Smoke-exposed Mice
Published on: January 16, 2015
1Department of Respiratory Medicine, King's College Hospital and Guy's, King's and St Thomas' School of Medicine, London, UK.

Background:
Alpha-1-antitrypsin (AT) deficiency is a hereditary disorder associated with pulmonary emphysema. AT replacement therapy has been available for many years with only one randomised controlled trial, showing no improvement in the rate of decline in lung function. We aimed to obtain further data on the natural history of the disorder and thus to refine the criteria for future clinical trials.
Methods:
Homozygotes for Pi type Z were identified among chest clinic patients and close relatives. Clinical and lung function data were obtained by means of a standardised questionnaire administered yearly for a maximum of 15 years.
Results:
Baseline study: forced expiratory volume in 1 s (FEV1) and vital capacity (VC) were studied in 194 Pi type Z patients at registration. Past or present smoking history had the strongest relationship to reduction in FEV1 (P < 0.001), but among those who had smoked, estimated total lifetime tobacco consumption (kg) was not significantly related to FEV1. No effecton FEV1 was produced by gender, age of starting to smoke, asthma, occupation or intra-family factors in sib pairs concordant for smoking. Follow-up study: In 71 patients, the average number of annual lung function assessments per subject was 8.0 (range 6-13) and average follow-up time 97 years (range 4.2-14.9). FEV1 slope tended to be steeper in current smokers than in ex-smokers (0.05 < P < 0.1) and greatest in patients with initial FEV1 in the range 30-65% predicted. Effects on VC were less severe. Much deterioration takes place before emphysematous patients come to clinical attention. FEV1 slopes calculated using only the first four assessments have a significantly greater variance than when calculated on all assessments (F = 3.79; P < 0.01). FEV1 and VC slopes using post-bronchodilator values are greater than when using pre-bronchodilator values.
Conclusions:
Future trials of AT replacement therapy need rigorous standardisation of lung function testing (including bronchodilator protocol) together with an adequate period of assessment. Only randomised controlled trials should be considered valid. Therapy should ideally be started earlier than normally envisaged and before the onset of clinical emphysema.
Related Concept Videos
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:26
COPD: Management Using Bronchodilators and Corticosteroids