Related Experiment Video
Updated: Sep 28, 2026


Using Human Induced Pluripotent Stem Cell-derived Hepatocyte-like Cells for Drug Discovery
Published on: May 19, 2018
How, when, and why to use apolipoprotein B in clinical practice
1Mike Rosenbloom Laboratory for Cardiovascular Research, McGill University Health Centre, Laboratory for Cardiovascular Research, Royal Victoria Hospital, Montreal, Quebec, Canada. allan.sniderman@muhc.mcgill.ca

Insights
Plasma apolipoprotein B (apo B) is a superior marker for coronary artery disease (CAD) risk and statin therapy effectiveness compared to LDL cholesterol. Apo B provides a more accurate assessment of cardiovascular risk in diverse patient groups.
Area of Science:
- Cardiovascular Medicine
- Clinical Chemistry
- Lipidology
Background:
- Plasma apolipoprotein B (apo B) is increasingly recognized as a superior biomarker for coronary artery disease (CAD) risk.
- Clinical risk is influenced by LDL particle number and the presence of small, dense LDL particles.
Purpose of the Study:
- To demonstrate the clinical utility of apo B measurement in practice.
- To highlight apo B's superiority over LDL cholesterol for CAD risk assessment and guiding statin therapy.
Main Methods:
- Review of evidence supporting apo B's efficacy over LDL cholesterol.
- Outline of biological mechanisms underlying apo B's predictive power.
- Presentation of clinical scenarios involving hypertriglyceridemic, hypercholesterolemic, and normolipidemic subjects.
Main Results:
- Apo B is a more accurate index of CAD risk than total or LDL cholesterol.
- Apo B effectively guides the adequacy of statin therapy.
- Laboratory measurement of apo B is standardized, precise, and cost-effective, unlike calculated LDL cholesterol which can underestimate true levels.
Conclusions:
- Apo B offers a more robust assessment of cardiovascular risk and therapeutic response.
- Routine use of apo B in diagnosing dyslipidemias and monitoring statin therapy is clinically justified.
- Methodological concerns regarding calculated LDL cholesterol underscore the need for apo B utilization.
Abstract:
The evidence is now clear that plasma apolipoprotein (apo) B is a better index of the risk of coronary artery disease (CAD) than total or low-density lipoprotein (LDL) cholesterol. Moreover, the evidence is also clear that clinical risk of apo B is determined not only by LDL particle number but also by whether small, dense LDL particles are present. The objective of this article, therefore, is to demonstrate how, when, and why apo B should be used in clinical practice. First, the evidence that apo B is superior to LDL cholesterol as an index of the risk of CAD and as a guide to the adequacy of statin therapy is briefly reviewed. Next, the biological bases for this superiority in identifying risk are outlined. Clinical scenarios are then outlined demonstrating the value of measuring apo B in hypertriglyceridemic, hypercholesterolemic, and normolipidemic subjects. The methodological soundness of the laboratory determinations of lipids and apo B is also an important issue. Concern has been raised regarding the measurement of apo B, but it is standardized, precise, and not expensive. Paradoxically, it is becoming ever more obvious that the methodological problems lie with calculated LDL cholesterol. To the known deficiencies must be added the fact that calculated LDL cholesterol systematically underestimates true LDL cholesterol at values close to target levels.Thus, from every perspective-pathophysiology, diagnosis, assessment of therapy, and methodologic soundness-there are powerful clinical arguments why apo B should be used in the routine diagnosis of dyslipidemias and assessment of the adequacy of statin therapy.


Related Concept Videos
 01:25
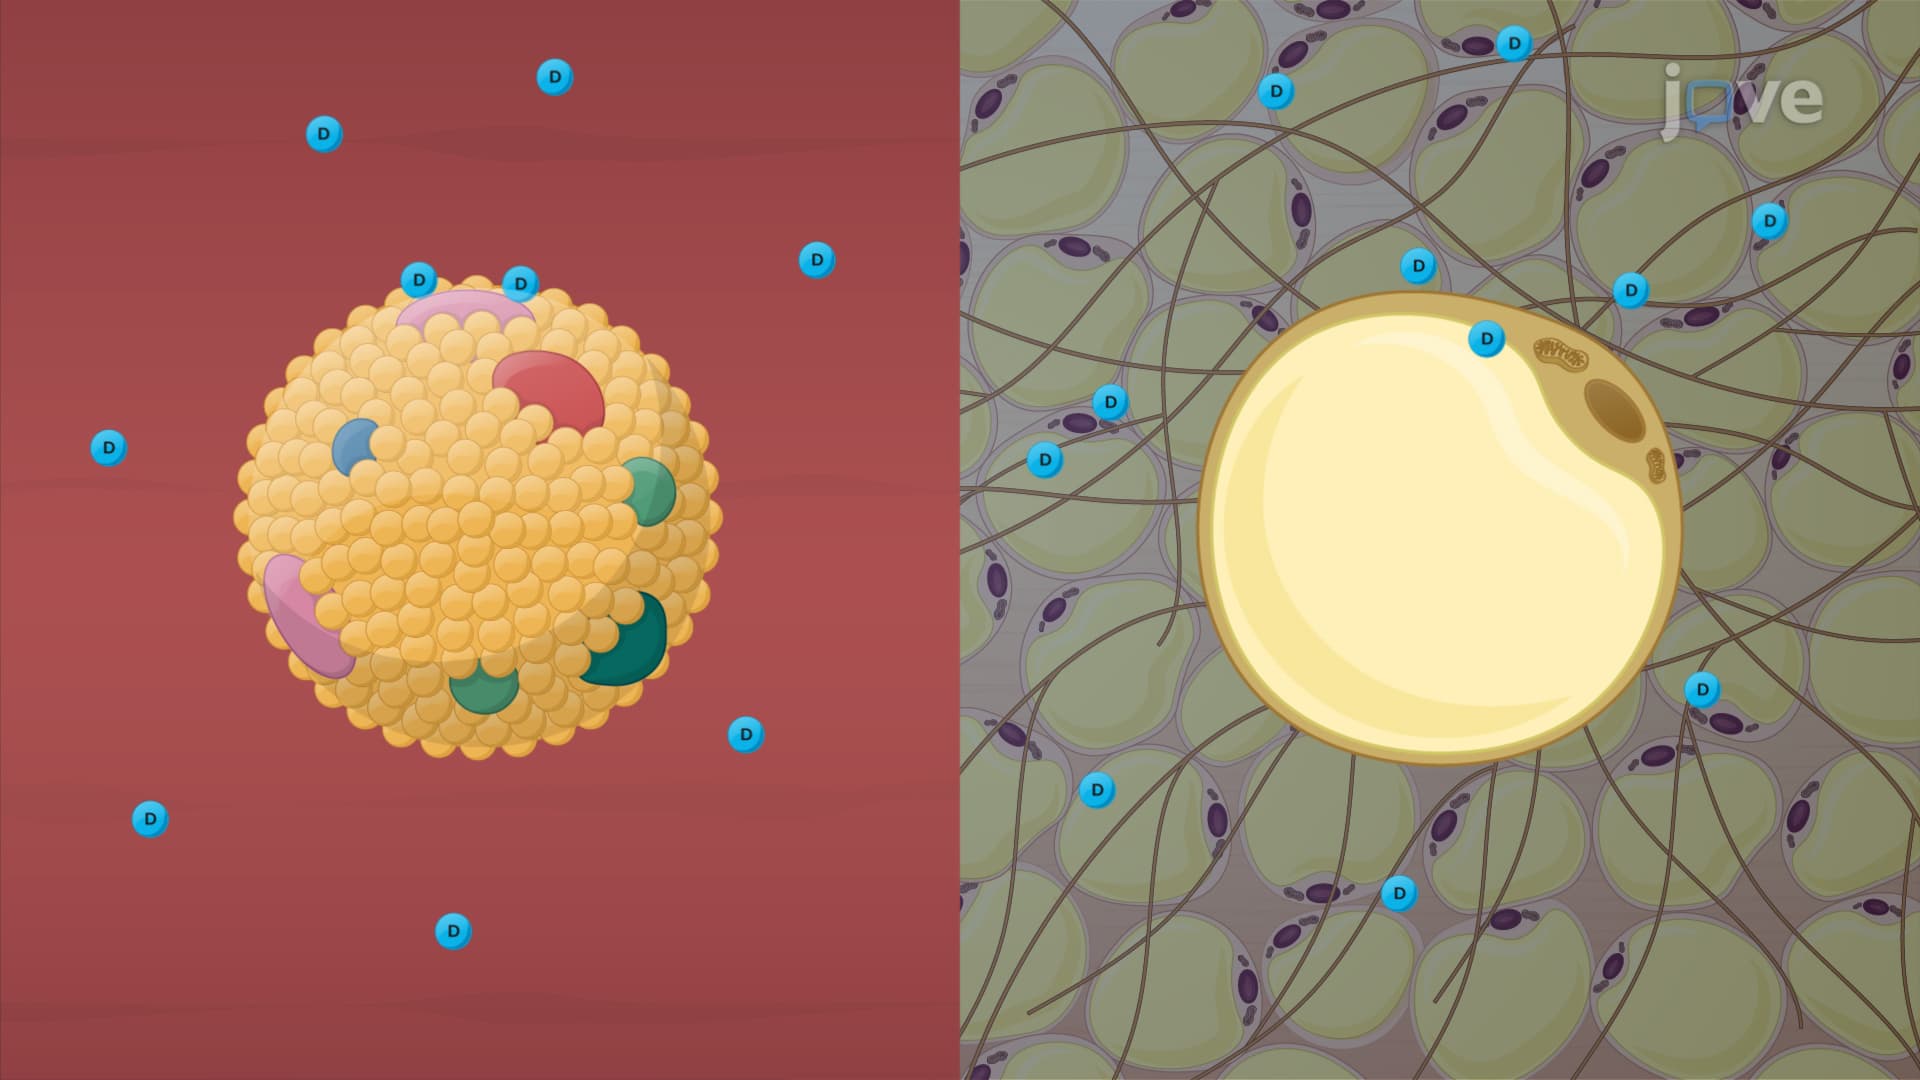
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:20
Factors Affecting Protein-Drug Binding: Protein-Related Factors
The physicochemical properties of a drug play a significant role in its ability to bind to proteins. Lipophilic drugs, which dissolve in fats, oils, and lipids, can be bound by...
 01:29
Drug Distribution: Plasma Protein Binding
 01:15
Bioavailability Study Design: Healthy Subjects Versus Patients
 01:30
Drug Binding to Blood Components
HSA is the most abundant plasma protein and is vital in drug binding. It contains distinct drug-binding sites, with different drugs exhibiting affinity for specific sites. There are three main drug-binding domains for HSA: sites I, II, and III. These domains are further...
 01:29
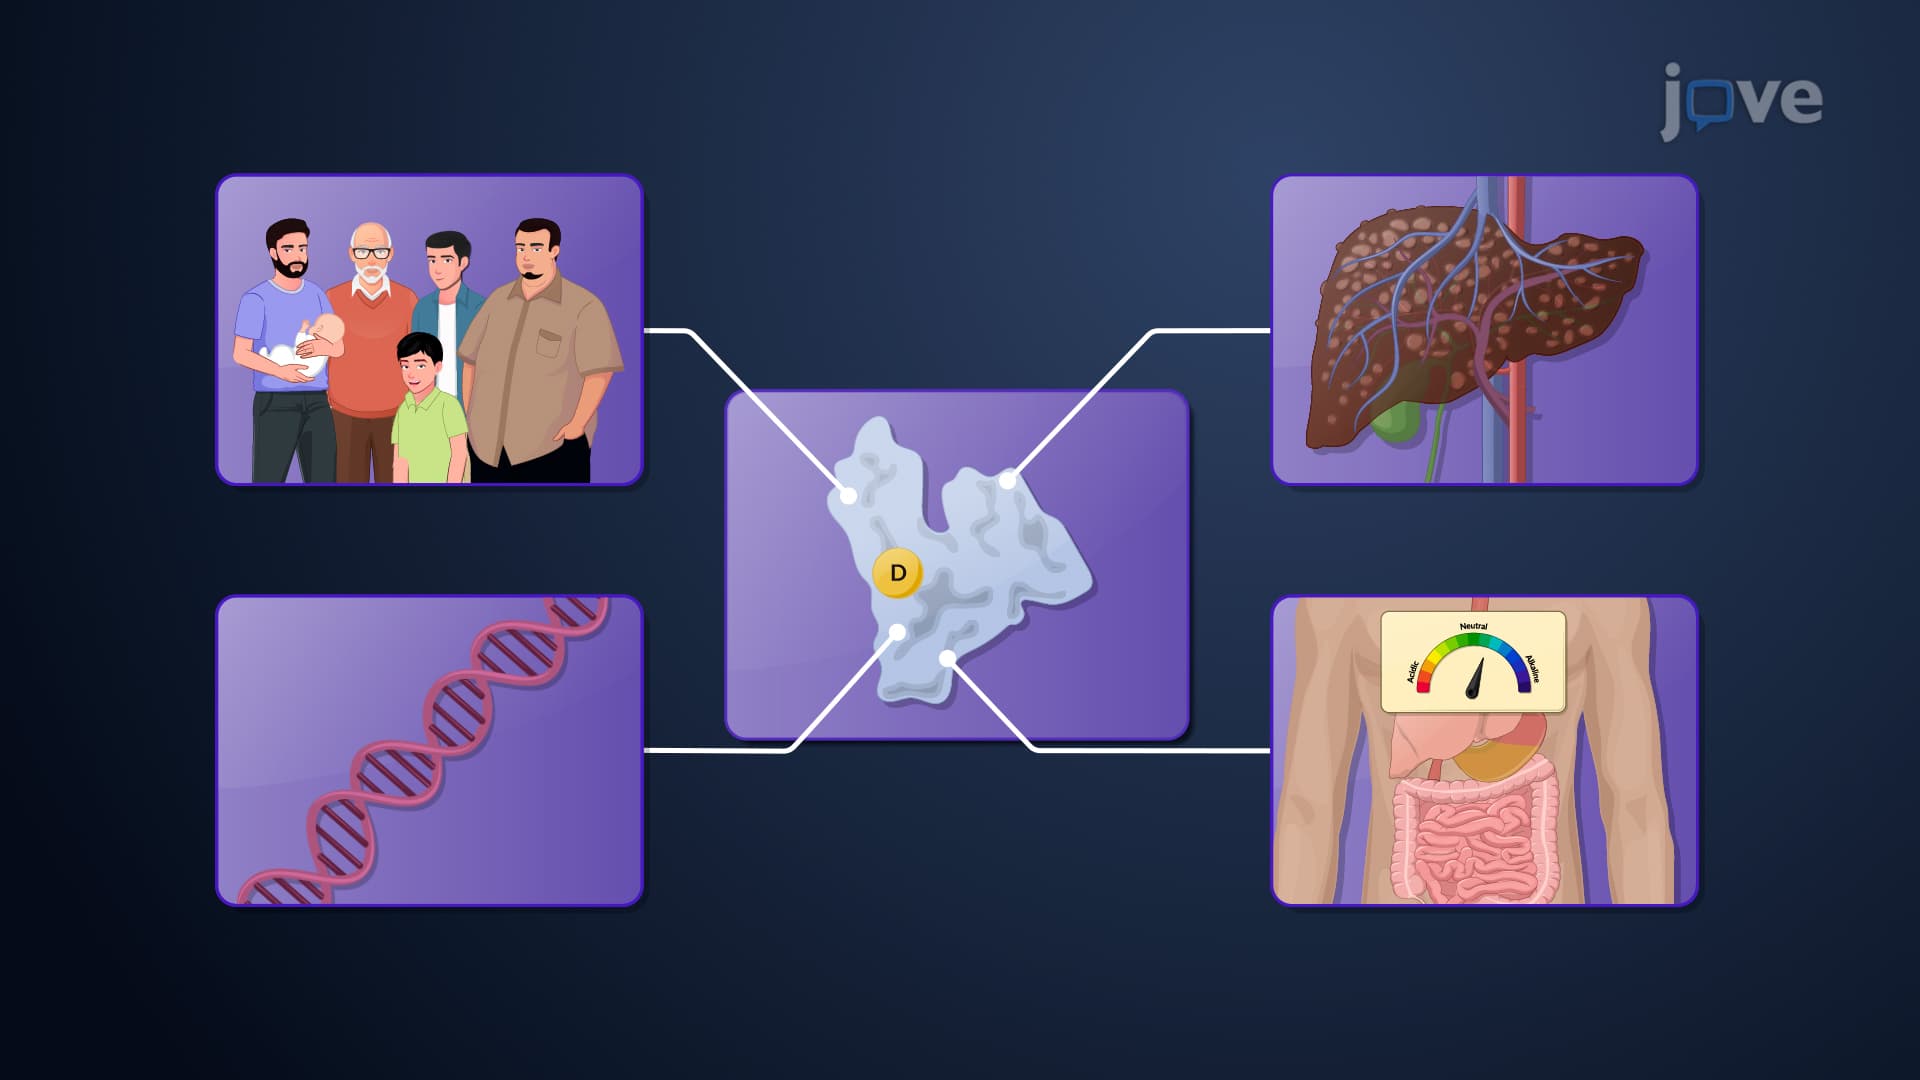
Factors Affecting Protein-Drug Binding: Patient-Related Factors
Age stands as a key determinant in protein-drug binding. Neonates, characterized by low albumin content, experience heightened concentrations of unbound drugs such as phenytoin and...