Related Experiment Video
Updated: Jul 12, 2026
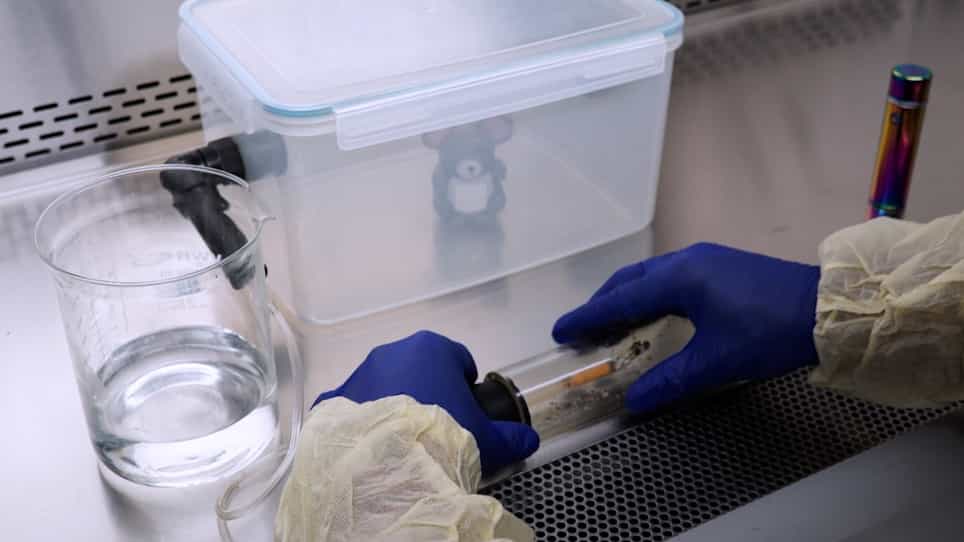

Cigarette Smoke Exposure in Mice using a Whole-Body Inhalation System
Published on: October 22, 2020
Effect of chronic and acute cigarette smoking on the pharyngoglottal closure reflex
1MCW Dysphagia Institute, Department of Medicine, Medical College of Wisconsin and Zablocki Veterans Affairs Medical Center, Milwaukee, Wisconsin, USA. dua@mcw.edu

Background:
Injection of water into the pharynx at a threshold volume induces vocal cord adduction--the pharyngoglottal closure reflex (PGCR). This reflex together with other supraoesophageal reflexes may be helpful in preventing aspiration. Cigarette smoking has an adverse affect on the pharyngo-upper oesophageal sphincter contractile reflex and reflexive pharyngeal swallow. The effect of smoking on PGCR has not been studied previously.
Aims:
To elucidate the effect of chronic and acute cigarette smoking on PGCR.
Subjects:
We studied 10 chronic smokers and 10 non-smokers before and after real/simulated smoking, respectively.
Methods:
Using concurrent recordings, glottal function was monitored by video endoscopy, swallowing by electromyography, and PGCR was triggered by rapid and slow pharyngeal water injections.
Results:
The threshold volume to trigger PGCR during rapid injection was significantly higher in chronic smokers (non-smoker 0.20 (SEM 0.02) ml, smoker 0.36 (0.02) ml; p<0.001). In six of 10 smokers, acute smoking abolished this reflex during slow water injection.
Conclusions:
Smoking adversely affects stimulation of PGCR. This finding may have implications in the development of reflux related respiratory complications in smokers.


Related Concept Videos
 01:23
Drugs Acting on Autonomic Ganglia: Stimulants
Ganglionic stimulants activate NM nicotinic receptors in autonomic ganglia, falling into two categories: nicotine mimetics [e.g., lobeline, dimethylpiperazine, tetramethylammonium] and muscarinic receptor agonists [e.g., muscarine, methacholine]. The first category's action is rapid and blocked by nicotinic receptor antagonists, while the second category's action is delayed and blocked by atropine-like agents. Nicotine, an alkaloid, affects the heart rate by stimulating sympathetic or...
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...
 01:30
Acute Respiratory Failure-III
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features