Early prediction of improvement in ejection fraction after acute myocardial infarction using low dose dobutamine
F Nijland1, O Kamp, P M J Verhorst
1Department of Cardiology and Institute for Cardiovascular Research, VU Medical Centre, Amsterdam, Netherlands. fr.nijland@12move.nl

Insights
Myocardial viability after acute myocardial infarction predicts ejection fraction improvement. This, along with infarct characteristics, helps estimate recovery potential at the bedside.
Area of Science:
- Cardiology
- Echocardiography
- Myocardial Infarction Research
Background:
- Assessing myocardial viability post-acute myocardial infarction (AMI) is crucial for predicting left ventricular function recovery.
- Ejection fraction (EF) changes in the early months after AMI can indicate the extent of myocardial recovery.
- Understanding predictors of EF improvement is vital for patient management and risk stratification.
Purpose of the Study:
- To investigate the relationship between changes in ejection fraction (EF) within three months of acute myocardial infarction (AMI).
- To determine the predictive value of myocardial viability for EF improvement after AMI.
- To identify clinical and echocardiographic factors associated with significant EF recovery.
Main Methods:
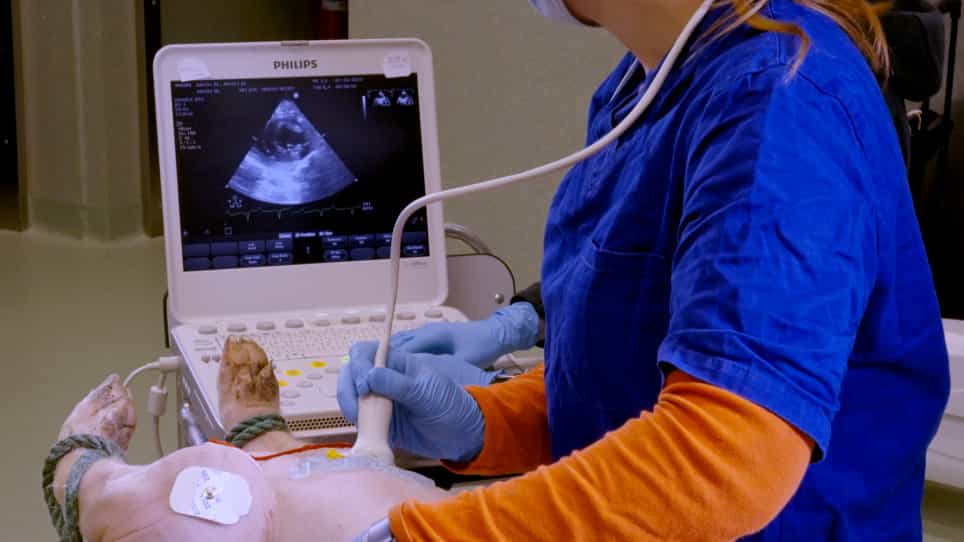
- 107 patients underwent low-dose dobutamine echocardiography to assess myocardial viability within days of AMI.
- Echocardiography was repeated at three months to measure changes in left ventricular volumes and ejection fraction.
- Statistical analyses, including ROC and multivariate logistic regression, were used to identify predictors of EF improvement.
Main Results:
- Patients with myocardial viability showed a significant increase in EF (4.4%) compared to those without (0.04%, p < 0.001).
- A > or = 5% EF increase was observed in 20% of patients.
- Myocardial viability, non-Q wave infarction, and anterior infarction were independent predictors of EF improvement, with viability being the strongest.
Conclusions:
- Myocardial viability is the most significant predictor of ejection fraction improvement following acute myocardial infarction.
- Combining viability assessment with infarct characteristics (location, Q wave presence) allows for bedside estimation of potential EF recovery.
- These findings aid in personalizing treatment strategies and managing patients post-myocardial infarction.
Objective:
To evaluate the relation between changes in ejection fraction during the first three months after acute myocardial infarction and myocardial viability.
Patients:
Myocardial viability was assessed using low dose dobutamine echocardiography in 107 patients at mean (SD) 3 (1) days after acute myocardial infarction. Cross sectional echocardiography was repeated three months later. Left ventricular volumes and ejection fraction were determined from apical views using the Simpson biplane formula.
Results:
In patients with viability, ejection fraction increased by 4.4 (4.3)%; in patients without viability it remained unchanged (0.04 (3.6)%; p < 0.001). A > or = 5% increase in ejection fraction was present in 21 of 107 patients (20%). Receiver operating characteristic analysis showed that myocardial viability in > or = 2 segments predicted this increase in ejection fraction with a sensitivity of 81% and a specificity of 65%. Multivariate logistic regression analysis was used to define which clinical and echocardiographic variables were related to > or = 5% improvement in ejection fraction. Myocardial viability, non-Q wave infarction, and anterior infarction all emerged as independent predictors, myocardial viability being the best (chi(2) = 14.5; p = 0.0001). Using the regression equation, the probability of > or = 5% improvement in ejection fraction for patients with a non-Q wave anterior infarct with viability was 73%, and for patients with a Q wave inferior infarct without viability, only 2%.
Conclusions:
Myocardial viability after acute myocardial infarction is the single best predictor of improvement in ejection fraction. In combination with infarct location and Q wave presence, the probability of > or = 5% improvement can be estimated in individual patients at the bedside.