Related Experiment Video
Updated: Aug 28, 2026
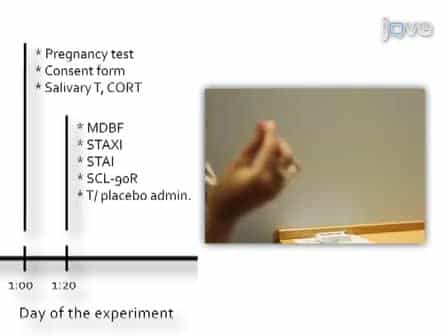

Combining Behavioral Endocrinology and Experimental Economics: Testosterone and Social Decision Making
Published on: March 2, 2011
Medical tests: women's reported and preferred decision-making roles and preferences for information on benefits,
Heather M Davey1, Alexandra L Barratt, Elizabeth Davey
1Screening and Test Evaluation Program, School of Public Health, Room 319A, Edward Ford Building, University of Sydney, Sydney NSW 2006, Australia. daveyh@health.usyd.edu.au

Objective:
To determine women's preferences for and reported experience with medical test decision-making.
Design:
Computer-assisted telephone survey.
Setting And Participants:
Six hundred and fifty-two women resident in households randomly selected from the New South Wales electronic white pages.
Main Outcome Measures:
Reported and preferred test and treatment (for comparison) decision-making, satisfaction with and anxiety about information on false results and side-effects; and effect of anxiety on desire for such information.
Results:
Overall most women preferred to share test (94.6%) and treatment (91.2%) decision-making equally with their doctor, or to take a more active role, with only 5.4-8.9% reporting they wanted the doctor to make these decisions on their behalf. This pattern was consistent across all age groups. In general, women reported experiencing a decision-making role that was consistent with their preference. Women who had a usual doctor were more likely to report experiencing an active role in decision-making. More women reported receiving as much information as they wanted about the benefits of tests and treatment than about the side-effects of tests and treatment. Most women wanted information about the possibility of false test results (91.5%) and test side-effects (95.6%), but many reported the doctor never provided this information (false results = 40.0% and side-effects = 31.3%). A substantial proportion said this information would make them anxious (false results = 56.6% and side-effects = 43.1%), but reported they wanted the information anyway (false results = 77.6% and side-effects = 88.1%).
Conclusions:
Women prefer an active role in test and treatment decision-making. Many women reported receiving inadequate information. If so, this may jeopardize informed decision-making.


Related Concept Videos
 02:07
Blind Procedures
 01:14
Decision Making: Traditional Method
First, a specific claim about the population parameter is decided based on the research question and is stated in a simple form. Further, an opposing statement to this claim is also stated. These statements can act as null and alternative hypotheses, out of which a null hypothesis would be a...
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast, controlled...
 01:13
Sensitivity, Specificity, and Predicted Value
Sensitivity is the...
 01:23
Assessment of the Cardiovascular System I: Subjective Data
Initial Enquiry
Ask the patient about their primary concern and thoroughly explore all reported symptoms.
Medical History
Investigate past illnesses affecting the cardiovascular system, such as angina, anemia, rheumatic fever, congenital heart disease, stroke, thrombophlebitis, dysrhythmias, varicosities
Inquire about symptoms...
 01:22
Self-Report Tests of Personality