Are stents still a useful therapy for benign prostatic hyperplasia?
Related Experiment Video
Updated: Sep 28, 2026
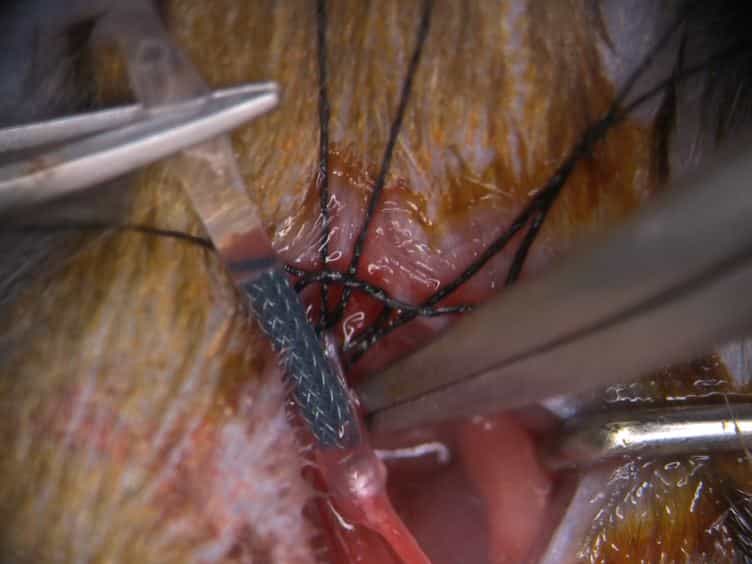
A Murine Model of Stent Implantation in the Carotid Artery for the Study of Restenosis
Published on: May 14, 2013
Jason S Ogiste1, Kimberly Cooper, Steven A Kaplan
1Department of Urology, Columbia University College of Physicians and Surgeons, 161 Fort Washington Avenue, New York, NY 10032, USA.

Purpose Of Review:
The use of an endoprosthesis to maintain lumenal patency is a well-established concept used in a variety of surgical settings, including cardiovascular and gastrointestinal pathologies. However, the utility of self-retaining endoprosthetics and their application in prostatic pathology and benign prostatic hyperplasia is not as clear. This report reviews recent developments in the management of symptomatic benign prostatic hyperplasia, particularly the current role of intraprostatic stenting in the advent of other minimally invasive therapies such as laser prostatectomy.
Recent Findings:
Over the past 5 years, urology has witnessed the proliferation of minimally invasive surgical therapies for benign prostatic hyperplasia. These interventions have enabled the urologist to treat a problem whose management was once limited to medical therapy, transurethral resection of the prostate, or open, relatively morbid surgery. The role of stents as an intermediary in cases of treatment failure, or as definitive therapy for benign prostatic hyperplasia and its associated problems is still not clear, when compared with newer, minimally invasive options. Current literature on stents is relatively sparse. However recent studies demonstrate that permanent and temporary prostatic urethral stenting are effective in relieving obstruction and urinary retention. Nevertheless larger controlled clinical studies are needed to demonstrate the real value of this intervention.
Summary:
Prostatic stenting has a definite role in the management of benign prostatic hypertrophy, but stents must be used with caution because complications are still relatively common, and their true efficacy and utility in the urological setting has not been determined.

Related Concept Videos
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:26
Mitral Stenosis III: Medical Management
 01:18
Treatment for Pulmonary Arterial Hypertension: Endothelin Receptor Antagonists
ETs are synthesized through a complex sequence of enzymatic steps, primarily involving an enzyme referred to as endothelin-converting enzyme (ECE). Of...
 01:28
Treatment for Pulmonary Arterial Hypertension: Phosphodiesterase Inhibitors
Among the PDE5 inhibitors, sildenafil (Revatio) stands out as a competitive and selective inhibitor. It operates by elevating cellular levels of cGMP and augmenting signaling through the cGMP-PKG pathway, promoting vasodilation. Upon oral...
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...